Related Experiment Video
Updated: Sep 29, 2026
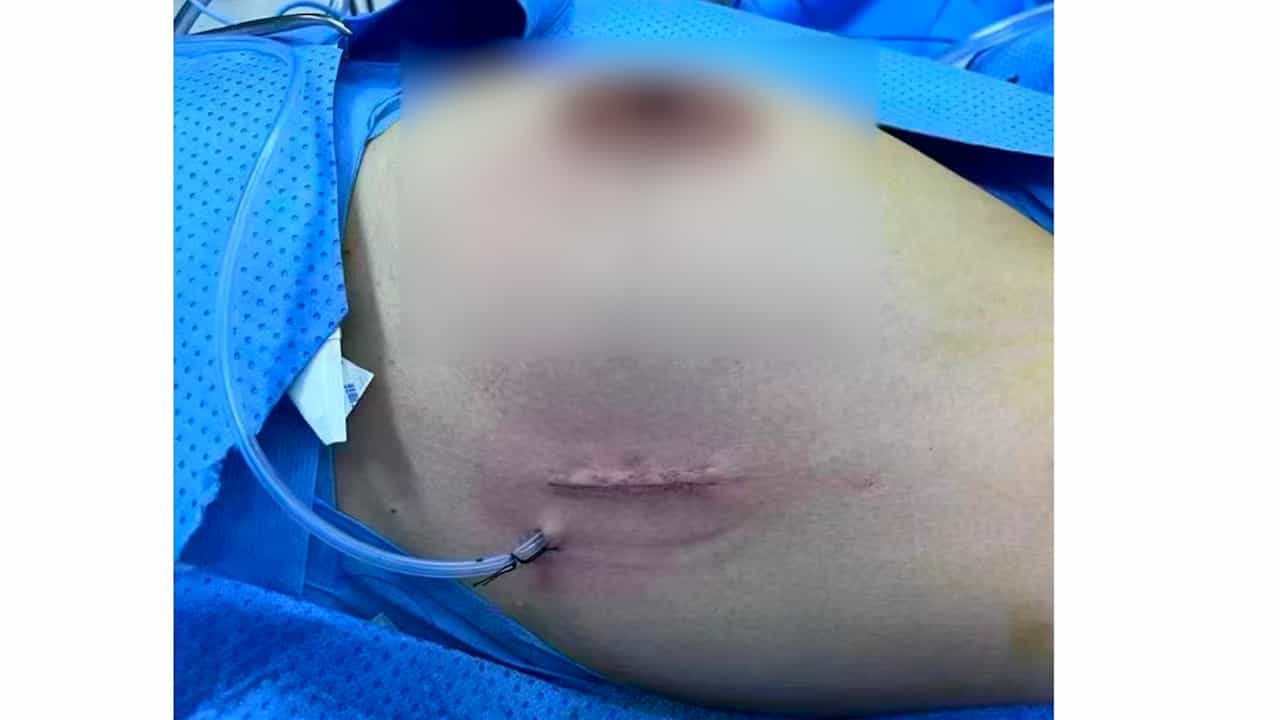

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Axillary Nodal Upstaging in cT1N0 Invasive Lobular Carcinoma: Evaluating Applicability of SOUND Trial Results
Thomas Amburn1, Anita Mamtani1, Jane J Chen2
1Breast Service, Department of Surgery, Memorial Sloan Kettering Cancer Center, New York, NY.

Objective:
To determine whether sentinel lymph node biopsy (SLNB) omission is applicable to stage 1 invasive lobular breast cancer (ILC).
Background:
The SOUND and INSEMA randomized controlled trials demonstrated that SLNB omission is noninferior to performing SLNB in early-stage, clinically node-negative (cT1-2N0), hormone receptor-positive/HER2-negative (HR+/HER2-) patients with breast cancer with negative preoperative axillary ultrasound. However, the applicability of SLNB omission in ILC has been uncertain.
Methods:
We retrospectively identified patients with cT1N0, HR+/HER2- pure ILC, and normal axillary ultrasound who underwent upfront surgery with SLNB between 2009 and 2024. Clinicopathologic characteristics and pathologic nodal burden were evaluated.
Results:
Six hundred thirty-nine patients met the inclusion criteria, of whom the majority were postmenopausal women (72%) with low- to intermediate-grade (88%) and/or classic-type (84%) ILC. Axillary nodal metastases were identified on surgical pathology in 113 (17.7%) patients: 24 (3.8%) pN1mic, 74 (11.6%) pN1, 8 (1.2%) pN2, and 7 (1.1%) pN3. Node-positive patients were more often younger, premenopausal (36% vs. 26%, P=0.035), and presented with larger pathologic tumor size (46.7% vs. 18.3% pT2-3, P<0.001) and lymphovascular invasion (LVI) (19% vs. 3.2%, P<0.001). On univariate analysis, premenopausal status, high grade, and LVI were independently associated with nodal positivity. On multivariate analysis, only LVI remained independently associated with nodal positivity.
Conclusions:
Among patients with SOUND-eligible ILC, 17.7% had axillary nodal metastasis and only 2.3% had extensive axillary nodal metastasis. These findings are comparable to the node-positive rates reported in the SLNB arm of the SOUND (13.7%) and INSEMA (15.1%) trials. High-risk features such as LVI and high grade were associated with nodal positivity.