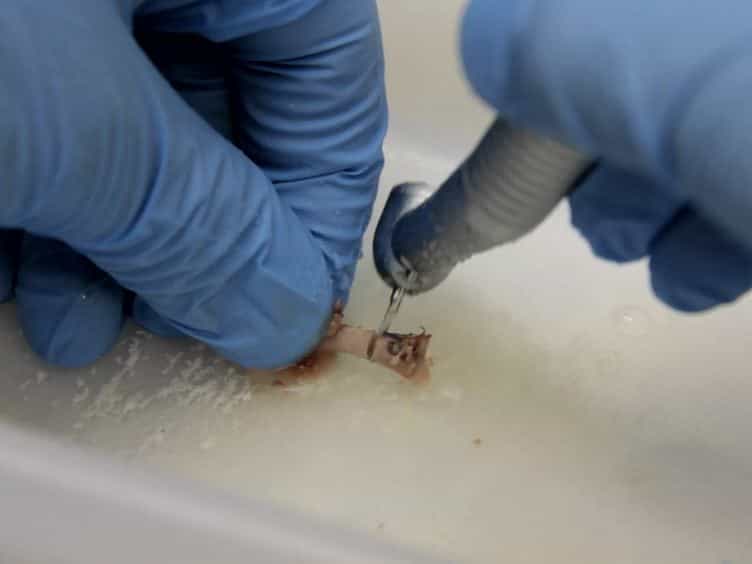
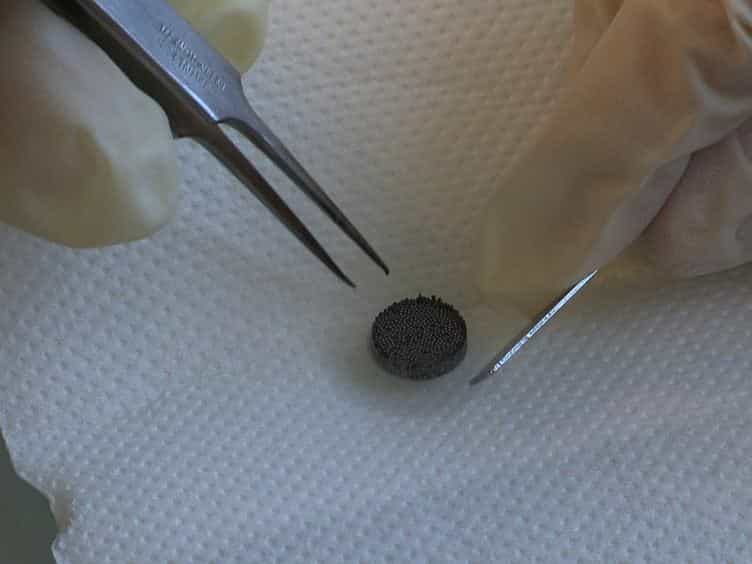
Related Experiment Video
Updated: Sep 29, 2026


Effects of Mechanical Methods Used in Peri-implantitis Treatment on Implant Surface Decontamination and Roughness
Published on: March 14, 2025
Long-Term Peri-Implant Outcomes of Smoother/Hybrid Versus Moderately Rough Titanium Implant Surfaces: An Updated
Heliette Emperatriz E Delgado Castromonte1, Arturo P Jaramillo2, Juan S Hernandez Jiménez3,4,5
1Dentistry, Universidad Gran Mariscal de Ayacucho, Anzoategui, VEN.

Abstract:
Roughened titanium implant surfaces can improve osseointegration, whereas smoother or hybrid coronal surfaces may limit biofilm retention if exposed. Whether either strategy improves long-term peri-implant outcomes remains uncertain. This update compared smoother, minimally rough, or hybrid implant surfaces with moderately rough or rougher surfaces after at least 24 months of follow-up. A 2024 systematic review was used as the baseline evidence set. PubMed was updated from January 1, 2024, through August 7, 2026, with forward and backward citation searching. Randomized clinical reports in adults were eligible when the surface contrast was not inseparable from a different whole implant system or collar macrodesign. The primary outcome was marginal bone-level change (MBL); probing depth (PPD) and implant failure were secondary outcomes. Risk of bias was assessed with RoB 2 (The Cochrane Collaboration, London, UK). RevMan 5.4 (The Cochrane Collaboration, London, UK)-compatible inverse-variance random-effects models were used for continuous outcomes, and a Mantel-Haenszel fixed-effect risk ratio was used for sparse implant-failure events. Ten reports involving 480 enrolled participants and 1,219 implants met the review criteria. Eight reports contributed to the MBL meta-analysis (671 analysis units). There was no evidence of a difference between smoother/hybrid and rougher surfaces (mean difference (MD) 0.07 mm, 95% confidence interval (CI) -0.12 to 0.27; p=0.46; I²=84%). Four reports contributed PPD data (MD -0.36 mm, 95% CI -0.93 to 0.21; p=0.22; I²=72%). Implant failure was uncommon (12/381 versus 6/392 implants); the risk ratio was imprecise and not statistically significant (RR 2.12, 95% CI 0.85 to 5.31; p=0.11; I²=0%). Excluding studies at high risk of bias did not materially alter the MBL conclusion. Current randomized evidence does not establish long-term clinical superiority of smoother/hybrid or rougher titanium implant surfaces. Confidence is very low because of risk of bias, substantial clinical and statistical heterogeneity, sparse failures, and unresolved clustering in multi-implant and split-mouth trials. Surface selection should therefore be individualized and should not rely on roughness alone.