Related Experiment Video
Updated: Sep 30, 2026
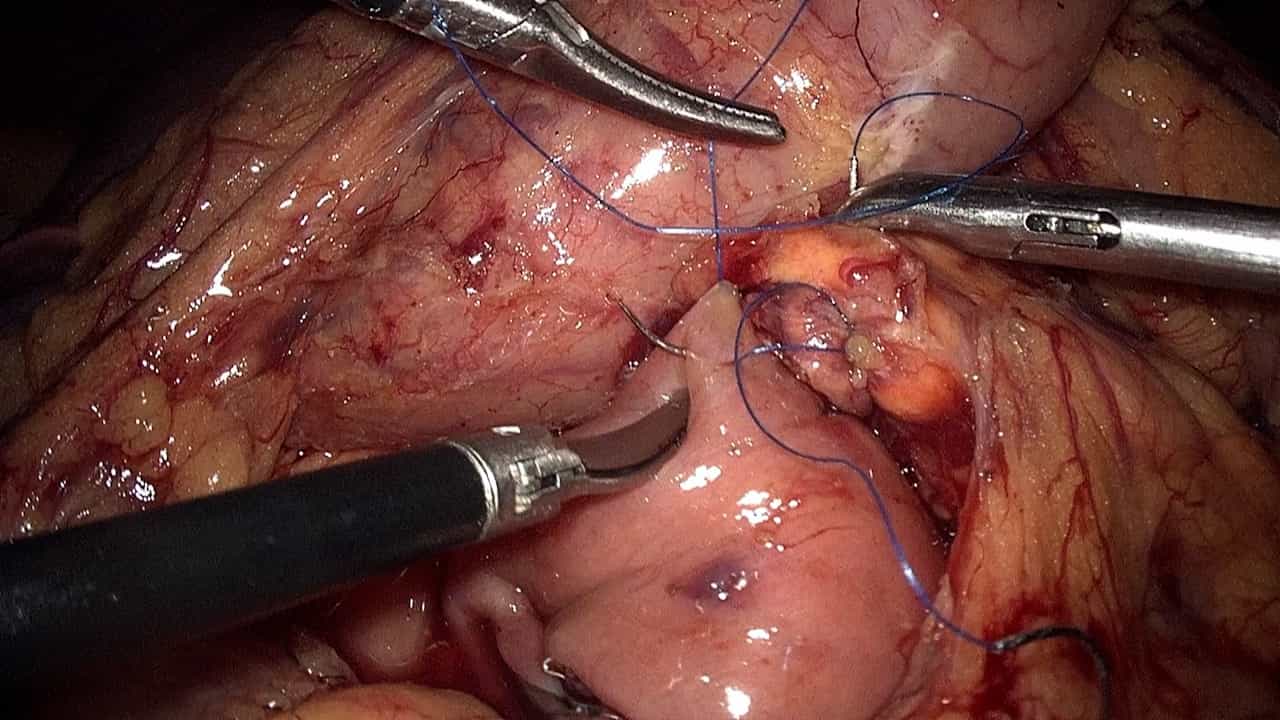

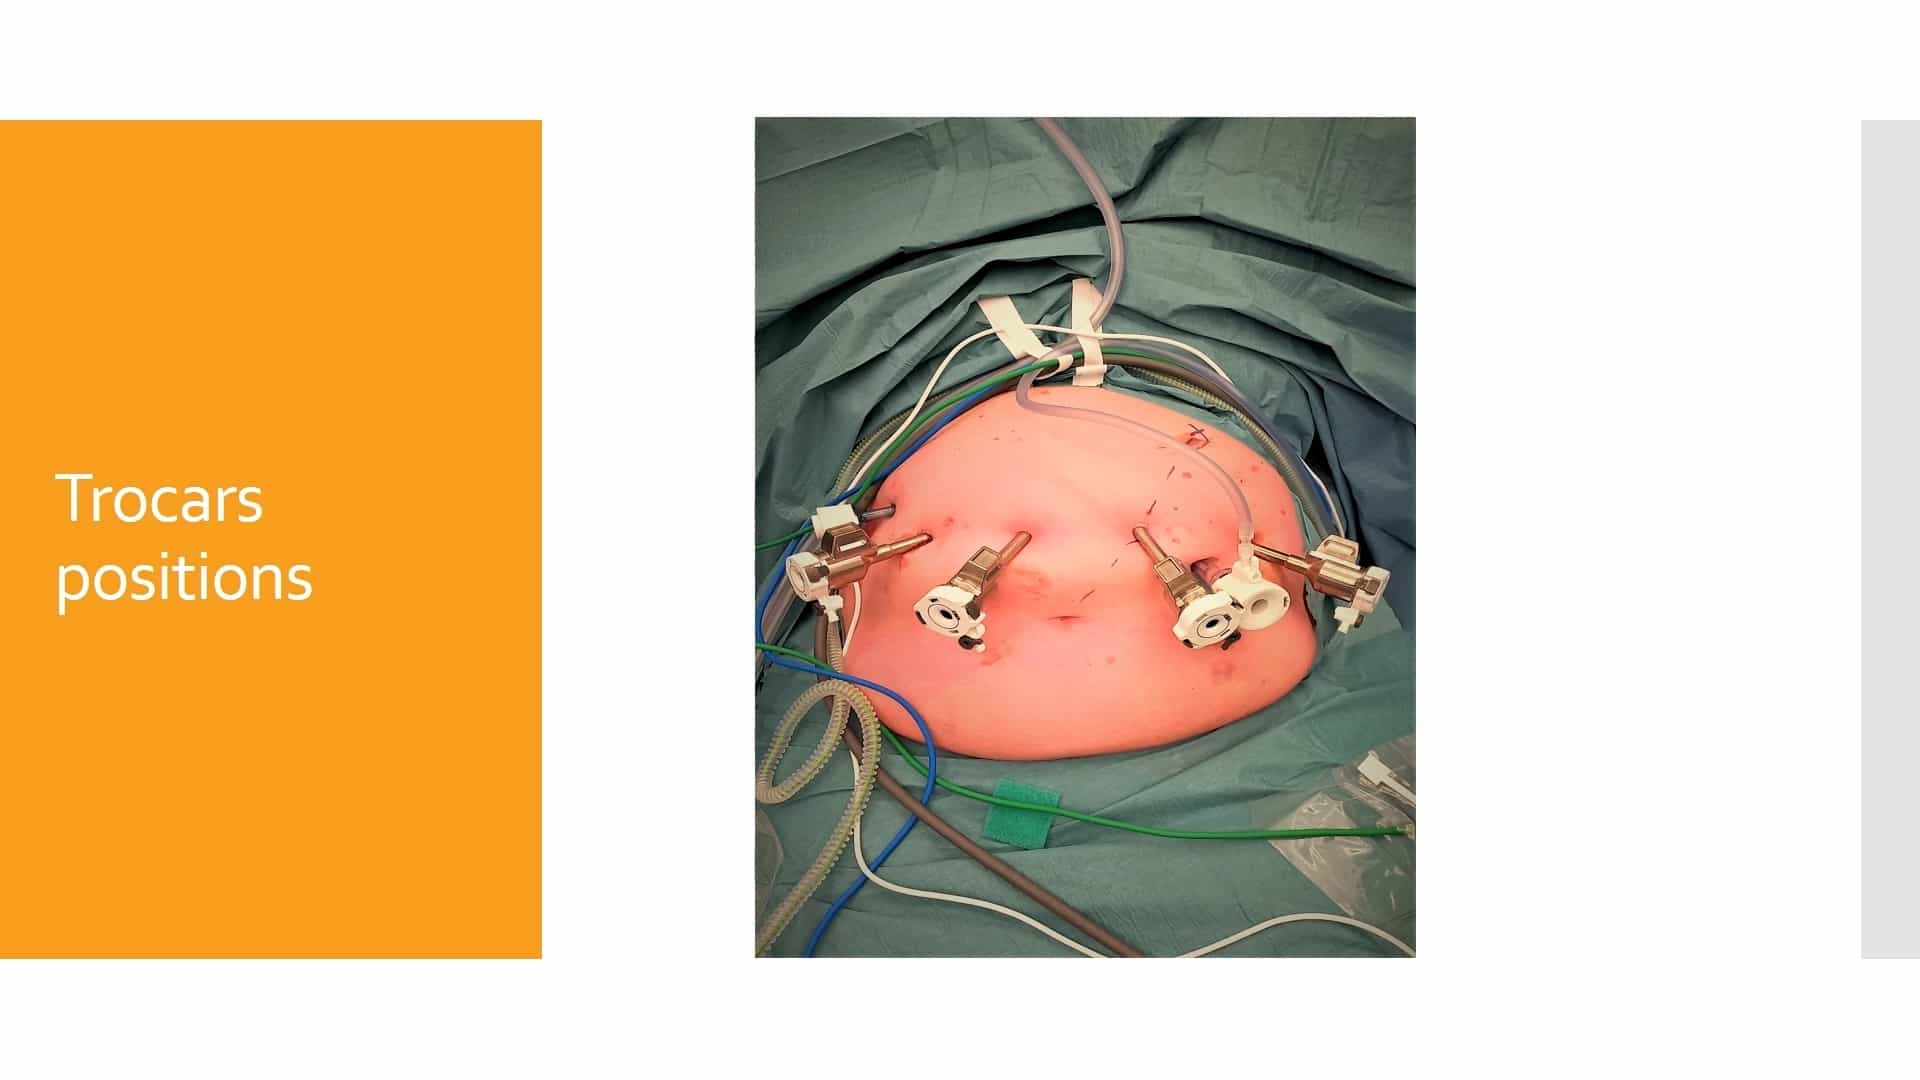
Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
Splenic-preserving total duodenopancreatectomy and a conservative postoperative management: a case report
Khadija El Aalaoui1, Sarah Benammi1,2, Nsiri Zakaria1,2
1Faculty of Medicine of Rabat, Mohammed VI University of Sciences and Health, Morocco.

Abstract:
Pancreatic ductal adenocarcinoma (PDAC) is aggressive. Tumors in the isthmus or body may require extended resection. Splenectomy is common, but spleen preservation can reduce hematologic and infectious morbidity while risking splenic ischemia. A 65-year-old man with insulin-treated type 2 diabetes and mid-body PDAC underwent neoadjuvant chemotherapy and laparoscopic spleen-preserving total duodenopancreatectomy. The patient was admitted in the intensive care unit on postoperative day 1 and 2. On postoperative day 9 patient reported left upper-quadrant pain; computed tomography scan showed a small splenic infarct managed nonoperatively with analgesia and a short antibiotic course. Discharged day was on postoperative day 16. Final pathology reported moderately differentiated PDAC with high-grade PanIN, lymphovascular, and perineural invasion, peripancreatic fat infiltration; 6/26 nodes were positive (ypT3 N2) and 6 nodes with non-necrotizing granulomas. Margins were negative. Spleen-preserving total duodenopancreatectomy can achieve oncologic clearance but poses technical challenges and splenic ischemia risk that can be managed with non-invasive approach. Feasible for select centrally located PDACs with meticulous vascular technique and vigilant follow-up.