Related Experiment Video
Updated: Oct 2, 2026
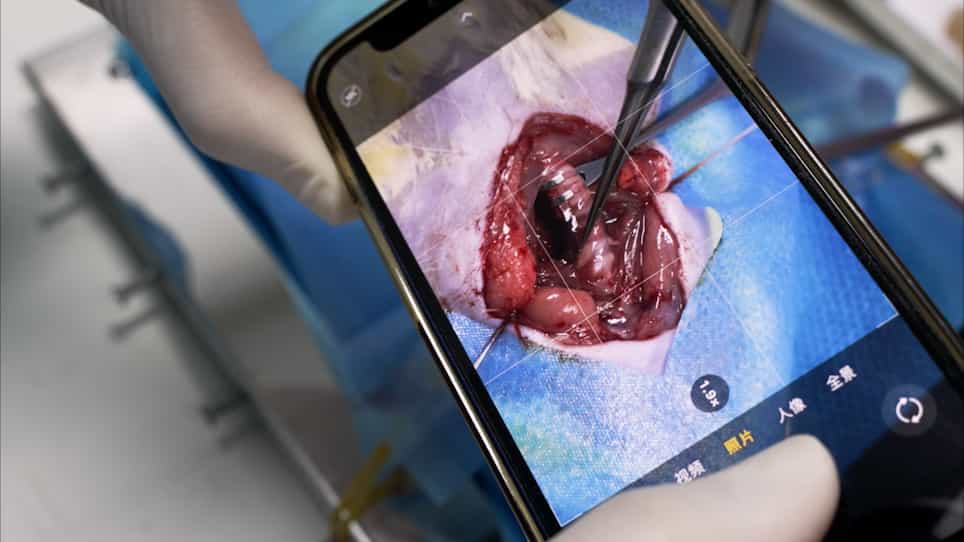

Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Incremental Value of Multimodality Imaging for Preoperative Localization in Primary Hyperparathyroidism: A Stepwise
Erdoğan Özgür1, Özden Savaş1, Asuman Feda Bayrak1
1Dokuz Eylül University Faculty of Medicine, Department of Otorhinolaryngology-Head and Neck Surgery, İzmir, Türkiye.

Objective:
Accurate preoperative localization of the affected parathyroid gland is important for focused parathyroidectomy in primary hyperparathyroidism, yet no single imaging modality is uniformly reliable. This study evaluated the incremental localization benefit of combining ultrasonography (US), 99mTc-sestamibi scintigraphy (MIBI), and four-dimensional computed tomography (4D-CT) and assessed agreement between imaging-measured and histopathological adenoma size.
Methods:
This retrospective, single-center study included 118 patients with histopathologically confirmed parathyroid adenoma who underwent parathyroidectomy between 2015 and 2025. Imaging-based localization was compared with the surgically confirmed location of the adenoma. Sensitivity, positive predictive value, and incremental localization accuracy were calculated. Size agreement was assessed using Bland-Altman analysis, and US sensitivity was examined according to gland location.
Results:
Site-level sensitivity was 71.8% for US, 72.8% for MIBI, 66.7% for CT, and 60.0% for 4D-CT, with no significant pairwise differences (all p>0.05). Adding MIBI to US significantly increased localization accuracy from 71.7% to 84.1% (n=113, McNemar p<0.001); adding 4D-CT to US+MIBI further raised accuracy from 73.5% to 79.4% in a smaller cohort (n=34), though this increment was not statistically significant (p=0.50). US sensitivity fell sharply with anatomical difficulty, from 80.9% for inferior glands to 61.1% for superior and 16.7% for ectopic glands. US also systematically underestimated adenoma size, particularly for larger lesions (bias -10.8 mm; 95% limits of agreement -50.1 to 28.5 mm).
Conclusion:
Combining US with MIBI improved localization accuracy. The addition of 4D-CT yielded a further, statistically non-significant increase in the smaller cohort studied. These findings support a stepwise approach to preoperative imaging for focused parathyroidectomy.
