Related Experiment Video
Updated: Oct 3, 2026
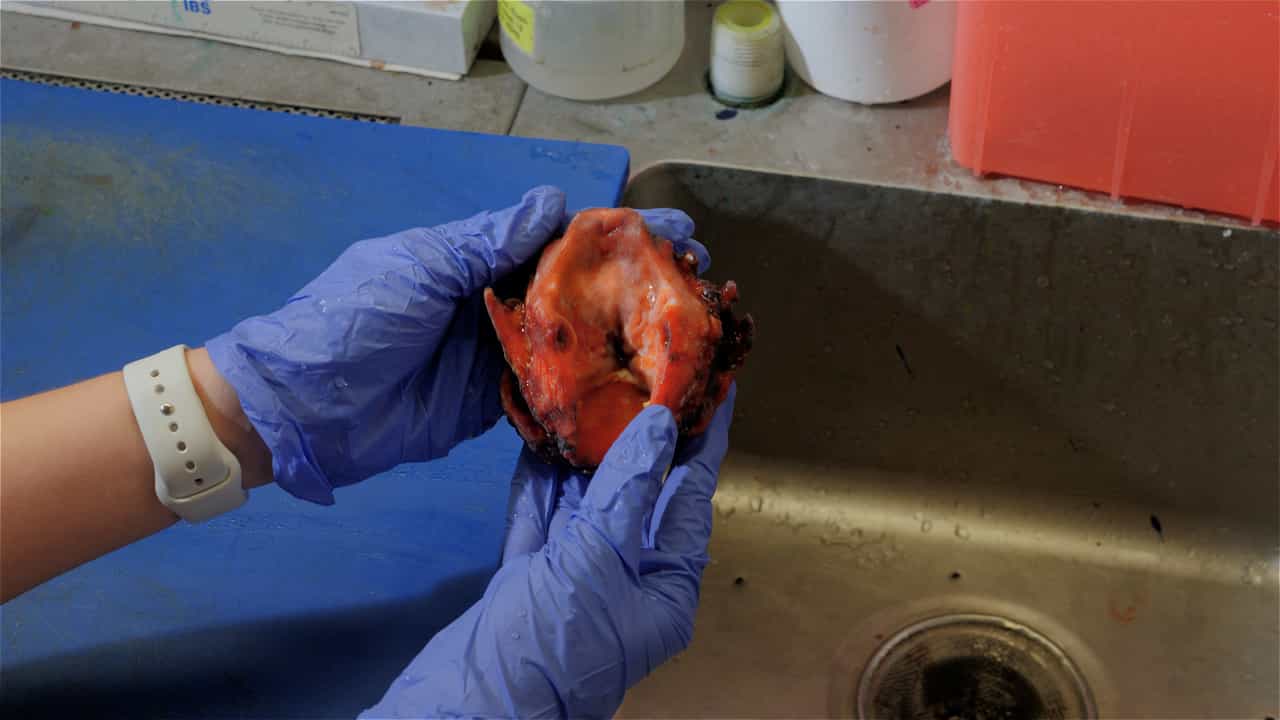

Enhanced Communication of Tumor Margins Using 3D Scanning and Mapping
Published on: December 15, 2023
Central Tumor Debulking in Mohs Micrographic Surgery: Technical Variations, Staging Utility, and Operational
1Department of Dermatology, Johns Hopkins University School of Medicine, Baltimore, Maryland.

Background:
Central tumor debulking typically precedes the initial stage in Mohs micrographic surgery (MMS) to facilitate tissue flattening and optimize margin evaluation.
Objective:
This review evaluates technical variations in debulking regarding tactile feedback, artifacts, laboratory processing, efficiency, and vertical staging.
Materials And Methods:
A structured search of MEDLINE and Scopus was conducted for literature published through June 2026.
Results:
Blunt curettage provides tactile feedback but leaves residual tumor in 76.0% of cases, creates jagged edges, and increases the risk of floaters. Sharp scalpel excision preserves vertical architecture for vertical staging and identifying high-risk features. Tangential shaving is well suited for superficial tumors on convex-site contours. Ex vivo debulking avoids jagged edges on complex free-margin sites. Omitting debulking preserves architectural continuity throughout the lesion depth but predisposes the specimen to splaying and chattering artifacts as well as missing epidermal edges. Only 81.9% to 85.4% of Mohs surgeons routinely perform a debulk when treating melanoma in situ, despite clear consensus guidelines and established vertical upstaging rates ranging from 2.3% to 8.1%.
Conclusion:
Technical variations in debulking directly affect the final slide quality, processing efficiency, and staging accuracy. Tailoring the debulking modality to specific tumor histology and anatomic site is essential to optimize both surgical efficacy and laboratory workflow.
