
Radiation stewardship in uniportal lumbar endoscopic decompression
Sahil Garg1,2, Patrick G Young1,2, Saqib Hasan3
11The Steadman Philippon Research Institute, Vail.

Objective:
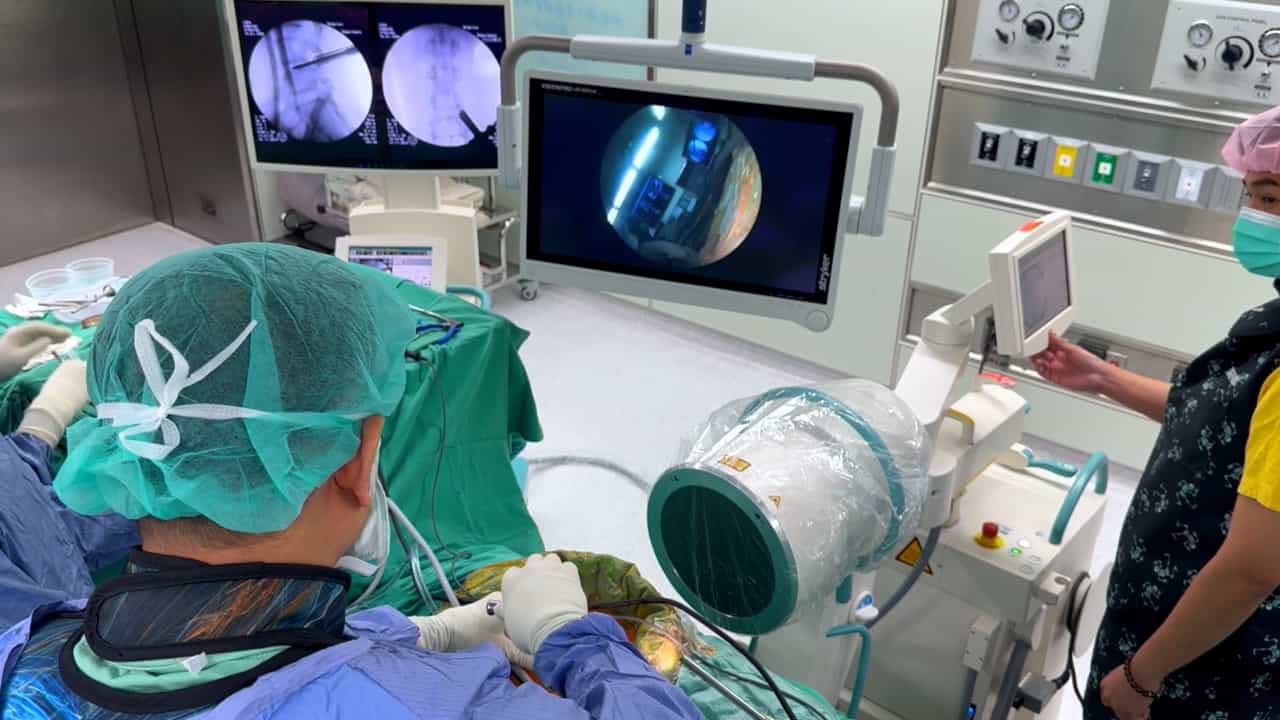
Uniportal lumbar endoscopic decompression is fluoroscopy-dependent, and the two dominant approaches, transforaminal and interlaminar, might impose distinct intraoperative targeting demands. Therefore, the aim of this study was to examine differences in radiation exposure based on technique and identify modifiable predictors beyond choice of approach.
Methods:
The authors identified 51 consecutive patients who underwent single-level uniportal lumbar endoscopic decompression with and without unilateral erector spinae blocks (ESBs). After excluding 4 with bilateral procedures, 2 with discography, and 1 with bilateral ESB, 44 patients remained for analysis (n = 16 transforaminal, n = 28 interlaminar). Of these, 38 received a single unilateral ESB, 4 received 2 ipsilateral ESBs, and 2 received none. Primary outcomes were intraoperative radiation dose (in milligrays), fluoroscopy time (in seconds), and operative duration. The Mann-Whitney U-test and Kruskal-Wallis test were used for group comparisons. A multivariable regression model was adjusted for approach, laterality, age, BMI, and the number of ESB injections.
Results:
Transforaminal cases had 1.8 times the radiation dose of interlaminar cases (median 11.48 vs 6.25 mGy, p < 0.001) and 2.4 times the fluoroscopy time (56 vs 23.5 seconds, p < 0.001). In the adjusted model (n = 44; R2 = 0.48, adjusted R2 = 0.42, F-test p < 0.0001), the transforaminal approach was an independent predictor of radiation dose [exp(β) = 1.83, 95% CI 1.25-2.69; p = 0.003], as was higher BMI [exp(β) = 1.067 per unit, 95% CI 1.02-1.11; p = 0.004]. In a restricted cohort limited to patients who received a single ipsilateral ESB, the transforaminal effect was preserved; in the overall cohort, interlaminar-specific BMI sensitivity was strong (ρ = 0.54, p = 0.003). The use of a second ESB trended toward an increase in cumulative radiation dose (95% CI 1.00-2.39, p = 0.051).
Conclusions:
Within a single-surgeon uniportal endoscopic practice, the transforaminal approach and higher BMI were independently associated with greater intraoperative radiation dose. Because the approach effect persisted after adjustment for patient and case factors, surgeons should consider BMI-sensitive technique refinement particularly for an interlaminar approach. While these findings require further validation in larger multisurgeon series, they suggest that approach selection should remain governed by the underlying pathology. The transforaminal radiation premium is best interpreted as a modifiable cost to be anticipated and mitigated rather than a reason to favor one corridor over another. Only in the subset of disc herniations amenable to either corridor does the lower radiation footprint of the interlaminar approach become a relevant secondary consideration.