Related Experiment Video
Updated: Oct 3, 2026
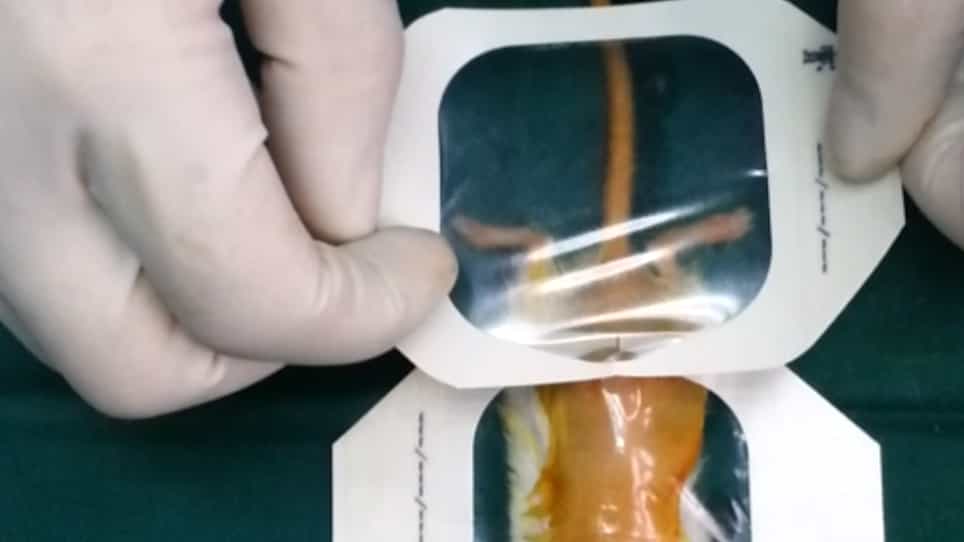

Comparing Metastatic Clear Cell Renal Cell Carcinoma Model Established in Mouse Kidney and on Chicken Chorioallantoic Membrane
Published on: February 8, 2020
Immunohistochemical profile of molecularly verified clear cell renal cell carcinomas
Kara S Tanaka1, Li Zhang2, Chien-Kuang Cornelia Ding1,3,4
1Department of Pathology, University of California San Francisco, San Francisco, California, USA.

Background:
Immunohistochemical (IHC) features of clear cell renal cell carcinomas (CCRCC) have historically been defined by morphologically selected tumours, but aberrant staining patterns that may confound the diagnosis are common. Recent studies have described the prognostic significance of architectural patterns in CCRCC and have proposed grading schemes based on morphology. We investigate a cohort of molecularly verified CCRCC to evaluate their IHC profiles and correlate with architectural patterns and key driver molecular alterations.
Methods:
Renal cell carcinomas (RCCs) sequenced at our institution between January 2015 and June 2024 by NGS assay were reviewed to identify CCRCCs based on VHL alterations and/or 3p loss. Architectural patterns were classified into low grade (LG) (nested, cystic), intermediate grade (IG) (tubular, tubulopapillary, alveolar), and high grade (HG) (fused nests/solid sheets, rhabdoid, sarcomatoid, low-grade spindled, pleomorphic tumour giant cells), based on findings from recent studies and scored based on highest-grade pattern. IHC staining for CA9, KER7, PAX8, and CD10 were reviewed for percent staining (focal 25% or less, moderate 26%-50%, diffuse greater than 50%). Correlation of aberrant staining with primary/metastatic status, architectural patterns, and molecular alterations was analysed.
Results:
125 cases of molecularly verified CCRCC were identified and 108 cases with concurrent IHC met inclusion criteria, including 54 primary and 54 metastatic tumours. KER7 positivity was more common in primary vs. metastatic tumours (45% vs. 13%, P = 0.001), in tumours with LG/IG architectural patterns (67% LG and 67% IG vs. 17% HG, P = 0.002) and in PBRM1 wild type (WT) tumours (84% PBRM1 WT vs. 16% PBRM1 mutated, P = 0.021). Negative CA9 staining occurred only in metastatic tumours (15%). PBRM1 mutated tumours were more likely to be KER7-/CA9+/PAX8-, while BAP1 mutated tumours were more likely to have higher-grade architectural patterns and lack CD10 expression.
Conclusions:
In this cohort of molecularly verified CCRCCS, positive KER7 staining was seen in 30% of tumours with diffuse strong staining in 16%. The IHC profiles correlated with both morphological features and genetic alterations.