Related Experiment Video
Updated: Oct 7, 2026

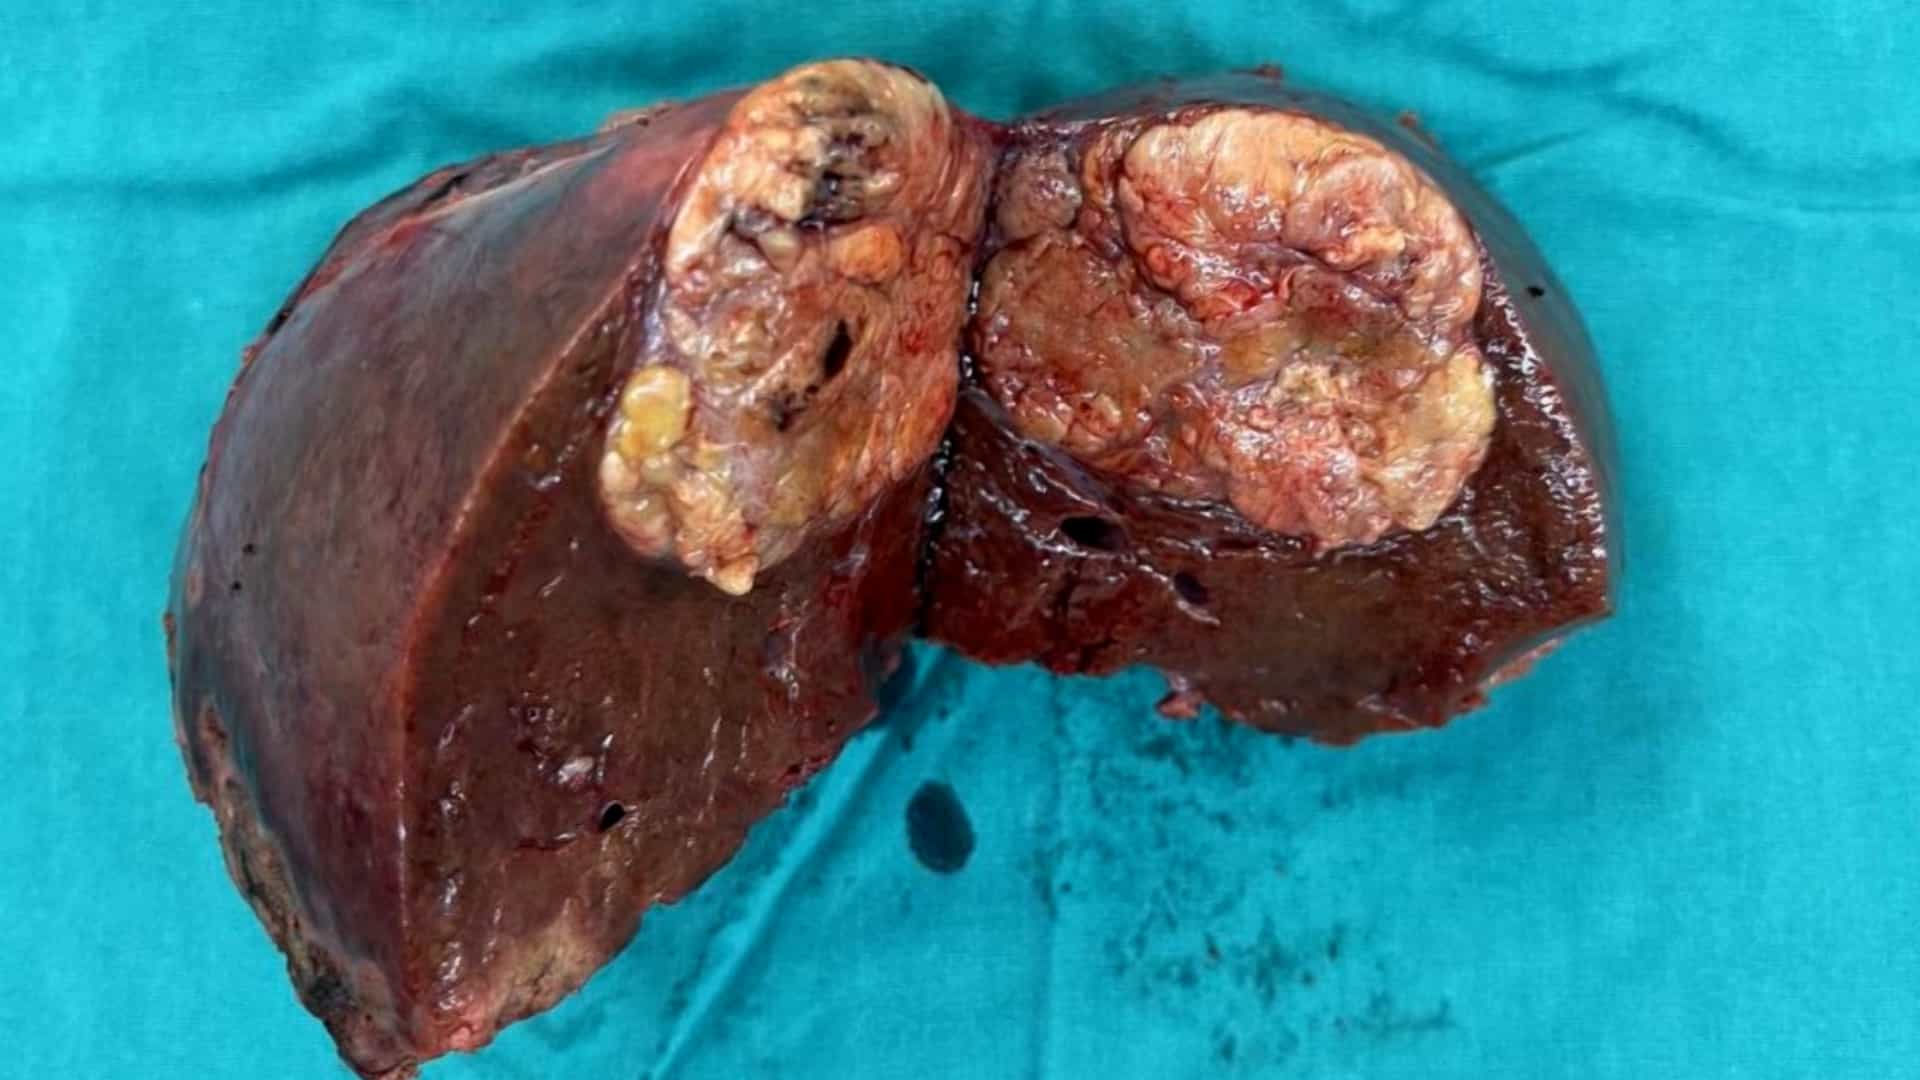
Application of the En Bloc Concept Combined with Anatomic Resection in Laparoscopic Hepatectomy
Published on: March 10, 2023
Optimal timing of surgery after conversion therapy for initially unresectable hepatocellular carcinoma: a multicenter
Siming Li1,2, Minjun Li1, Fan Zhu3
1Department of Hepatobiliary Surgery, Guangxi Liver Cancer Diagnosis and Treatment Engineering and Technology Research Center, Guangxi Medical University Cancer Hospital, Nanning, China.

Objective:
The optimal timing of surgery after conversion therapy for initially unresectable hepatocellular carcinoma (uHCC) remains unclear. This study aimed to evaluate whether surgical timing can be optimized by integrating major pathological response (MPR), defined as residual viable tumor (RVT) ≤15%, with preoperative treatment duration.
Methods:
This multicenter retrospective study enrolled patients with initially uHCC who underwent curative-intent hepatectomy after comprehensive conversion therapy at seven tertiary hospitals between January 2020 and December 2025. The prognostic cutoff for MPR was determined using restricted cubic spline (RCS) models. Patients were categorized into three groups according to the interval from initiation of conversion therapy to surgery: <12 weeks, 12-24 weeks, and >24 weeks. MPR rates, survival outcomes, and perioperative safety were compared among the three groups.
Results:
A total of 257 patients were included. RCS analysis showed that a higher RVT proportion was associated with increased risks of poor overall survival (OS) and recurrence-free survival (RFS), with the most pronounced change in risk observed at an RVT threshold of 15%. Therefore, RVT ≤15% was defined as MPR in this study. The overall MPR rate was 63.4% (163/257). MPR was an independent protective factor for both OS and RFS. The MPR rate increased progressively with longer treatment duration (41.3% in the <12-week group, 66.2% in the 12-24-week group, and 73.0% in the >24-week group). OS differed significantly among the three duration groups, whereas the difference in RFS was not statistically significant. The incidences of severe postoperative complications and high-grade adverse events were low across all groups and did not increase markedly with prolonged therapy.
Conclusions:
RVT ≤15% may serve as a prognostically meaningful criterion for MPR after conversion therapy for uHCC. To balance the degree of pathological response, long-term survival benefit, and perioperative safety, a treatment-to-surgery interval of 12 to 24 weeks may be optimal.