Related Experiment Video
Updated: Oct 8, 2026
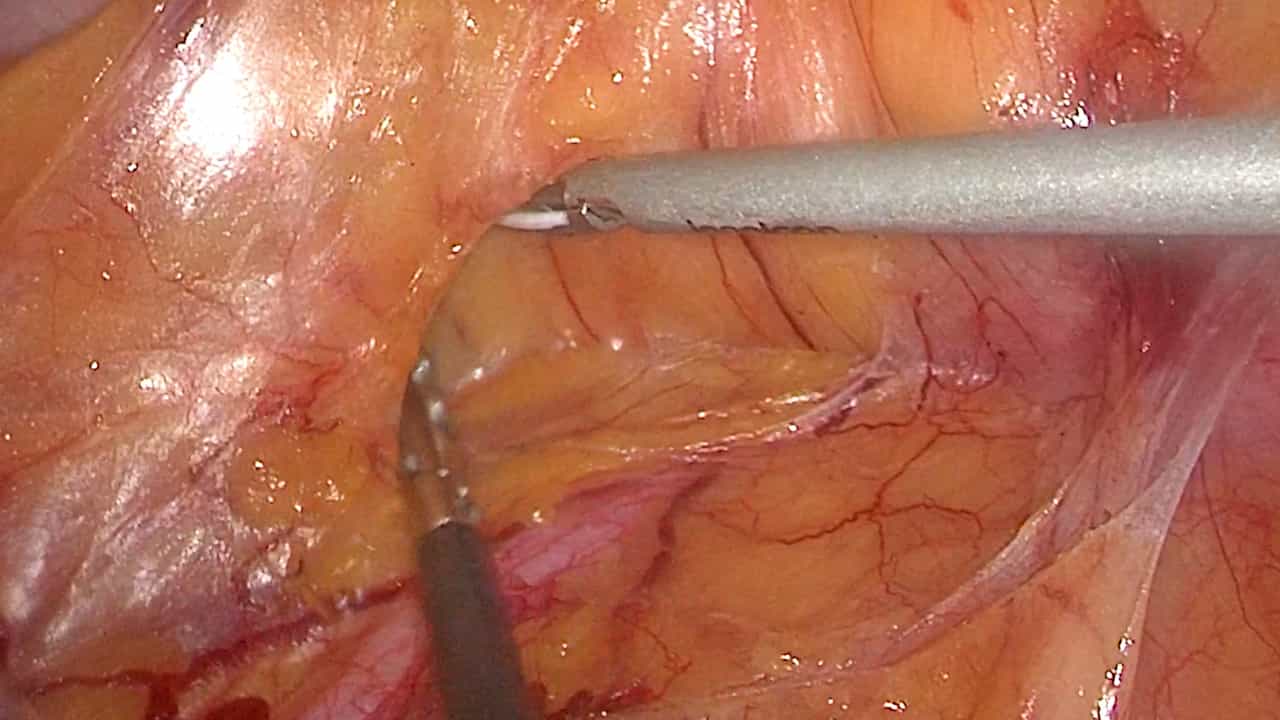

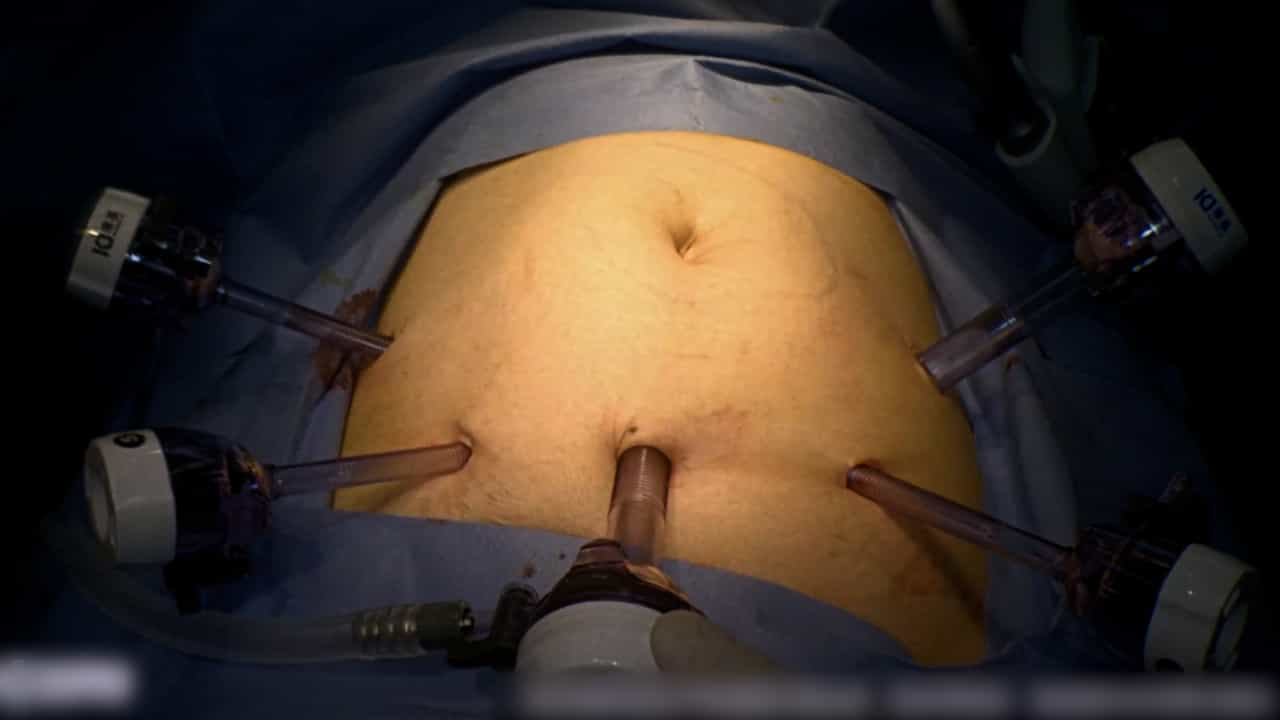
Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Minimally invasive versus open emergency right-sided colectomy for malignant obstruction: a nationwide propensity
Erik Agger1,2, Peter Matthiessen3,4, Tomas Vedin5,6
1Department of Surgery, Skåne University Hospital, Malmö, SE-214 21, Sweden. erik.agger@med.lu.se.

Background:
Minimally invasive surgery (MIS) improves short-term outcomes in elective colectomy, however, the choice of surgical approach in hemodynamically stable patients with obstructing right-sided colon cancer remains unclear in emergency settings. MIS could be considered and the present study aims to evaluate short-term outcomes of MIS in bowel obstructed patients compared with open surgery (OPEN).
Methods:
A retrospective nationwide study including patients from the nationwide Swedish Colorectal Cancer Registry (SCRCR) undergoing emergency right-sided colectomy in Sweden (2017-2023) was conducted. Propensity score matching (1:1) was performed based on sex, age, ASA class, hospital size, and operative timing (on-call vs. daytime). Outcomes included length of stay (LOS), postoperative complications, and surgical quality indicators. Analysis was performed according to intention-to-treat.
Results:
A total of 1147 patients were identified. Of the 1,147 included patients, 99 (8.6%) underwent an initially minimally invasive approach. After matching, 99 patients remained in each group. The conversion rate was 34%. Median LOS was 9 days (IQR 6;14) after OPEN and 6 days (IQR 5;10) after MIS. In quantile regression with bootstrap standard errors, MIS was associated with a 3-day shorter median LOS (median difference - 3.0 days, 95% CI - 4 to - 2, p = 0.002). Postoperative complications (Clavien-Dindo ≥ 2) occurred in 38.8% after OPEN and in 23.2% after MIS. Logistic regression analysis with robust standard errors showed significantly lower odds of postoperative complications after MIS (OR 0.48, 95% CI 0.27-0.83, p = 0.009). No significant differences were observed in re-admission, 90-day mortality, R0 resection, lymph node yield, blood loss or operative time.
Conclusion:
In this nationwide observational cohort, an initially minimally invasive approach was associated with shorter length of stay and fewer postoperative complications. No statistically significant differences were observed in the available short-term surgical and pathological quality indicators. Given the limited number of MIS procedures and potential for residual confounding, these findings support further evaluation of MIS in carefully selected patients.