Related Experiment Video
Updated: Oct 13, 2026
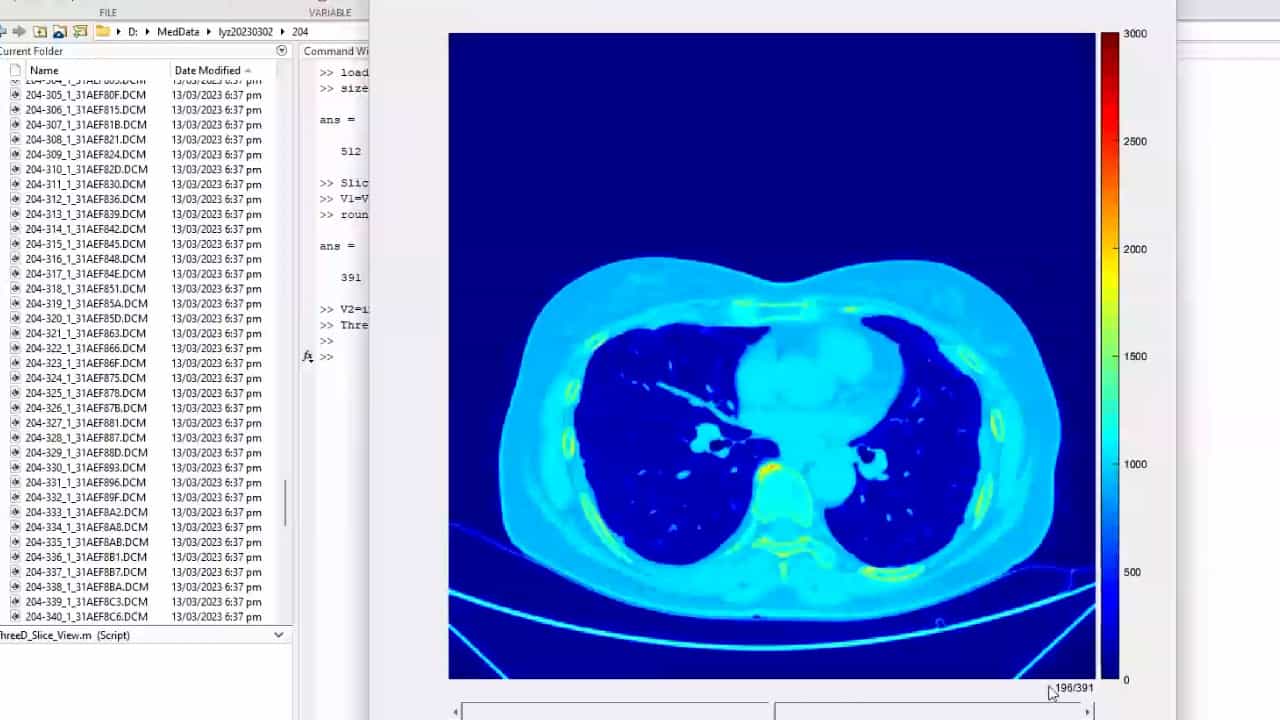

Three-Dimensional Reconstruction for the Whole Lung with Early Multiple Pulmonary Nodules
Published on: October 13, 2023
Automated triage to a virtual lung nodule clinic using veye lung nodule volumetry provides a cost saving compared to
Giles Dixon1,2, Vruti Dattani3, Vidan Masani1
1Department of Respiratory Medicine, Royal United Hospitals Bath NHS Foundation Trust, Bath, BA13NG, United Kingdom.

Objectives:
Pulmonary nodules are frequently identified on thoracic CT imaging, with management guided by established clinical pathways. Thoracic CT scans are reported by both specialist and general radiologists. This study evaluated discordance in pulmonary nodule identification and management between general and specialist radiologists and modeled automated triage to a virtual nodule clinic (VNC).
Methods:
All CT scans, including the thorax, performed over a 1-week period at a single UK center in March 2022 were identified and original reports reviewed. Oncology follow-up scans were excluded. Reports were categorized and compared with an independent second expert radiologist review. VNC triage pathways were modeled to select patients for second review by an expert radiologist. The pathways used combinations of original radiologist reports and automated nodule assessment (DeepHealth Ltd) to trigger VNC review. The cost implications of each pathway were calculated.
Results:
Among 243 CT scans, 98 (40%) original reports identified a pulmonary nodule. Expert review identified incorrect recommendations in 24/243 (10%) cases. Errors were significantly more frequent in reports issued by general radiologists compared with specialist thoracic radiologists (χ² ∼ 11.0, df = 2, P < .05). VNC triage pathways that selected cases for secondary review when automated nodule assessment failed to identify a nodule that was identified by the reporting radiologist resulted in the greatest cost savings per corrected nodule.
Conclusion:
Approximately 10% of thoracic CT scans contained errors in pulmonary nodule reporting. Cost-saving triage pathways combining non-specialist reporting with automated nodule assessment appear feasible and warrant prospective real-world validation.
Advances In Knowledge:
This study demonstrates theoretical clinical implementation of semi-automated triage to a virtual nodule clinic and provides an evidence base for prospective study.
