Related Experiment Video
Updated: Oct 13, 2026

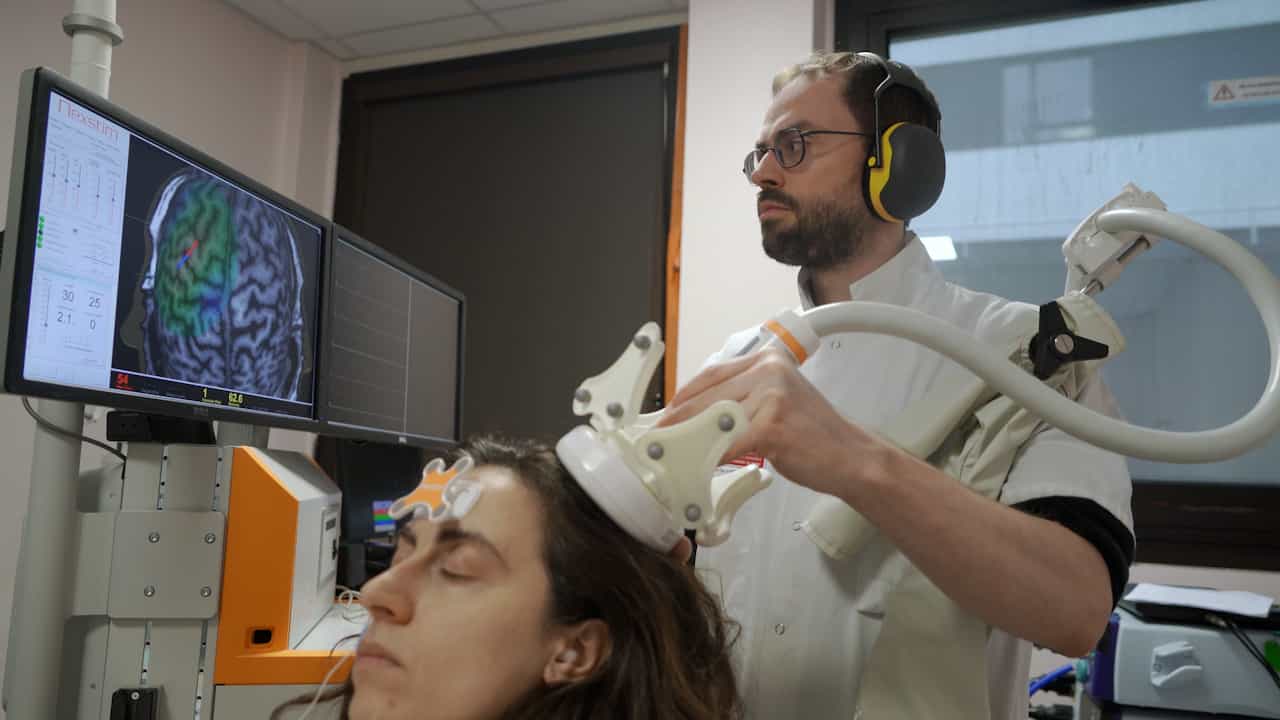
Translational Brain Mapping at the University of Rochester Medical Center: Preserving the Mind Through Personalized Brain Mapping
Published on: August 12, 2019
Passive intraoperative motor fMRI under general anesthesia during open-craniotomy glioma surgery: a prospective
Jonathan Wais1, Julia Shawarba1, Vitalij Zeiser1
1Dept. of Neurosurgery, Medical University of Vienna, Vienna, Austria.

Introduction:
Sensorimotor localization is important during peri-Rolandic glioma surgery. We assessed passive intraoperative motor functional MRI (pifMRI) under general anesthesia.
Research Question:
Can pifMRI provide useable sensorimotor maps before and after resection for neuronavigation and comparison with cortical stimulation?
Material And Methods:
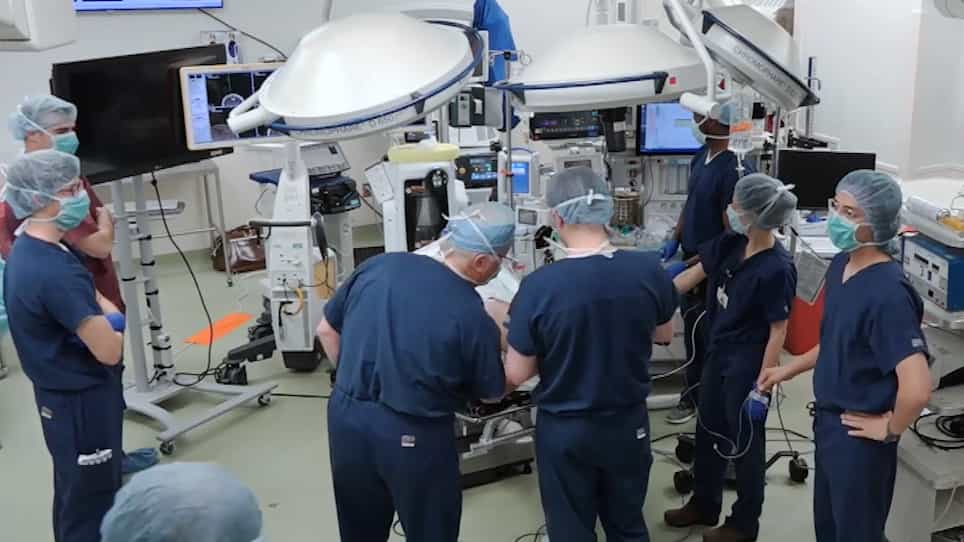
Eight adults (24-72 years; median, 57.5) underwent pifMRI intraoperatively in a two-room 3-T intraoperative MRI setting. With cranium open, blood oxygen level-dependent signals were elicited by passive flexion-extension of digits II-V. Maps were integrated into neuronavigation and used for corticospinal tract tractography. Given the exploratory sample and absent systematic coordinate-level recording, analyses were descriptive.
Results:
Useable activation in the primary sensorimotor region was obtained in all patients. Stimulation at pifMRI-defined regions elicited motor responses in all patients. However, negative sites and coordinate-level distances were not recorded, precluding diagnostic-accuracy and distance analyses. Post-resection pifMRI was obtained in seven patients. Median tumor volume decreased from 17.05 to 2.78 cm3; median extent of resection was 84.5% (range, 44%-100%). Six patients developed new or worsened deficits; five recovered fully and one improved by 3 months. All five patients with preoperative focal motor seizures were Engel Ia at 3 months, an uncontrolled observation not attributable to pifMRI. Mean imaging time was 48 min 45 s; each pifMRI acquisition lasted about 5 min.
Discussion And Conclusions:
This prospective series supports the feasibility of acquiring and integrating pifMRI during glioma surgery, including after resection. Correspondence with positive stimulation sites is hypothesis-generating with no quantitative validation of mapping accuracy or clinical efficacy.