Related Experiment Video
Updated: Oct 14, 2026

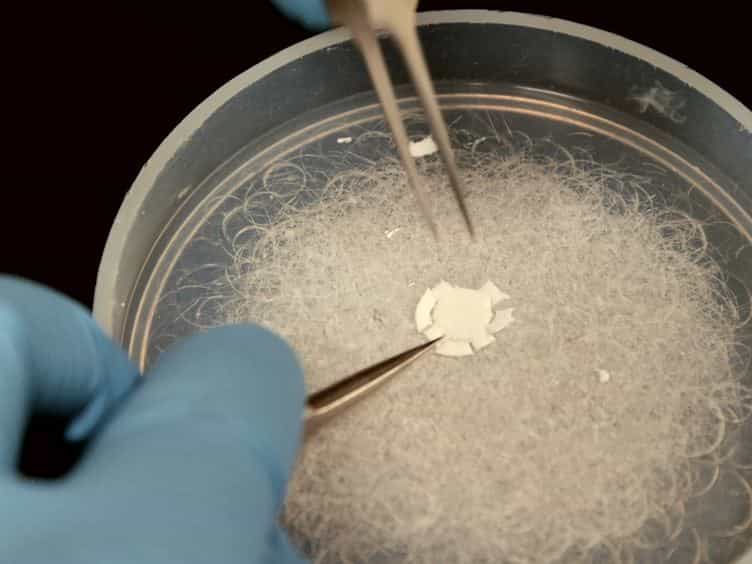
Synthetic, Multi-Layer, Self-Oscillating Vocal Fold Model Fabrication
Published on: December 2, 2011
Clinical Utility of Aerodynamic Measures in Vocal Fold Augmentation Outcomes
Kelly Zdrowak1, Ammar A Rashied2, Andrew Tkaczuk1
1Department of Otolaryngology Head and Neck Surgery, Emory University School of Medicine, Atlanta, Georgia.

Objective:
Glottic insufficiency can result in respiratory-laryngeal dysfunction that contributes to dysphonia. Instrumental assessments complement patient- and clinician-reported evaluations. Aerodynamic measurements provide quantitative data to characterize phonatory function. This study aimed to determine whether preoperative phonatory aerodynamic measures are associated with outcomes following vocal fold medialization for glottic insufficiency.
Methods:
A retrospective review of patients who underwent injection laryngoplasty or type 1 thyroplasty at the Emory Voice Center from 2022 to 2024 was analyzed for baseline and postprocedure phonatory aerodynamic measures (mean airflow during voicing [MADV]), breaths while speaking, speaking duration, and patient-reported outcomes (voice handicap index-10) to assess changes across procedures (N = 98). Patients underwent one or multiple procedures, but data were not stratified by type or sequence.
Results:
Patients who underwent a second augmentation procedure had significantly higher baseline MADV (M = 0.49 L/s, SD = 0.25) than those who had one procedure (M = 0.32 L/s, SD = 0.23; P = 0.01), and took fewer breaths to read a standard passage from baseline (M = 13.1, SD = 7.2) to post-procedure 1 (M = 9.9, SD = 4.5; P = 0.02) than the 1-procedure cohort. Across groups, VHI-10 scores improved from baseline (M = 29.9, SD = 8.7) to postprocedure 1 (M = 21.6, SD = 10.7; P = 0.0008), and further after procedure 2 (M = 10.9, SD = 10.5; P = 0.02).
Conclusion:
Higher baseline MADV was linked to requiring multiple procedures, suggesting it may help predict the number needed to achieve glottic sufficiency. Post-treatment improvements in airflow and the number of breaths while speaking highlight the clinical value of aerodynamic assessments in planning and evaluating intervention outcomes.
Level Of Evidence:
Level III.

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids, corniculates, and...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques