Related Experiment Video
Updated: Oct 14, 2026
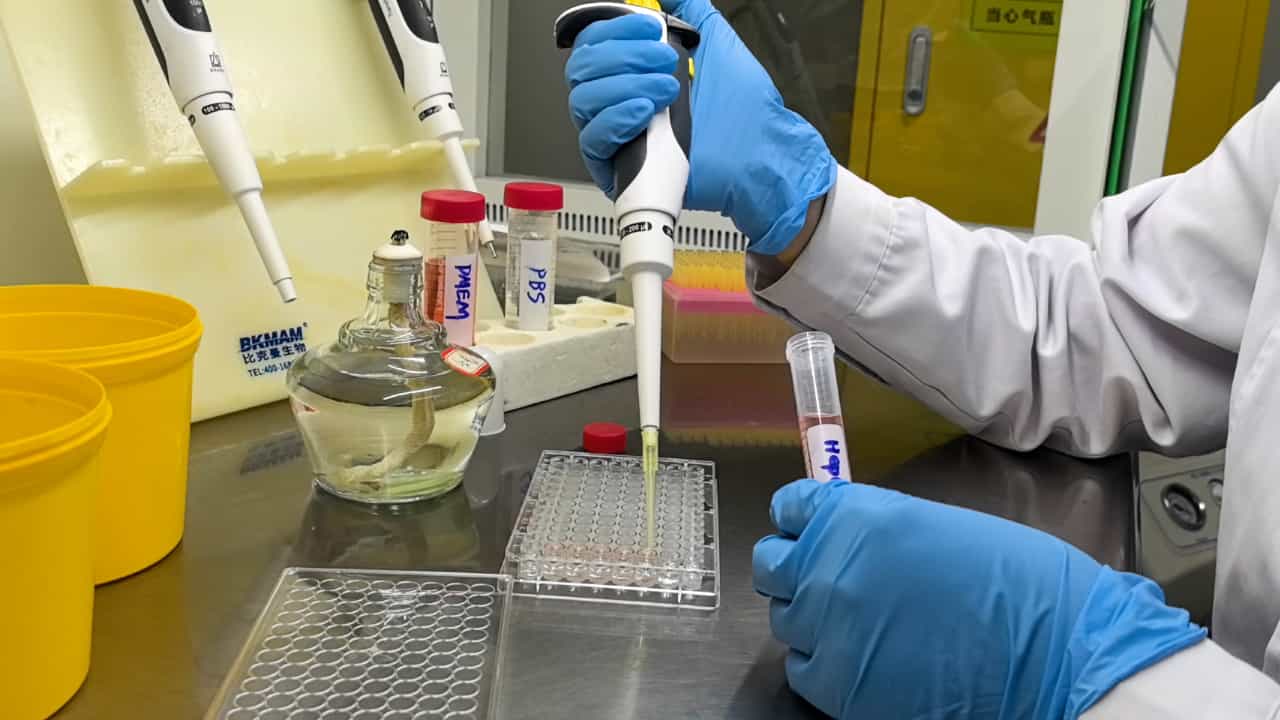
In Vitro Modeling of Fat Deposition in Metabolic Dysfunction-Associated Steatotic Liver Disease
Published on: July 19, 2024
The liver-muscle axis in metabolic dysfunction-associated steatotic liver disease: a narrative review and conceptual
Zhendong Ma1, Xinri Zhang1, Yan Leng2
1College of Traditional Chinese Medicine, Changchun University of Traditional Chinese Medicine, Changchun, Jilin, China.

Abstract:
Metabolic dysfunction-associated steatotic liver disease (MASLD) exhibits substantial phenotypic heterogeneity, yet pathways centered on body mass index (BMI) and liver non-invasive tests (NITs) do not adequately identify reduced metabolic reserve, functional vulnerability, or the risk of treatment-related muscle loss. This review aims to delineate the conceptual boundaries among sarcopenic obesity (SO), non-obese sarcopenia, and myosteatosis; evaluate their mechanistic, histological, and prognostic relationships with MASLD; compare body-composition assessment tools; and propose a body composition risk characterization framework for future validation. A formal diagnosis of SO should not be based on a mechanical combination of BMI and a single muscle mass threshold, but should concurrently establish excess adiposity, impaired muscle function, and reduced skeletal muscle mass/quantity confirmed by body-composition assessment. Current evidence indicates that low muscle mass, low muscle strength, and myosteatosis are associated with metabolic dysfunction-associated steatohepatitis (MASH), liver fibrosis, and adverse outcomes, although observational associations remain influenced by reverse causation, physical activity, visceral adiposity, and disease stage. Compartment-specific apolipoprotein J (ApoJ/clusterin) signaling illustrates liver-to-muscle endocrine communication and context-dependent intrahepatic or remote-organ effects. We propose four muscle phenotypes: phenotype A, preserved muscle function/quantity without myosteatosis; phenotype B, isolated myosteatosis; phenotype C, abnormal muscle function and/or quantity without myosteatosis; and phenotype D, coexisting abnormalities in muscle function/quantity and myosteatosis. Excess adiposity is treated as an independent modifying axis, and phenotypes C or D are considered SO-related only when excess adiposity is independently confirmed and formal SO criteria are fulfilled, thereby avoiding the misclassification of non-obese sarcopenia as SO. The model is intended for validation in a multicenter prospective biopsy cohort using centrally reviewed, blinded liver histology as the reference for MASH and fibrosis, with its incremental value assessed beyond the fibrosis-4 index (FIB-4), vibration-controlled transient elastography (VCTE), the enhanced liver fibrosis (ELF) test, or magnetic resonance elastography (MRE). Body-composition assessment should complement rather than replace liver NITs, and the four-phenotype classification, selective clinical pathway, and dual liver-muscle endpoint framework remain conceptual, hypothesis-generating tools that require histological, longitudinal-outcome, and clinical-utility validation.
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can also...
 01:24
Cirrhosis II: Pathophysiology
 01:27
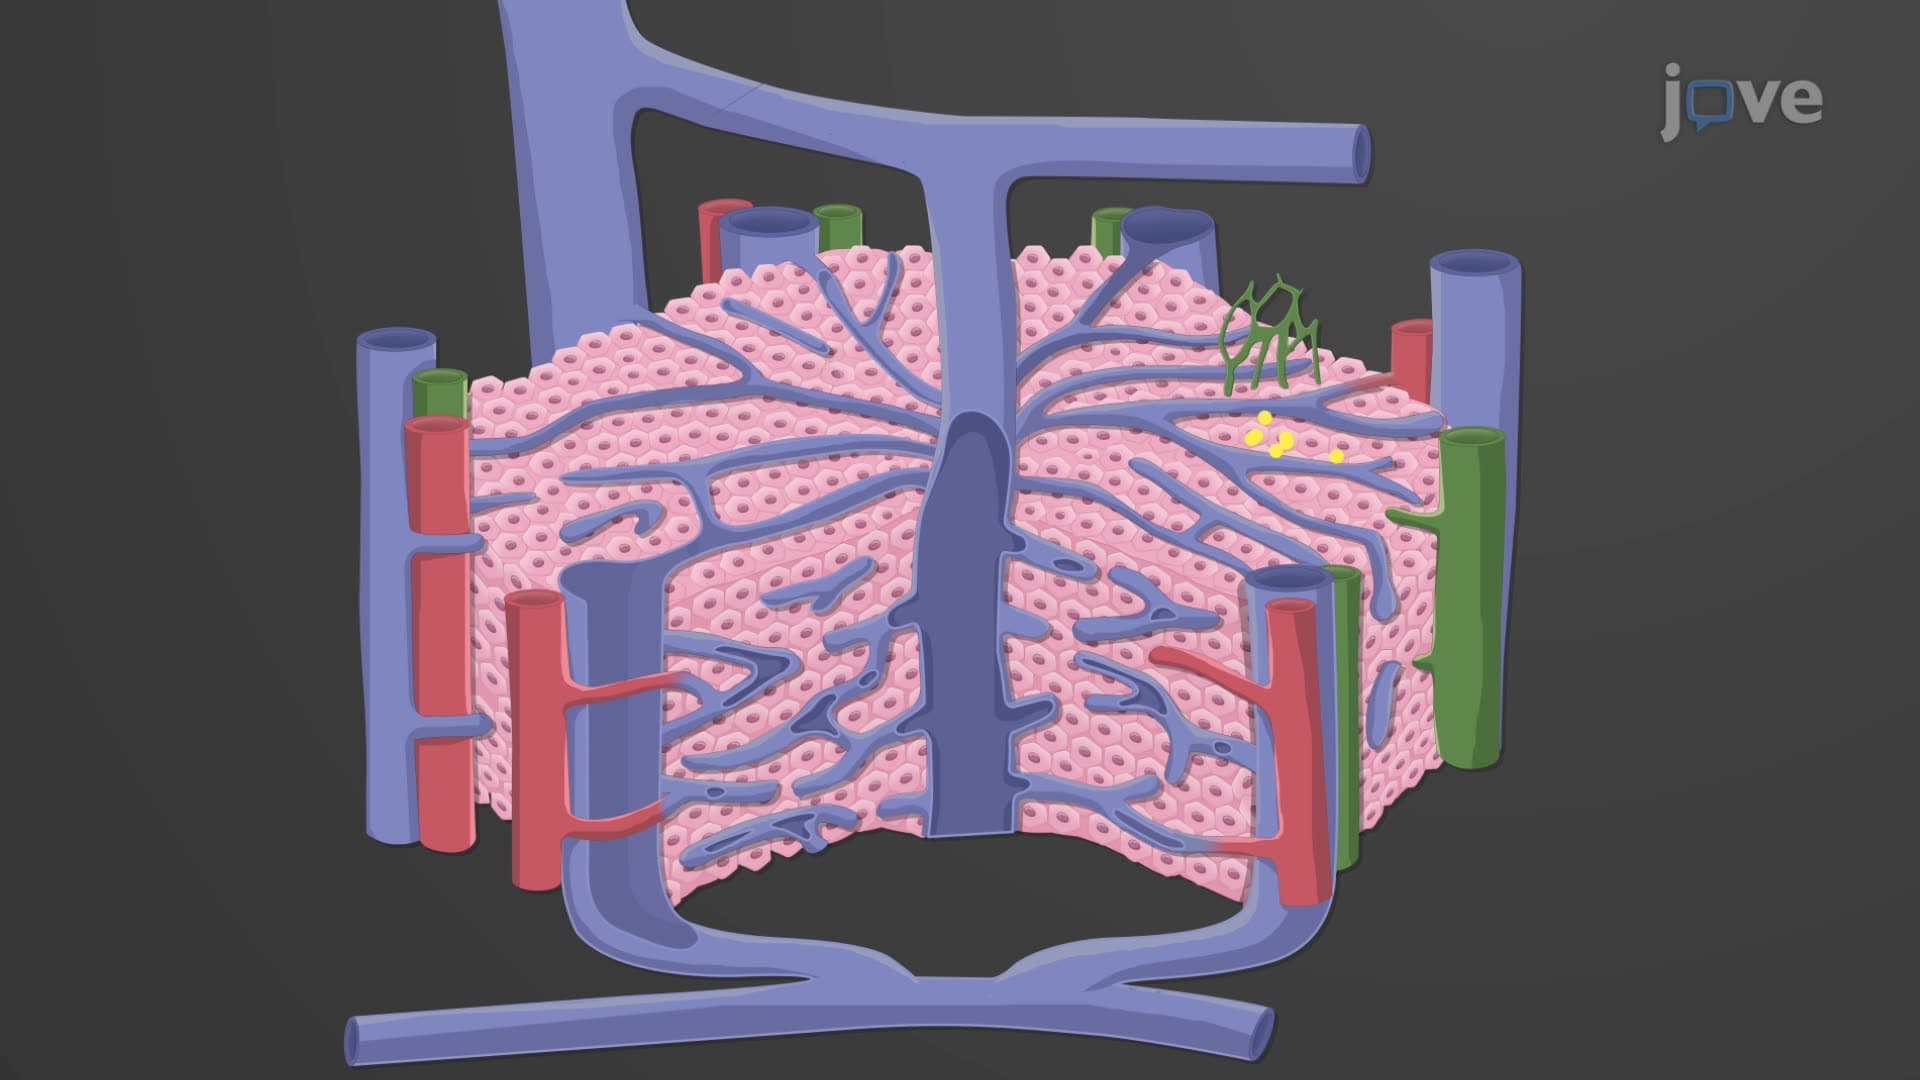
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:23
Cirrhosis I: Introduction