Related Experiment Video
Updated: Oct 18, 2026
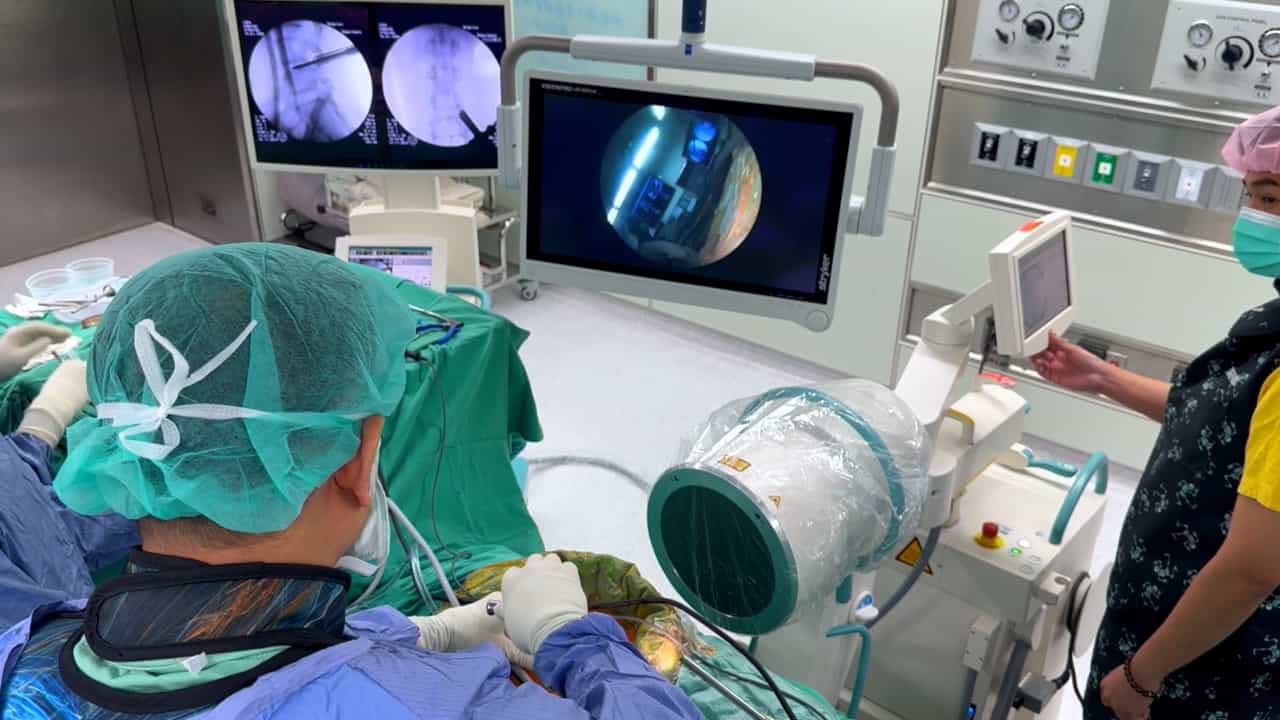
Uniportal Full Endoscopic Posterolateral Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Arthroscopic-assisted uniportal spinal surgery with bone-anchored annular repair for far lateral lumbar disc
Hao Cao1, Xin Zhang1, Shili Chen1
1Orthopedics, Kunming Orthopedic Hospital, Kunming, Yunnan, China.

Rationale:
Far lateral lumbar disc herniation (FLLDH) is technically challenging because of its foraminal or extraforaminal location. Arthroscopic-assisted uniportal spinal surgery (AUSS) with bone-anchored annular repair has previously been described for lumbar disc herniation, but its use through an extraforaminal corridor for FLLDH has not been specifically detailed.
Patient Concerns:
A 50-year-old woman presented with a 4-month history of refractory lumbosacral and gluteal pain, followed by acute right lower-extremity radicular pain along the L3-L4 dermatome. Walking was limited to <20 minutes. Her leg-pain visual analog scale (VAS) score was 7, and her Oswestry Disability Index (ODI) was 45/50 (90%) despite conservative treatment.
Diagnoses:
Computed tomography and magnetic resonance imaging demonstrated a right-sided far-lateral L3-L4 disc herniation with foraminal stenosis and compression of the exiting L3 nerve root. Dynamic radiographs showed no segmental instability.
Interventions:
The patient underwent AUSS-assisted far lateral discectomy under general anesthesia through a 1.5 to 2.0-cm extraforaminal incision. Foraminal decompression, removal of the herniated nucleus pulposus, and bone-anchored annular repair were performed through the same uniportal approach.
Outcomes:
The operation lasted 45 minutes, with an estimated blood loss of approximately 10 mL. No perioperative complications were documented. The leg-pain VAS score decreased from 7 to 1, and the ODI decreased from 45/50 (90%) to 10/50 (20%). Postoperative day 1 imaging confirmed removal of the herniated fragment and adequate decompression of the exiting L3 nerve root. At the 15-month telephone-only follow-up, the patient-reported leg-pain VAS score was 0 and the ODI was 8/50 (16%); no physical examination or interval imaging was obtained.
Lessons:
This case demonstrates the technical feasibility of performing decompression and bone-anchored annular repair for FLLDH through an extraforaminal AUSS corridor. The contribution is the anatomical and procedural application of a previously described repair concept rather than the introduction of a new repair technique. Because the 15-month follow-up was telephone-based and lacked neurological examination and interval imaging, this report does not establish structural healing, recurrence prevention, long-term safety, comparative effectiveness, or superiority.