Related Experiment Video
Updated: Oct 19, 2026
Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
Right ventricular strain analysis in acute pulmonary embolism and its role for late complications
Ioannis T Farmakis1,2,3, Lina-Marie Brandes3, Karsten Keller1,3
1Center for Thrombosis and Hemostasis (CTH), University Medical Center of the Johannes Gutenberg University, 55131 Mainz, Germany.

Aims:
Acute pulmonary embolism (PE) can result in long-term complications, including post-PE impairment (PPEI) and chronic thromboembolic pulmonary hypertension (CTEPH). Right ventricular global longitudinal strain (RVGLS) is a sensitive measure of RV myocardial deformation that may detect subclinical dysfunction and predict adverse outcomes; however, its value in the follow-up of post-PE assessment has not been yet elucidated.
Methods And Results:
In this prospective sub-study of the FOCUS cohort, 175 consecutive PE survivors from the Mainz centre underwent echocardiographic follow-up at 3 and 12 months, including speckle-tracking assessment of RVGLS, RV free wall strain (RVFWLS), and strain-derived ventriculoarterial coupling indices. Conventional RV parameters, volumetric measures, and clinical outcomes were recorded. Overall, 175 patients were included, of whom 16 developed PPEI or CTEPH during follow-up. RV function improved over time in patients without PPEI/CTEPH, including increases in RVGLS (from -16 to -18%), RVFWLS, ejection fraction, and strain-based ventriculoarterial coupling, accompanied by reductions in RV volumes. In contrast, patients who developed PPEI/CTEPH (n = 16) displayed progressive deterioration of RV strain and strain-derived coupling despite relatively preserved TAPSE-based indices. At 3 months, RVGLS was significantly associated with the combined PPEI/CTEPH endpoint over 2 years (OR 1.10, 95% CI 1.01-1.21), whereas strain-derived ventriculoarterial coupling parameters demonstrated borderline associations [RVGLS/systolic pulmonary artery pressure (sPAP): OR 0.11, 95% CI 0.01-0.91; RVFWLS/sPAP: OR 0.16, 95% CI 0.02-1.17]. TAPSE/sPAP was not associated with the outcome.
Conclusion:
RV strain and strain-derived ventriculoarterial coupling may provide sensitive early markers of maladaptive RV remodelling after acute PE and were associated with the development of PPEI/CTEPH, highlighting their potential value in post-PE follow-up strategies.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Pulmonary Embolism I: Introduction
 01:19
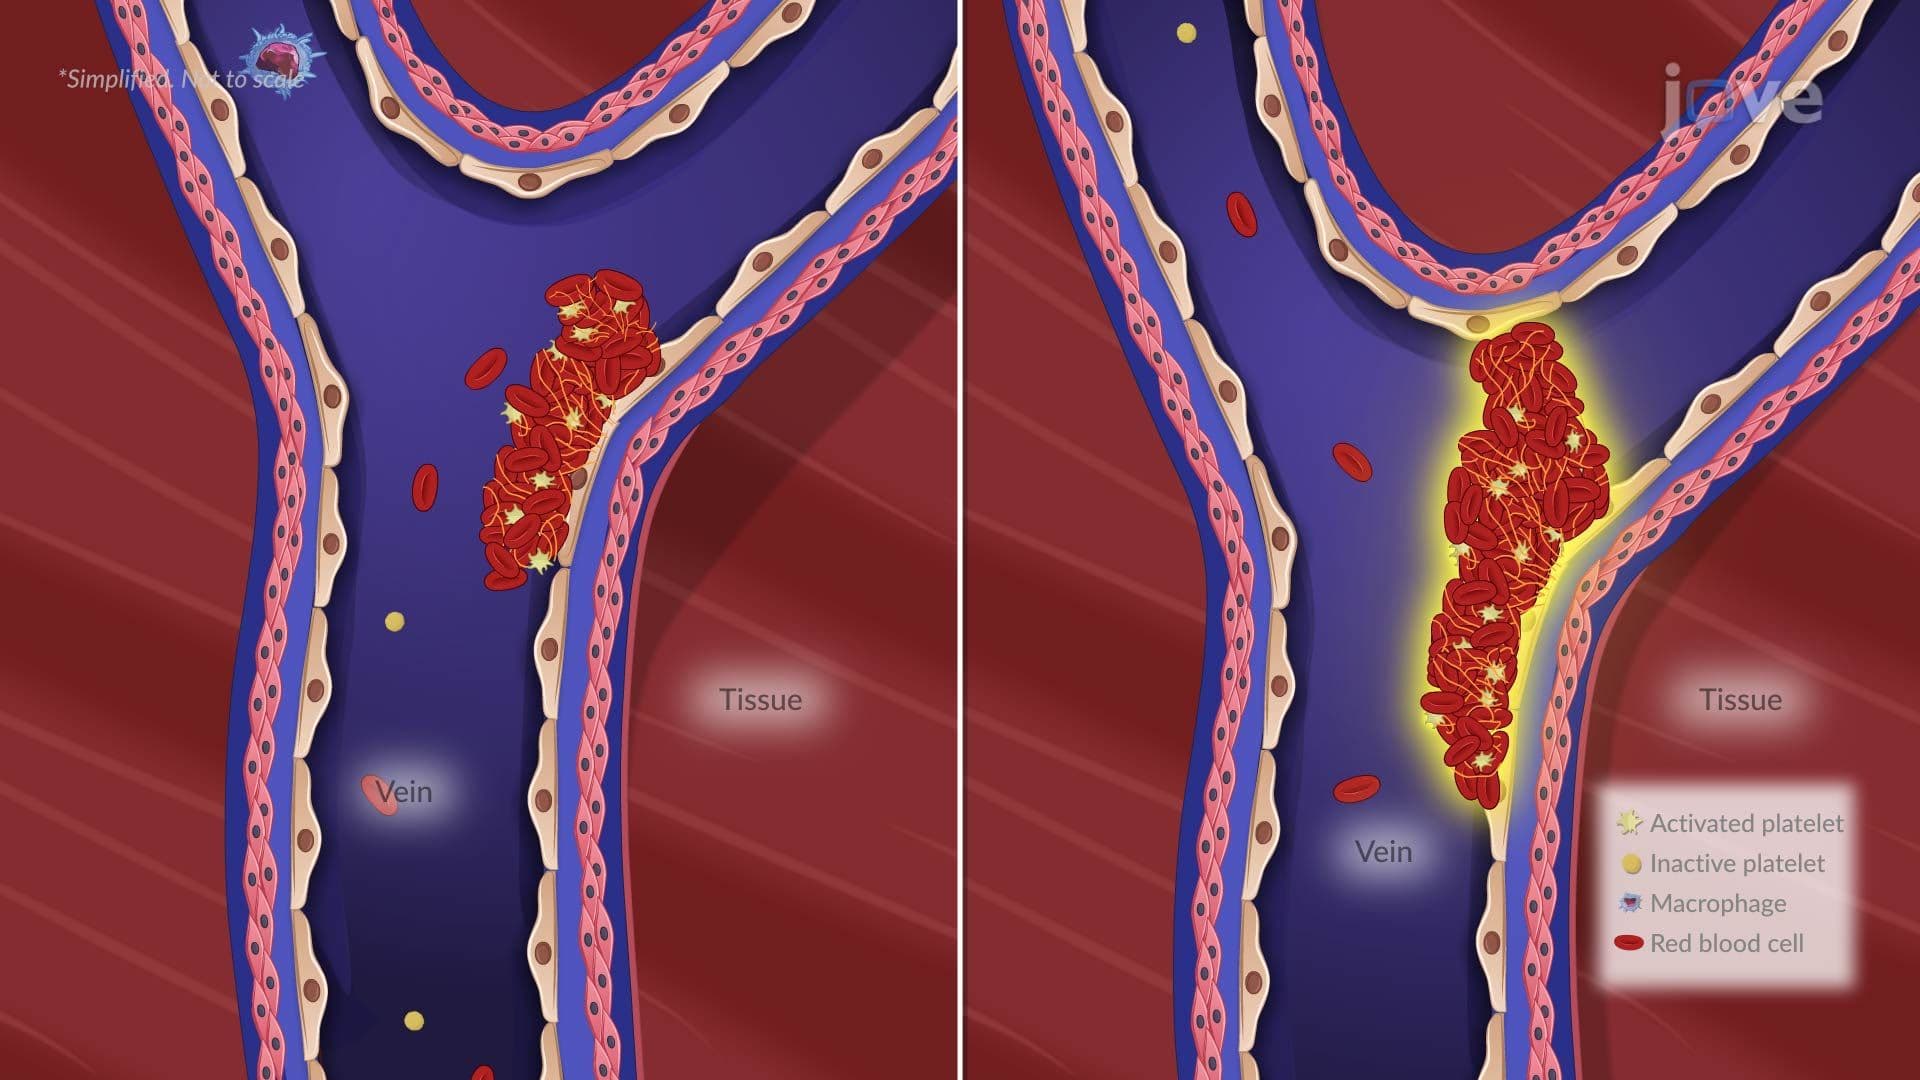
Pulmonary Embolism I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies