Related Experiment Video
Updated: Oct 19, 2026
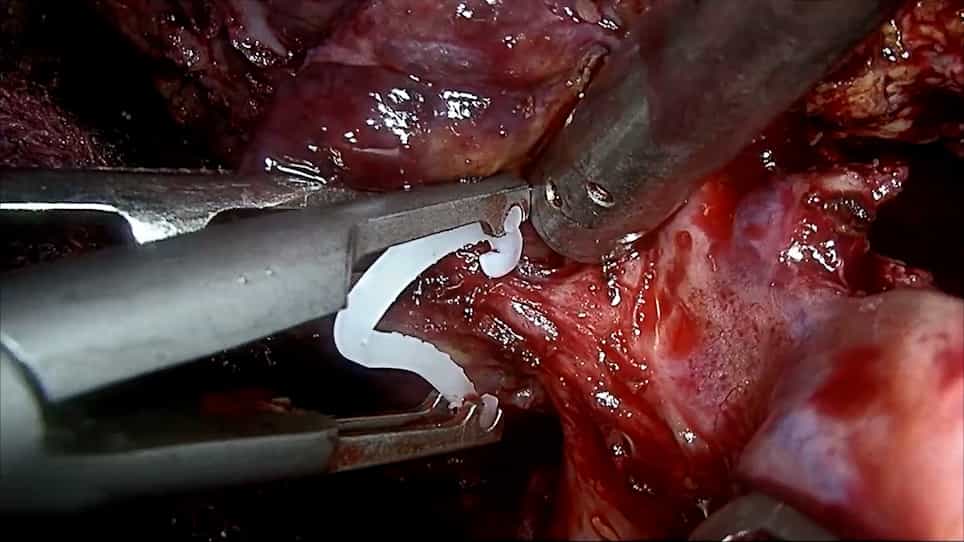
Modified Laparoscopic Anatomic Hepatectomy: Two-Surgeon Technique Combined with the Simple Extracorporeal Pringle Maneuver
Published on: June 16, 2023
Competing Hemodynamic Goals During Hepatectomy in Patients with Fontan Circulation: A Systematic Review of Case
Takamune Minote1, Hiroki Yonezawa2, Michiko Kinoshita1
1Department of Anesthesiology, Tokushima University Hospital, Tokushima, Japan.

Objectives:
To synthesize available evidence on perioperative management and clinical outcomes of hepatectomy in patients with Fontan circulation, focusing on hemodynamic strategies and surgical safety.
Design:
A systematic review of case reports and case series.
Settings:
Published studies were identified through databases (PubMed, Scopus, Cochrane Library, Google Scholar, ICHUSHI, and CiNii Research).
Participants:
Thirty-one patients from 28 studies underwent hepatectomy after the Fontan procedure.
Interventions:
Open or laparoscopic hepatectomy, primarily for hepatocellular carcinoma in the setting of Fontan-associated liver disease.
Measurements And Main Results:
All patients had stable Fontan physiology, and no perioperative mortality was reported. Preoperative baseline central venous pressure (CVP) ranged from 10 to 15 mmHg. Intraoperative management consistently favored a baseline-CVP strategy over conventional low-CVP targets. Laparoscopic approaches uniformly used low-pressure pneumoperitoneum below baseline-CVP levels. The Pringle maneuver was well tolerated; however, inferior vena cava clamping was associated with significant hypotension. The median blood loss was 1,106 mL (range 10-4,130 mL). Congestion-related complications, including ascites, pleural effusion, heart failure, and unspecified fluid retention, were most commonly reported postoperatively.
Conclusion:
Hepatectomy appears feasible in carefully selected patients with stable Fontan circulation. Practical perioperative considerations summarized from reported patterns include maintaining CVP near baseline, minimizing increases in pulmonary vascular resistance, and keeping pneumoperitoneum pressure below baseline CVP during laparoscopic surgery. However, hepatectomy-specific risk stratification has yet to be established, and optimal perioperative management of patients with impaired Fontan physiology remains uncertain. A critical knowledge gap remains regarding hemostatic approaches that optimize bleeding control while preserving the Fontan circulation.