Related Experiment Video
Updated: Oct 19, 2026
A Teleoperated Robotic System-Assisted Percutaneous Transiliac-Transsacral Screw Fixation Technique
Published on: January 6, 2023
Sagittal Alignment-Dependent Mechanical Interference during Robotic-Assisted S2 Alar-Iliac Screw Insertion
Hiroaki Manabe1, Yutaka Kinoshita1, Takayuki Kitahara1
1Department of Orthopedics, Institute of Biomedical Sciences, Tokushima University Graduate School, Tokushima, Japan.

Introduction:
Although robotic-assisted spinal instrumentation enables highly accurate screw placement, mechanical feasibility constraints remain underrecognized. During sacral instrumentation, a collision between the robotic arm and the patient's body may prevent completion of S2 alar-iliac (S2AI) screw placement as planned. Alignment-related factors associated with failure of this procedure have not been clearly defined. The aim of this study was to identify spinopelvic alignment factors associated with mechanical interference during robotic-assisted S2 alar-iliac (S2AI) screw insertion.
Methods:
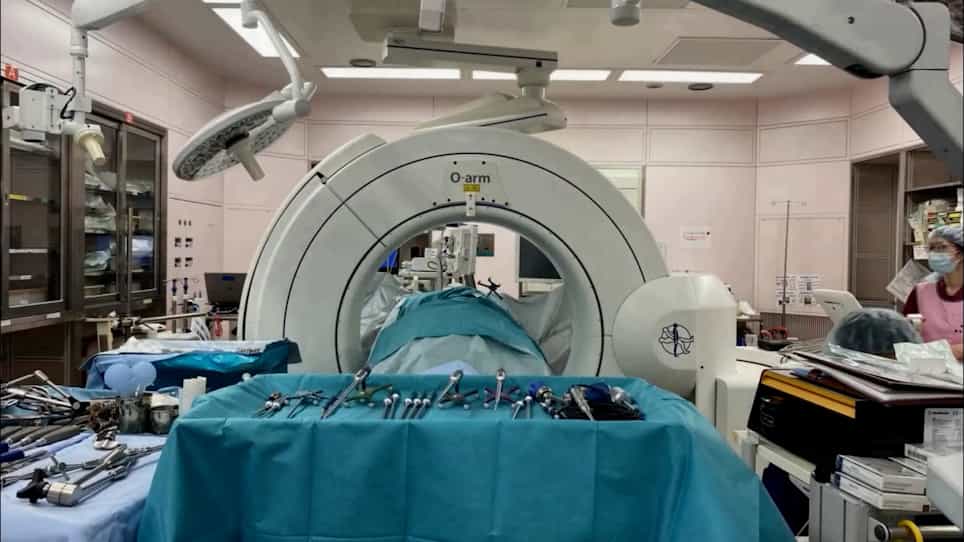
This retrospective observational study included 17 consecutive patients who underwent planned robotic-assisted S2AI screw insertion using the Cirq robotic alignment system (Brainlab) between July 2022 and January 2026. Patients were categorized into a success group (robotic guidance completed as planned) and an interference group (robotic guidance abandoned because of mechanical collision requiring conversion to a conventional technique). Supine spinopelvic parameters, including lumbar lordosis, sacral slope, pelvic tilt, and pelvic incidence, were evaluated preoperatively. Continuous variables were compared between groups using the Mann-Whitney U test.
Results:
Robotic guidance was successfully completed in 13 patients (76%) and discontinued because of mechanical interference in 4 (24%). Supine lumbar lordosis was significantly greater in the interference group (median 58.5° vs. 27.6°, p=0.0008). All cases in the interference group demonstrated lumbar lordosis >50°, whereas none in the successful group exceeded this value (p<0.001). Pelvic tilt demonstrated complete separation between groups, with negative values in all interference cases and positive values in all successful cases (p=0.0008). Sacral slope was significantly higher in the interference group (p=0.0055), whereas pelvic incidence and skin-to-bone distance were not associated with interference.
Conclusions:
Mechanical interference during robotic-assisted S2AI screw insertion was associated with a sagittal alignment profile characterized by increased lumbar lordosis and anterior pelvic orientation. Recognition of alignment-dependent spatial constraints may improve preoperative assessment and help predict technical difficulty.