Related Experiment Video
Updated: Oct 19, 2026
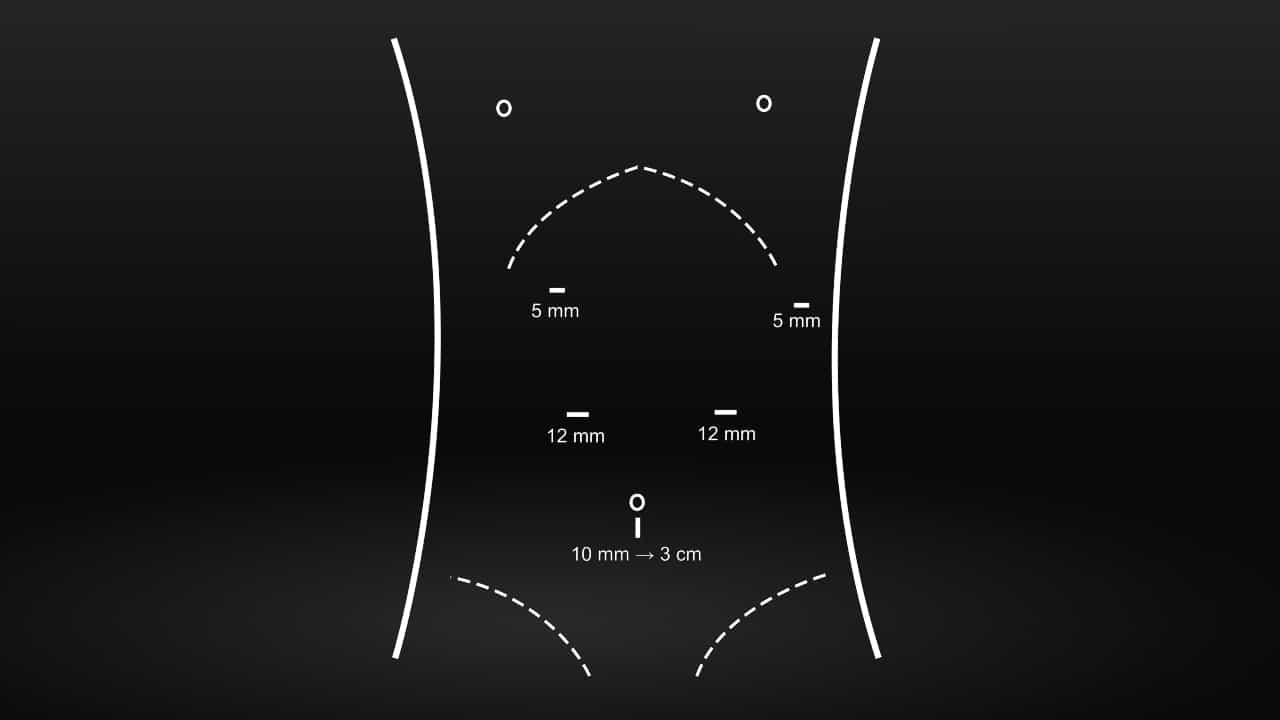
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Coil Embolization and Open Splenectomy for a Massive Splenic Vein Aneurysm: A Case Report
Kaitlyn Vu1, Logan Brown1, Blake Durrence1
1Mercer University School of Medicine Savannah Georgia USA mercer.edu.

Background:
Splenic vein aneurysms (SVAs) are a rare vascular anomaly of the portal system that are often asymptomatic and found incidentally on imaging. Intervention is reserved for aneurysms that are enlarging, thrombosed, symptomatic, or ruptured to avoid catastrophic complications. This can range from endovascular to open, complex procedures. Here, we present the case of a massive, symptomatic, partially thrombosed SVA that required a hybrid approach involving both minimally invasive and open surgery.
Case Presentation:
A 56-year-old woman presented to the emergency department for an infected right foot wound and was admitted for intravenous antibiotics and surgical debridement. While hospitalized, she had a worsening transaminitis with associated abdominal pain, prompting investigation with a computed tomography (CT) scan, which identified a massively dilated, partially thrombosed SVA measuring 18 cm. Given the enormous size of the aneurysm and substantial risk of impending rupture, urgent surgical intervention was planned. Preoperative coil embolization of the splenic artery was performed first to reduce the arterial inflow to the SVA and to minimize the risk of intraoperative hemorrhage during open resection. Three days after embolization, the patient underwent open splenectomy with aneurysmectomy for definitive management. The patient's postoperative course was complicated by a bleeding gastric ulcer that was successfully cauterized, and she was discharged home on postoperative Day 10 after receiving the recommended postsplenectomy vaccines.
Conclusion:
No standard treatment algorithm exists for SVAs, as management is individualized, and treatment evidence is limited to case reports and series. This patient had one of the largest SVAs ever recorded, and management was based on the acuity of symptoms, size, and rupture risk of the aneurysm sac. This case also demonstrated the success of a novel management approach to massive SVAs, using preoperative embolization of the splenic artery followed by open resection without portal reconstruction.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:24
Esophageal Varices-I: Introduction