Related Experiment Video
Updated: Oct 21, 2026
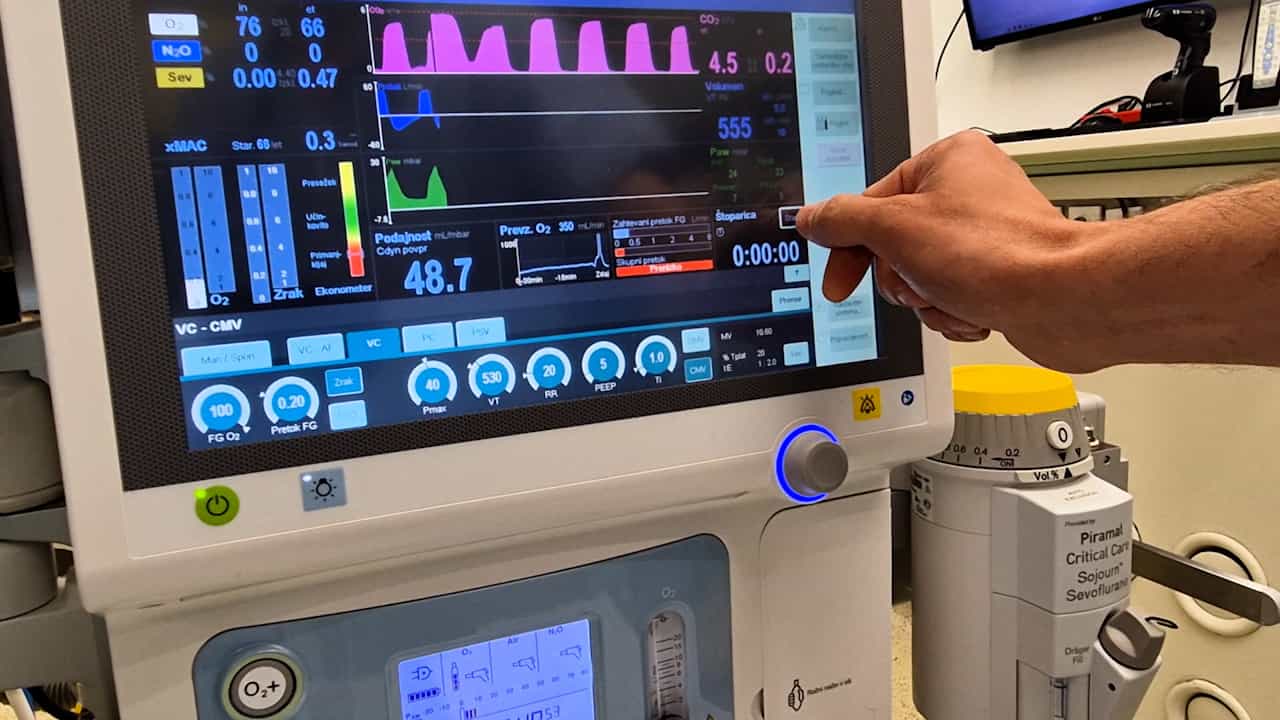
Hypercapnic Hyperventilation to Accelerate Emergence from Inhaled Volatile Anesthetics: A Practical Method Using Standard Hospital Equipment
Published on: June 26, 2026
Obesity Hypoventilation Syndrome: Unloading the Respiratory System with Expiratory Pressure
William H Noah1, Ludovico Messineo2, David P White2
1Sleep Centers of Middle Tennessee, Murfreesboro, TN, USA.

Abstract:
Obesity hypoventilation syndrome (OHS) is traditionally interpreted through the lens of coexistent obstructive sleep apnea (OSA), yet the mechanisms by which continuous positive airway pressure (CPAP) improves daytime hypercapnia without providing ventilatory support remain incompletely explained. This Perspective proposes that abdominal obesity-induced depletion of expiratory reserve volume (ERV) and functional residual capacity (FRC), with consequent reduction in end-expiratory lung volume (EELV), may represent upstream mechanical abnormalities linking OSA, increased work of breathing, sleep hypoventilation, and daytime hypercapnia. Reduced EELV worsens pharyngeal collapsibility by decreasing caudal traction, while simultaneously shifting tidal volume toward a mechanically inefficient portion of the respiratory system curve, characterized by impaired compliance, and increased elastic, resistive respiratory work and possibly threshold loading. Within this framework, OHS emerges when respiratory burden (the mechanical load on the pulmonary apparatus due to excess weight) exceeds ventilatory reserve (an ensemble of respiratory drive and its modifiers such as sleep-state control, leptin signaling, and genetic factors). CPAP and expiratory PAP may provide, in addition to upper-airway splinting, a mechanical unloading by raising EELV, improving respiratory mechanics, and reducing the pressure cost of ventilation. In this context, weight loss represents the ultimate structural unloading therapy, whereas pressure support may be required when unloading alone is insufficient to restore adequate ventilation. Future studies should measure ERV, FRC/EELV, respiratory effort, and mechanics to better phenotype OHS, and understand whether optimizing expiratory pressure before adding ventilatory support actually improves ventilation.
Related Concept Videos
 01:25
Hyperpnea and Hyperventilation
 01:17
Pulmonary Cycle: Exhalation
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:29
Mechanical Ventilation I: Indication and Settings