Related Experiment Video
Updated: Oct 24, 2026
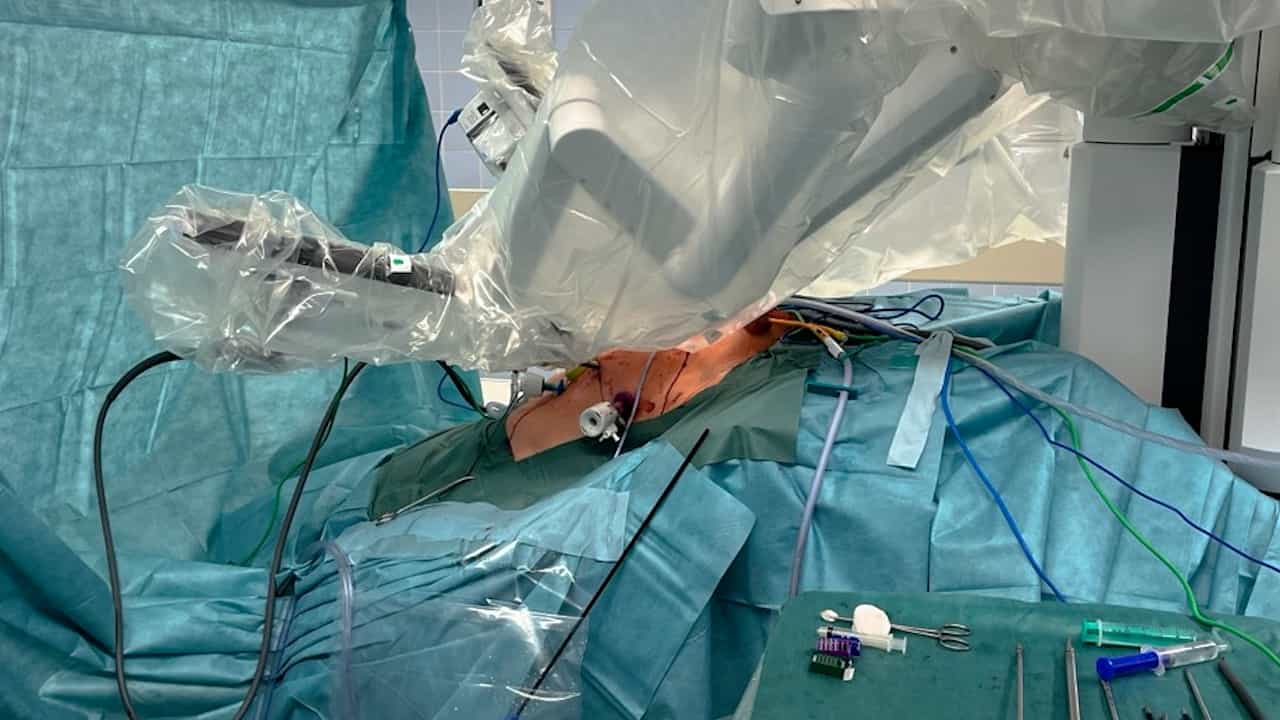
Robot-Assisted Radical Prostatectomy in a Heart Transplant Patient
Published on: July 17, 2026
Robot-Assisted Radical Prostatectomy in a Post-Enucleation Gland
Paulo Roberto Salustiano de Carvalho1, Rafael Gomes Viterbo1, Fabrício Borges Carrerette1
1Serviço de Urologia, Hospital Universitário Pedro Ernesto - HUPE/ UERJ, Rio de Janeiro, RJ, Brasil.

Purpose:
Holmium laser enucleation of the prostate (HoLEP) is an established treatment for benign prostatic obstruction, and some patients subsequently prove to have prostate cancer (1-3). Enucleation leaves fibrosis that displaces the anatomical landmarks relevant to radical prostatectomy (4, 5). We present a robot-assisted radical prostatectomy (RARP) performed after HoLEP.
Materials And Methods:
A 64-year-old man underwent HoLEP; biopsy subsequently showed adenocarcinoma of the right lobe, ISUP grade 3. PSA was 0.51 ng/mL; MRI demonstrated a 0.4 cm PI-RADS 4 lesion at the right mid-base. RARP was performed 29 months later on a da Vinci Xi system. Without the adenoma, the capsule is flaccid and offers no counter-resistance; without haptic feedback, the planes of the bladder neck (6) and neurovascular bundle (7) become indistinct. A wide bladder neck may admit the balloon into the fossa; overinflating it to 40 mL or tracing extravesical landmarks restores the anatomical reference. Retzius-sparing and transvesical approaches are recognized alternatives (8, 9). The video demonstrates a thickened Denonvilliers fascia and the use of the 30-degree lens rotated 180 degrees to open the posterior plane.
Results:
Six ports were used (four robotic, two assistant); console time was 90 minutes with an estimated blood loss of 75 mL. Nerve-sparing was bilateral, and bladder neck reconstruction was not required. The patient was discharged on postoperative day 1; the catheter was removed on day 5. Pathology revealed adenocarcinoma of both lobes, Gleason 7 (4+3), pT2c, with negative surgical margins. At six weeks, the patient was continent without pads and had an undetectable PSA.
Conclusions:
RARP after HoLEP is feasible. To our knowledge, this is the first video article dedicated to this operation, demonstrating each post-enucleation anatomical obstacle and a practical surgical response. The bladder neck and posterior plane warrant particular caution.
