Related Experiment Video
Updated: Oct 25, 2026
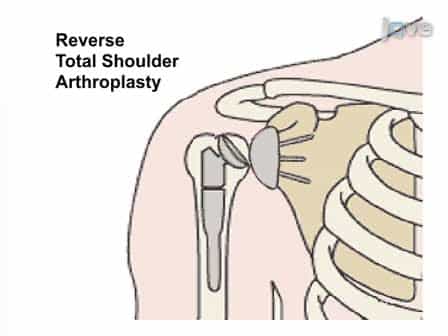
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Late efficiency gains in robotic-assisted reverse shoulder arthroplasty: an updated learning curve analysis of the
Dilpreet Singh1, Ivan Mansour1, Kali Barnes1
1UC Davis Department of Orthopaedic Surgery, UC Davis Health, Sacramento, USA.

Abstract:
Learning curves for robotic-assisted reverse shoulder arthroplasty (RSA) are typically described over a surgeon's first 20 to 30 cases. Whether operative efficiency continues to improve beyond that point, and whether mean operative time is the appropriate measure of it, is unknown. We evaluated 100 consecutive primary robotic-assisted RSA procedures performed by a single fellowship-trained surgeon using the Mako system (Stryker, Kalamazoo, MI) at an academic ambulatory surgery center. The first 30 cases comprise our previously reported cohort. Operative time, defined as incision to the start of closure, was modeled by segmented linear regression with a breakpoint at case 30. Variability was assessed by standard deviation and Levene's test, and the distribution of improvement by percentile comparison and by quantile regression at the 10th, 50th and 90th percentiles. Baseline characteristics were compared across case groups, and the influence of patient factors on operative time was assessed by multivariable regression. Mean operative time fell from 88.6 min (cases 1 to 30) to 75.4 min (cases 31 to 70) to 64.3 min (cases 71 to 100). Segmented regression demonstrated a steep initial decline of 1.85 min per case (P = 0.0001) followed by a shallower but significant decline of 0.26 min per case (P = 0.001), with a significant difference in slope between phases (P < 0.0001). Variability fell proportionally further than the mean, with standard deviation decreasing by 56.6% against a 27.5% decrease in mean operative time (P = 0.008). Improvement was greatest at the upper end of the distribution: the 90th percentile declined by 0.52 min per case compared with 0.30 min per case at the 10th, and percentile improvement increased from 17% at the 5th percentile to 35% at the 95th. The total range of operative time contracted from 115 to 42 min, and the proportion of cases exceeding 90 min fell from 40% to none. Baseline characteristics did not differ across case groups, and the case-number effect persisted after adjustment for age, sex, body mass index and glenoid deformity. Operative efficiency in robotic-assisted RSA continues to improve well beyond the initial 30-case learning period, but the way that improvement is expressed shifts from shortening the typical case to eliminating the prolonged outliers. Because operating room scheduling is driven by the tail of the distribution rather than its mean, case-to-case predictability of operative time may be a more informative marker of a mature robotic workflow than mean operative time alone.
