Related Experiment Video
Updated: Oct 26, 2026
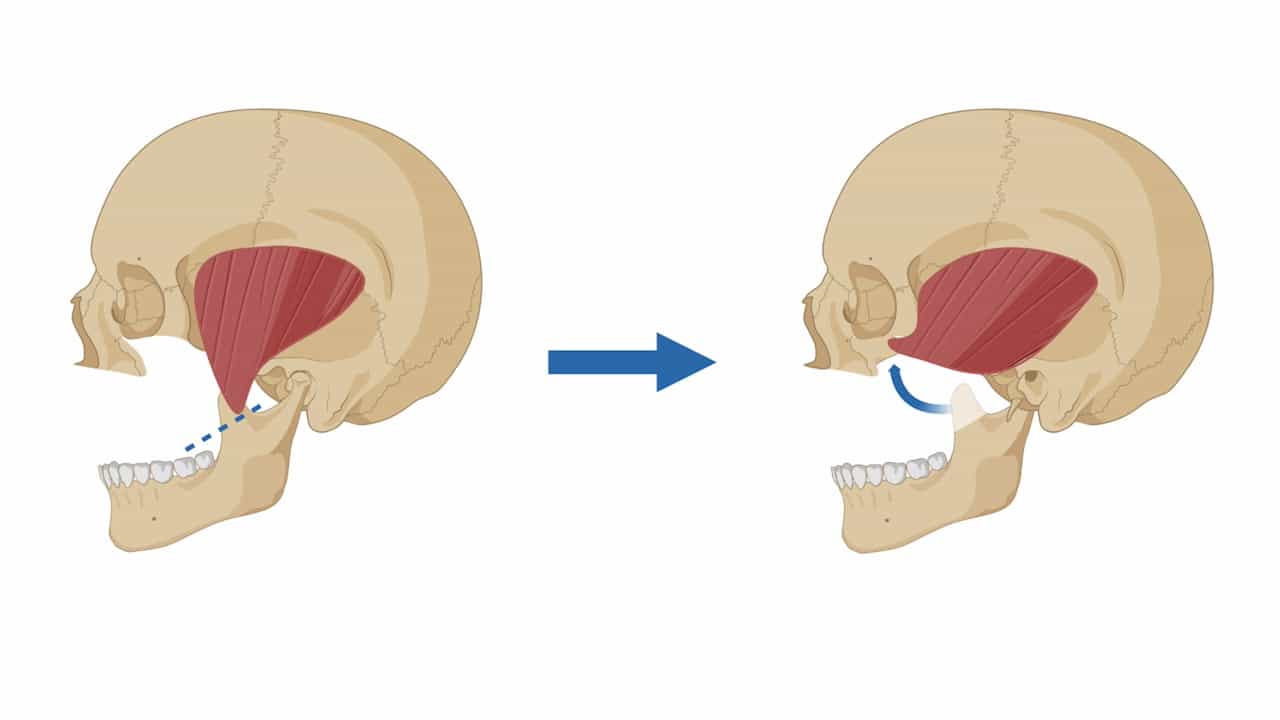
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Free flap selection strategies and advances in facial soft tissue defect reconstruction
Junzhi Zhao1, Xing He1, Kangcha Chen1
1Department of Orthopedics (Area 3), Xiaolan Clinical Institute of Shantou University Medical College, Zhongshan, China.

Background:
Reconstruction of facial soft tissue defects remains a demanding task in plastic, reconstructive, and head and neck surgery because the face combines aesthetic units with essential functions such as oral competence, speech, swallowing, breathing, eyelid protection, and facial expression. The severity, depth, and composition of the defect are the primary determinants of flap selection, especially when defects extend beyond skin and subcutaneous tissue to expose the oral cavity, pharynx, nasal cavity, skull base, or critical structures.
Methods:
This narrative review summarizes evidence and technical progress regarding free flap selection for facial soft tissue reconstruction. Literature was identified through PubMed, Web of Science, and Google Scholar using combinations of the terms "facial soft tissue defect," "free flap," "perforator flap," and "virtual surgical planning." Priority was given to systematic reviews, meta-analyses, clinical series, and studies published between 2019 and 2026, while classic microsurgical reports were retained when foundational.
Results:
Free flap choice should be guided by an integrative three-dimensional matrix: defect characteristics×patient profile×institutional resources. The anterolateral thigh flap remains a workhorse for moderate to large defects because of its thickness, long pedicle, availability of fascia lata, and nerve harvest. The radial forearm free flap remains valuable for thin and pliable resurfacing of the lips, eyelids, nasal lining, and oral lining. The deep inferior epigastric perforator flap is useful for large-volume contour restoration. Additional soft tissue options-including the lateral arm, parascapular, and medial sural artery perforator flaps-should be considered when color match, donor-site morbidity, or body habitus makes traditional workhorse flaps suboptimal.
Conclusions:
Facial soft tissue reconstruction requires not only flap survival but also restoration of contour, sensation, oral competence, facial animation, donor-site acceptability, and patient-reported quality of life. Mature technologies such as CTA, selective ultrasound, virtual surgical planning, intraoperative indocyanine green angiography, and structured postoperative monitoring should be distinguished from evolving tools such as augmented reality, artificial intelligence decision support, robotic-assisted anastomosis, artificial vascular conduits, and allogeneic or xenogeneic transplantation. Future research should focus on multicenter registries, standardized outcome measures, cost-effectiveness analyses, and externally validated decision-support models.