Related Experiment Video
Updated: Oct 26, 2026

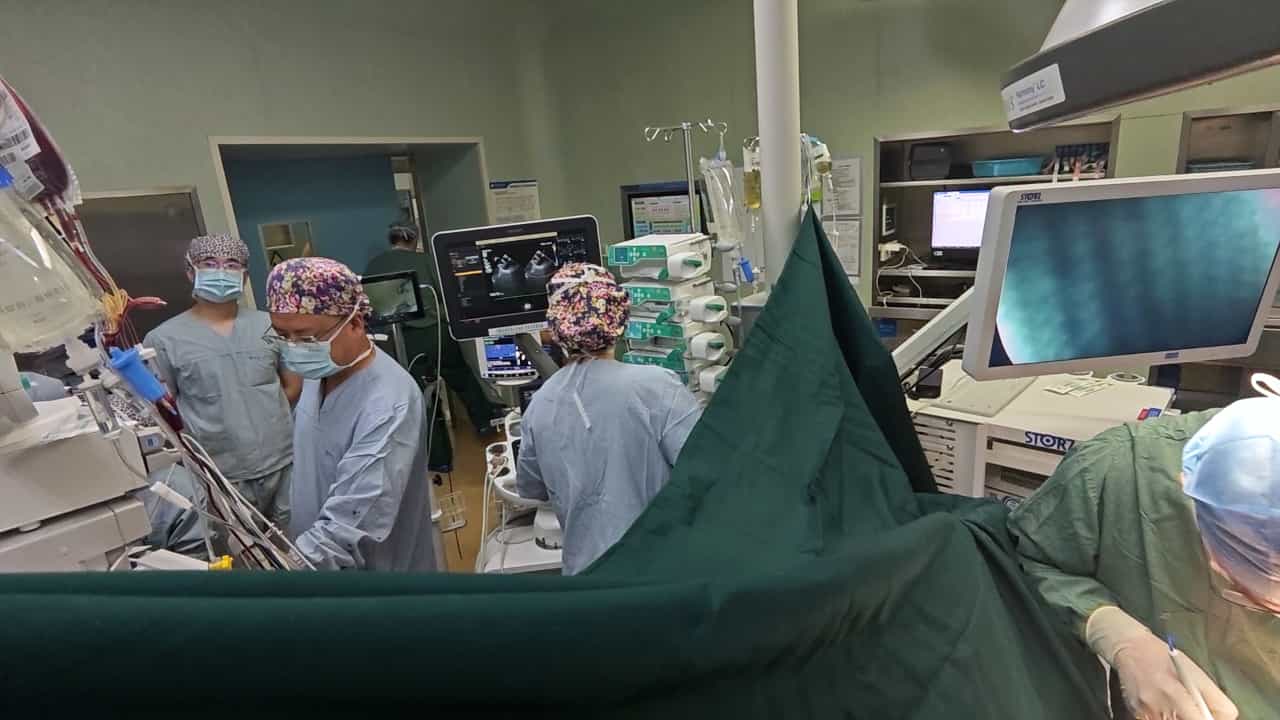
Cardiac Loading using Passive Left Atrial Pressurization and Passive Afterload for Graft Assessment
Published on: August 2, 2024
Prognostic value of Fibrosis-4 Index and preoperative dynamic changes in heart transplantation
Junlin Lai1, Yazheng Shan1, Wai Yen Yim1
1Department of Cardiovascular Surgery, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, No. 1277 Jiefang Avenue, Wuhan, Hubei 430022, China.

Introduction:
The Fibrosis-4 (FIB-4) Index has shown prognostic value in cardiovascular diseases, but its role in heart transplantation (HTx) and the impact of dynamic preoperative changes remain unclear. This study evaluated the prognostic value of preoperative FIB-4 for mortality after HTx and investigated whether dynamic changes in FIB-4 before transplantation are associated with post-transplant survival.
Methods:
This single-centre retrospective cohort study included 791 adult patients who underwent orthotopic HTx between January 2015 and December 2024, with follow-up through June 2025. Patients were stratified by preoperative FIB-4 into low (<1.30), intermediate (1.30-2.67), and high (>2.67) risk groups. The primary outcome was all-cause mortality. Analyses employed Cox models, restricted cubic splines, and five machine learning survival models, including Random Survival Forest (RSF).
Results:
During a median follow-up of 28.8 months, 218 patients (27.6%) died. Preoperative FIB-4 showed a non-linear association with mortality (inflection point: 2.03) and was an independent predictor of death [hazard ratio (HR) per unit increase, 1.04; 95% CI, 1.02-1.07; P < .001]. In the RSF model, FIB-4 was the most important prognostic variable (Variable Importance = 0.068), outperforming traditional donor and surgical factors. Sensitivity analyses confirmed that FIB-4's prognostic value was independent of age (interaction P = .745) and superior to its individual components (aspartate aminotransferase, alanine aminotransferase, and platelet count). Correlation analyses showed no significant association between FIB-4 and invasive haemodynamic parameters, tricuspid regurgitation severity, or MELD/MELD-XI scores, supporting its distinction from haemodynamic congestion. Among high-risk patients (n = 153), preoperative improvement in FIB-4 category was associated with significantly lower mortality (adjusted HR, 0.49; 95% CI, 0.29-0.82; P = .007). Preoperative use of glutathione was independently associated with FIB-4 improvement [odds ratios (OR), 1.50; 95% CI, 1.01-2.22; P = .04].
Conclusion:
Preoperative FIB-4 is a robust and independent predictor of post-transplant mortality, with greater predictive importance than traditional surgical risk factors. Dynamic improvement in FIB-4 before transplantation is associated with better survival. Integrating FIB-4 into routine preoperative assessment may refine risk stratification and guide pre-transplant management.