Related Experiment Video
Updated: Oct 26, 2026
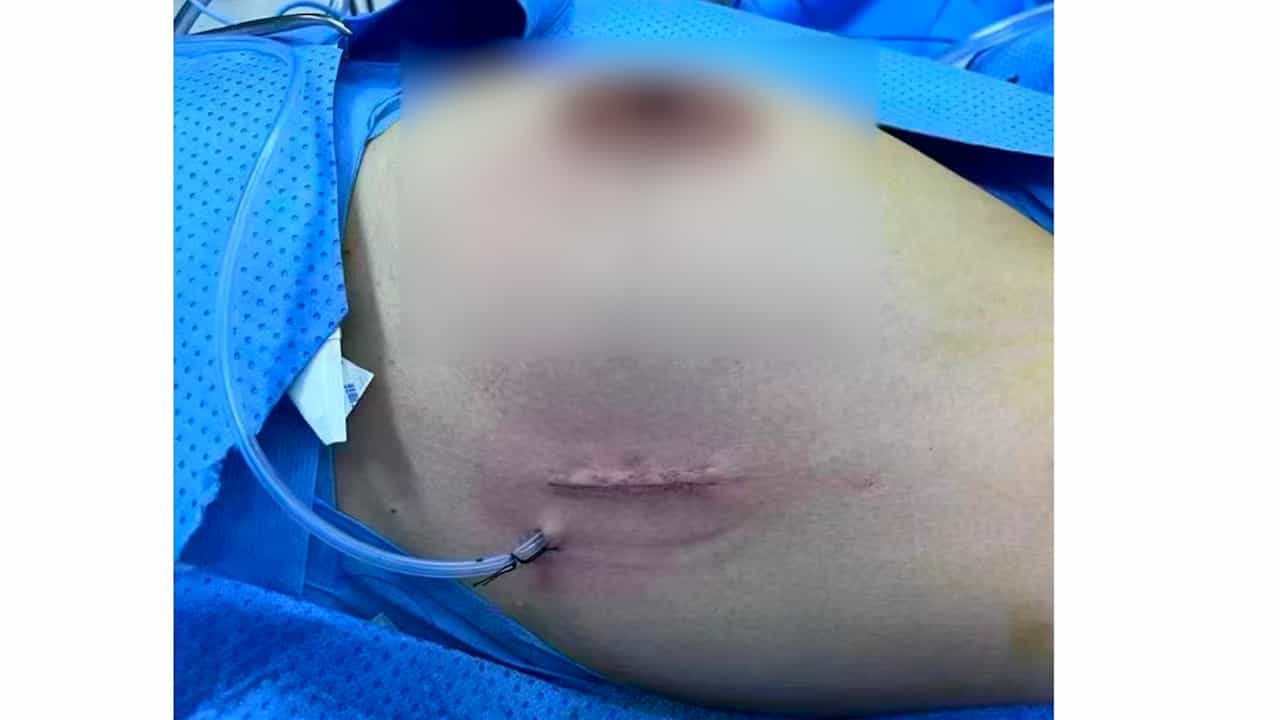
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Imaging Assessment of Residual Disease in Clipped Target Lymph Nodes after Neoadjuvant Chemotherapy for Breast
Michiko Yamazaki1, Rikiya Nakamura1, Shouko Hayama1
1Division of Breast Surgery, Chiba Cancer Center, Chiba, Japan.

Introduction:
Accurate assessment of residual axillary disease after neoadjuvant chemotherapy (NAC) is critical for selecting candidates for tailored axillary surgery. However, the diagnostic performance of post-NAC imaging for residual disease in clipped metastatic lymph nodes remains unclear.
Methods:
We retrospectively analyzed 112 patients with biopsy-proven axillary lymph node metastasis who underwent clip placement in a target lymph node before NAC. After NAC, the clipped node was assessed using ultrasonography and computed tomography, and imaging findings were directly compared with the pathological status of the resected clipped node. Diagnostic performance was evaluated overall and according to breast cancer subtype. In addition, logistic regression-based prediction models were developed and internally validated using 5-fold cross-validation.
Results:
Among the 112 patients, 82 were classified as clinically node-negative and 30 as clinically node-positive after NAC. Post-NAC imaging showed a sensitivity of 38.8%, specificity of 82.5%, positive predictive value of 63.3%, negative predictive value of 63.4%, and accuracy of 63.4% for residual disease in the clipped node. Notably, imaging did not detect residual disease in 30 of 49 pathologically positive clipped nodes. Diagnostic performance varied according to subtype, with higher negative predictive value in HER2-positive tumors and lower negative predictive value in HR-positive/HER2-negative disease. Prediction models showed moderate discrimination, with 5-fold cross-validated AUCs of 0.79-0.81. The 6-variable model achieved the highest NPV of 0.88, although additional variables yielded only modest improvements over the baseline model.
Conclusion:
Post-NAC imaging of the clipped target lymph node frequently differed from the pathological findings of the same resected clipped metastatic lymph node. Residual disease may persist despite disappearance of nodal morphology, while pathological complete response may occur despite suspicious imaging findings. These limitations underscore the importance of pathological evaluation of the clipped node for safe axillary de-escalation. These findings have direct implications for surgical decision-making in axillary management after NAC.