Related Experiment Video
Updated: Oct 26, 2026
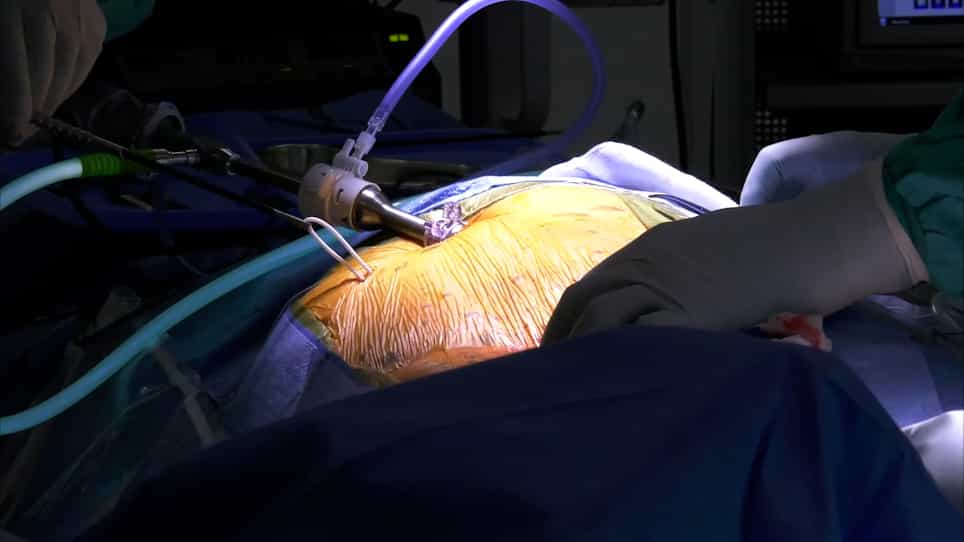
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Mortality after ventriculoperitoneal shunting for idiopathic normal pressure hydrocephalus and its clinical
Abdelrahman M Hamouda1, Rahul Kumar1, Zach Pennington1
1Department of Neurosurgery, Mayo Clinic, Rochester, MN, 55905, USA.

Introduction:
Patients with idiopathic normal pressure hydrocephalus (iNPH) often have comorbid conditions that may adversely impact survival, but long-term mortality risk in this population remains incompletely characterized.
Methods:
Patients who underwent VPS placement for iNPH at a single tertiary care center between 2017 and 2025 were identified. Comorbidities, demographic characteristics, and perioperative complications were evaluated using univariable Cox regression analyses to identify factors associated with mortality at the last follow-up. Comorbidities were quantified with the modified Frailty Index-5 (mFI-5) and Charlson Comorbidity Index (CCI).
Results:
452 patients were included (median age, 75.3 years; 61.9% male). Forty-four (9.7%) died during follow-up (median 39.1 months), with a median postoperative survival of 19.8 months and a median age at death of 78.4 years. Median mFI-5 was 1.0 and median CCI was 2.0. Baseline comorbidities in total cohort included prior myocardial infarction (MI) in 5.8% of patients, congestive heart failure (CHF) in 6.9%, cerebrovascular accident (CVA) in 14.4%, dementia in 27.1%, and functional dependence in 54.9%. At presentation, 96.0% had gait impairment, 84.5% had cognitive deficits, and 81.6% had urinary incontinence. Regarding perioperative outcomes, 57 patients (12.6%) were hospitalized more than one day and 30 (6.7%) required non-home discharge. Postoperative subdural fluid collections occurred in 13.6% of patients, while 6.9% underwent shunt revision. On multivariable Cox regression analysis, higher CCI (HR 1.27, p = 0.005) and hospitalization >1 day (HR 3.20, p = 0.001) were independently associated with increased mortality.
Conclusion:
Nontrivial rates of mortality are seen following VPS in iNPH - approximately estimated at 10% over four years in the present study. Increased mortality appears correlated with more extensive comorbidities and poorer functional status, highlighting the importance of careful patient selection in this frail population. Notably, this mortality rate closely approximates the mortality expected on an actuarial basis for an age- and sex-matched general population and is substantially lower than mortality previously reported for patients with mild cognitive impairment, suggesting that VPS may mitigate the excess mortality otherwise anticipated in this population.
Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology