Preoperative MRI-based clinicoradiological scoring system for perineural invasion prediction and risk stratification
Shi-Ao Hu1, Yi-Hao Yan1, Jun-Jie Shu1
1Department of Magnetic Resonance Imaging, The First Affiliated Hospital of Henan University of Chinese Medicine, Zhengzhou, Henan, China; The First Clinical Medical College, Henan University of Chinese Medicine, Zhengzhou, Henan, China.

Background:
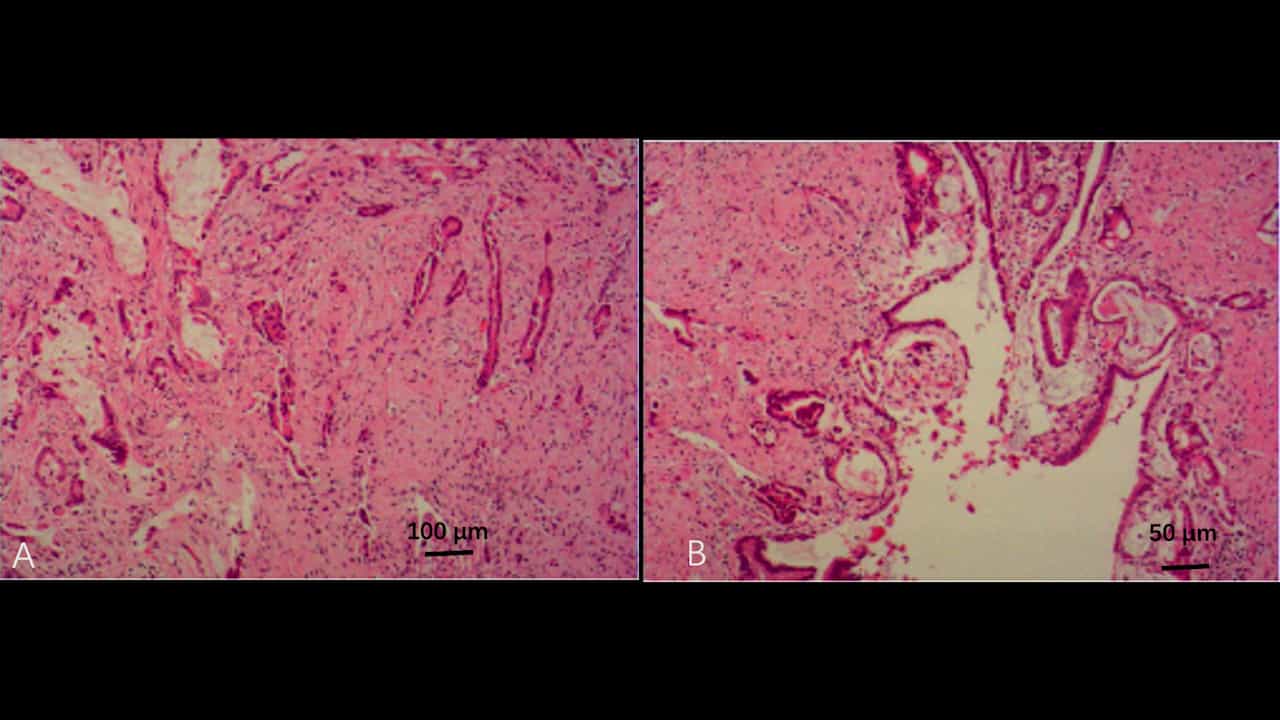
Perineural invasion (PNI) is a strong predictor of early recurrence and poor survival in intrahepatic cholangiocarcinoma (ICC). However, PNI can only be confirmed by postoperative histopathology, and preoperative risk stratification tools remain lacking.
Materials And Methods:
A total of 190 intrahepatic cholangiocarcinoma patients from three centers were retrospectively allocated into training, internal, and external validation cohorts. Continuous variables were dichotomized via the Youden index. Independent predictors from multivariate logistic regression were assigned integer scores, calculated by dividing each β coefficient by the minimum β, to construct a simplified scoring system. Performance was validated using AUC, calibration, and decision curve analysis. Using the optimal Youden cutoff , patients were risk-stratified to evaluate recurrence-free survival via Kaplan-Meier and Cox analyses.
Results:
Elevated platelet-to-lymphocyte ratio (>144.43), perihilar location, and disrupted arterial enhanced edge integrity were identified as independent PNI predictors. Each was assigned 1 point to construct a 3-point scoring system. The system demonstrated favorable discrimination with AUCs of 0.870, 0.859, and 0.807 in the training, internal, and external validation cohorts, respectively. Calibration and DCA confirmed excellent agreement and clinical utility. High-risk patients (score ≥ 2) exhibited significantly shorter RFS across the training (hazard ratio [HR] = 4.150, 95 % CI: 2.343-7.350; P < 0.001), internal validation (HR = 3.801, 95 % CI: 1.589-9.093; P = 0.001), and external validation (HR = 3.311, 95 % CI: 1.397-7.848; P = 0.004) cohorts.
Conclusions:
This MRI-based scoring system offers a noninvasive tool to preoperatively identify high-risk PNI patients, potentially guiding extended resection, neoadjuvant therapy, and intensified surveillance.