Related Experiment Video
Updated: Oct 27, 2026
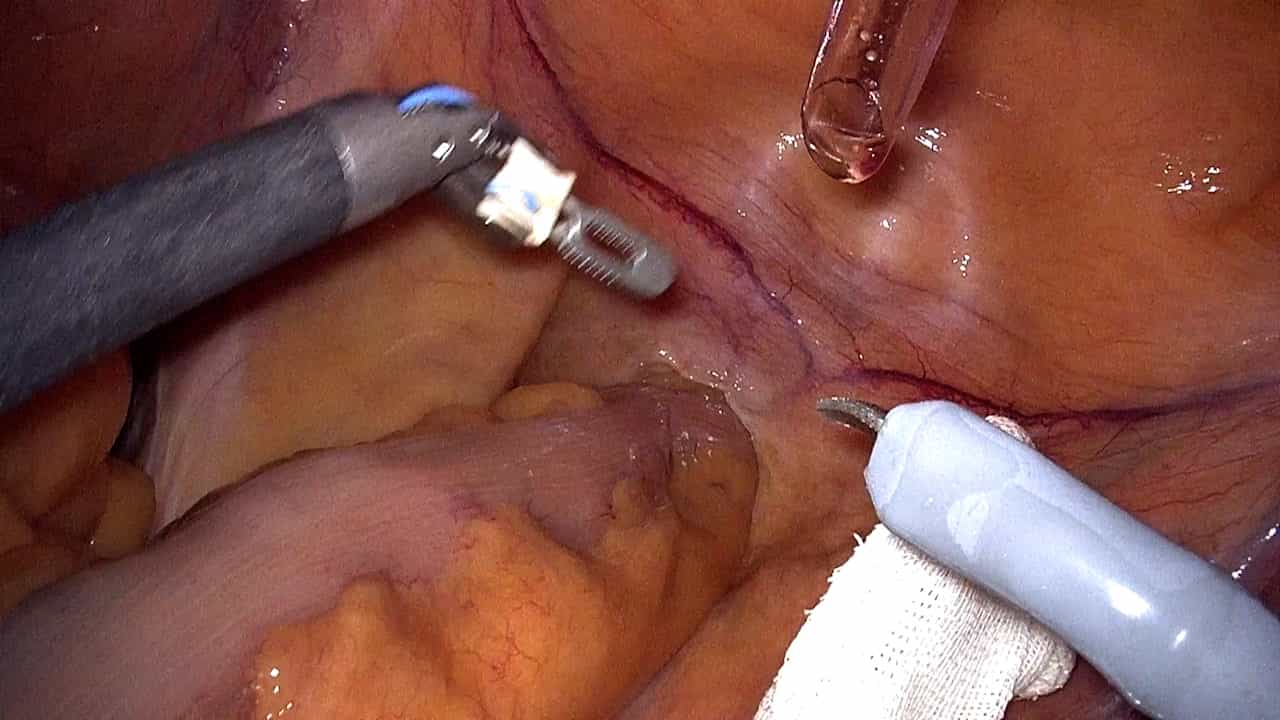
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Robotic rectal cancer surgery: oncological and functional outcomes, technical pitfalls, and unresolved controversies
Xiangyu Zhu1, Xiaoquan Yang2, Tianzuo Wang3,4
1Department of General Medicine, Cancer Hospital of Dalian University of Technology, Liaoning Cancer Hospital & Institute, Shenyang, China.

Abstract:
Total mesorectal excision (TME) remains the curative operation for rectal cancer. The male pelvis, obesity, and a narrow anal canal make rectal dissection the most demanding step in abdominal surgery, even for experienced surgeons. Robotic systems were introduced to address these constraints by providing a stable three-dimensional view, wristed instruments, and ergonomic control beyond that of conventional laparoscopy. Two decades after the first robotic TME, randomized trials (ROLARR and REAL), transanal TME trials, and more than a dozen meta-analyses permit a more measured assessment. To make that assessment clear and comparable, we organize it around a prespecified core set of outcome parameters rather than every metric reported in the literature: the primary oncological and surgical-quality outcomes are conversion to open surgery, circumferential resection margin (CRM) involvement, completeness of the mesorectal specimen, and long-term locoregional recurrence and disease-free survival; the primary functional outcomes are bowel, urinary, and sexual function, measured with validated instruments at fixed time points. Overall survival, distal margin, lymph node yield, general morbidity and anastomotic leak, operative time, blood loss, length of stay, quality of life, and cost are treated as secondary outcomes. Against this core set, robotic surgery consistently reduces conversion to open surgery. In the most informative recent trial, it also improved circumferential resection margin quality and three-year locoregional control in high-risk middle and low rectal cancers, without affecting overall survival. Functional benefits, including earlier recovery of urinary function and modest improvements in bowel and sexual outcomes, are plausible but supported by low-certainty evidence. Distinct pitfalls remain, ranging from arm collision and docking errors to distal-plane deviation and anastomotic failure, and the approach is slower and more expensive than laparoscopy. This review summarizes the oncological and functional evidence, relates technical errors to the operative sequence, and examines unresolved controversies: which patients benefit most, how robotics compares with transanal dissection, and whether fluorescence imaging, neuromonitoring, and new competing platforms alter the balance.