Related Experiment Video
Updated: Oct 27, 2026
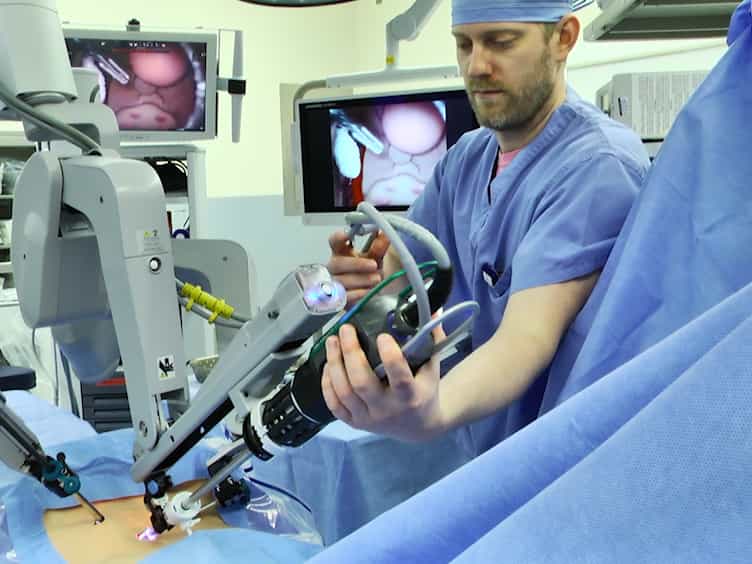
Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Emergency undocking in robotic surgery: an international Delphi consensus study
George Ryan1, Taner Shakir2, Nader Francis3
1Division of Surgical and Interventional Sciences, University College London, London, UK. george.ryan2@nhs.net.

Abstract:
Emergency undocking in robotic surgery is an uncommon but high-stakes event. Published protocols are predominantly single-institution and specialty-specific, and no multidisciplinary cross-specialty consensus exists. This study aimed to establish expert consensus on the definitions and procedural steps of safe emergency undocking. A four-round modified Delphi study was conducted with an international panel of robotic theatre team members. Round 1 used open-text questions to generate themes; Rounds 2 to 4 presented binary statements (Yes / No / Unable to rate), with a pre-specified threshold of 80% agreement and Unable to rate responses excluded from the denominator. Items below threshold, or reaching threshold with substantive comments, were revised and re-presented. Fifty-two experts from 10 countries consented and completed Round 1. The panel comprised lead or experienced console surgeons (53.8%), first assistants (30.8%), surgical care practitioners (9.6%), anaesthetists (3.8%), and one industry representative (1.9%). Response rates were 80.8%, 80.8%, and 76.9% for Rounds 2 to 4 respectively. Thirty-seven statements reached consensus, comprising two definitions, six common pathway items, 18 controlled undocking items, and 11 uncontrolled undocking items. Of the 37 statements, 25 were classified as platform-agnostic and 12 as platform-dependent. Three role-allocation items were deferred to a planned subsequent round. This Delphi process produced 37 consensus statements defining controlled and uncontrolled emergency undocking and the steps for each. The panel was predominantly United Kingdom-based and surgical, and included no scrub or circulating practitioners. The resulting framework requires simulation and clinical validation before implementation.