Related Experiment Video
Updated: Oct 28, 2026
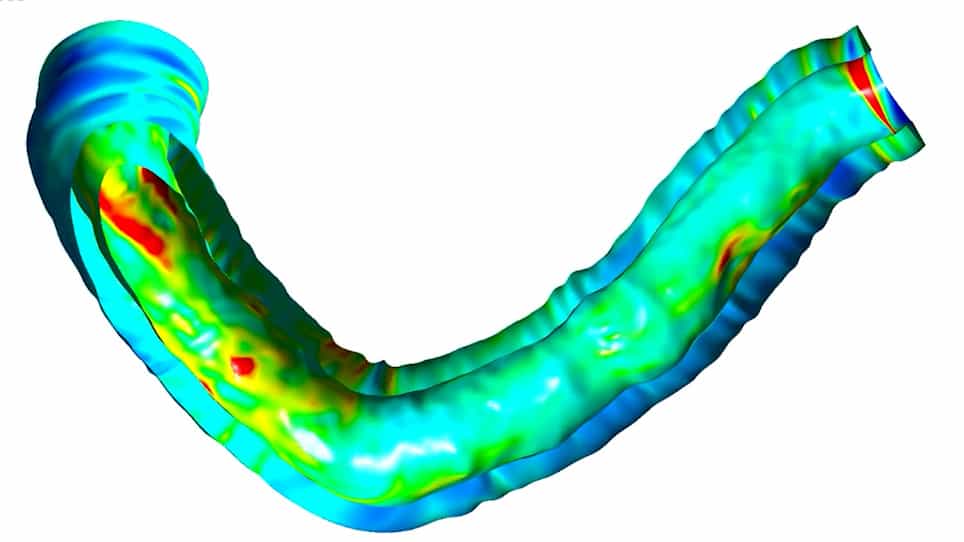
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Residual SYNTAX score and optical coherence tomography-derived thin-cap fibroatheroma in patients with ST-elevation
Meharunnisha Syed1, Uma Devi Karuru1, Sunitha Arumulla1
1Department of Cardiology, Nizam's Institute of Medical Sciences, Hyderabad, India.

Background:
ST-elevation myocardial infarction (STEMI) remains a leading cause of global morbidity and mortality. While percutaneous coronary intervention (PCI) is the definitive reperfusion strategy, residual disease burden and plaque vulnerability both influence clinical recovery. The residual SYNTAX score (rSS) quantifies untreated macroscopic coronary artery disease, whereas optical coherence tomography (OCT) resolves microscopic plaque architecture, notably thin-cap fibroatheroma (TCFA). This pilot study explored the descriptive characteristics and short-term outcomes associated with combining rSS and OCT-derived TCFA in a highly selected STEMI cohort.
Methods:
This retrospective observational pilot study included 30 patients with STEMI who underwent primary PCI and culprit lesion OCT evaluation at a tertiary care center. Patients were stratified into four groups according to the presence of culprit TCFA and the post-PCI rSS threshold ( 4 vs. > 4): group 0 (TCFA absent, rSS > 4), group 1 (TCFA absent, rSS 4), group 2 (TCFA present, rSS > 4), and group 3 (TCFA present, rSS 4). The primary clinical endpoint was major adverse cardiac events (MACE)-a composite of all-cause death, recurrent myocardial infarction, target lesion revascularization, heart failure hospitalisation, and ischemic stroke-assessed over 3 months.
Results:
The cohort (mean age, 54.5 ± 10.1 years; 83.3% male, 40% with diabetes mellitus) had a 53.3% prevalence (16 of 30) of culprit lesion TCFA. Complete or reasonable revascularization (rSS ≤ 4) was achieved in 12 patients (40.0%). The overall cumulative 3-month MACE rate was 30.0% (9 of 30). MACE occurred in 1 of 7 patients (14.3%) in group 0, 1 of 7 (14.3%) in group 1, 4 of 11 (36.4%) in group 2, and 3 of 5 (60.0%) in group 3 (Fisher exact test, P = 0.23; log-rank P = 0.38). Patients with TCFA accounted for 7 of 9 clinical events (77.8%). Given the small subgroup sizes (n < 12), multivariable predictive risk modeling was not performed.
Conclusions:
In this exploratory pilot cohort of STEMI patients undergoing PCI, the presence of OCT-derived TCFA was descriptively associated with higher short-term adverse event rates across both complete and incomplete revascularization strata. Given the small sample size and clear indication bias, these findings are strictly hypothesis-generating and support the need for adequately powered prospective registries to evaluate dual anatomical-biological risk stratification.
More Related Videos
 07:18
Evaluation of Capillary and Other Vessel Contribution to Macular Perfusion Density Measured with Optical Coherence Tomography Angiography
Published on: February 18, 2022
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT