Related Experiment Video
Updated: Oct 28, 2026
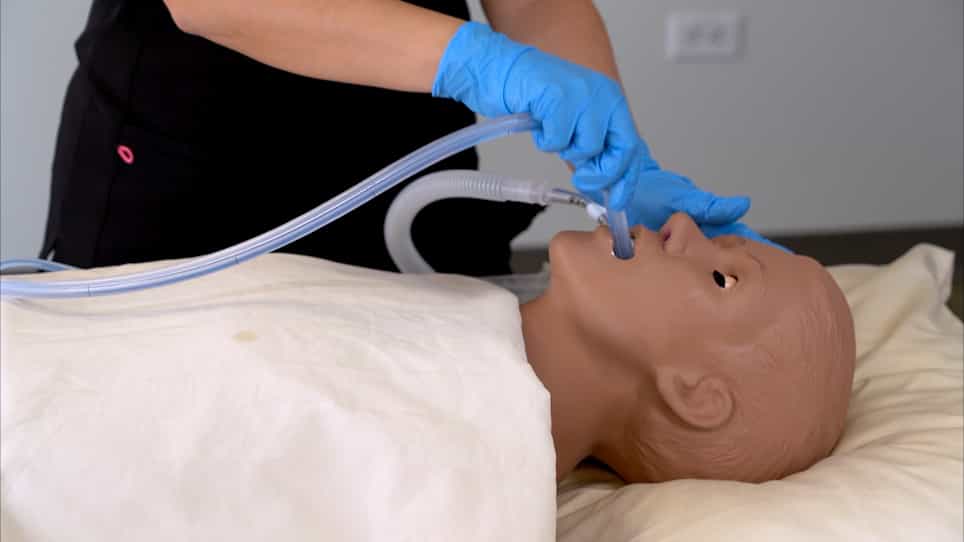
Reduced Procedure Time and Variability with Active Esophageal Cooling During Radiofrequency Ablation for Atrial Fibrillation
Published on: August 25, 2022
Physiological Responses to a Sequential Higher-Frequency Low Tidal Volume Ventilation Protocol During Radiofrequency
Max Briefs1, Maximilian A Jacobi1, Astrid Bergmann1
1Heart and Diabetes Center NRW, Institute of Anesthesiology and Pain Therapy, Ruhr University Bochum, 32545 Bad Oeynhausen, Germany.

Abstract:
The physiological effects of mechanical ventilation are subject to ongoing research. Conventional ventilation may contribute to pulmonary volutrauma or barotrauma and influence cardiovascular physiology through changes in intrathoracic pressure. In the multicenter Ablate-by-LAWT study, patients undergoing atrial fibrillation ablation were ventilated using a higher-frequency, low tidal ventilation (HFLTV) protocol. This post hoc single-center subgroup proof-of-concept study aimed to characterize physiological responses to HFLTV using left atrial pressure (LAP), gas exchange, and hemodynamic parameters during sequential, nonrandomized volume-controlled ventilation (VCV) and HFLTV. The ventilation protocols differed in respiratory rate, tidal volume, PEEP, FiO2, and I:E ratio. Twelve patients were included, and differences between ventilation strategies were assessed using two-sided paired t-tests. Compared with VCV, HFLTV was associated with lower systolic LAP (Mean Difference (MD) -3.33 mmHg, 95% confidence interval (CI) [-5.61; -1.06], p = 0.008), whereas post hoc estimated mean LAP was similar between ventilation periods (MD -0.06 mmHg, 95% CI [-2.19; 2.08], p = 0.955). Heart rate (MD 8.1 bpm, 95% CI [3.8; 12.4], p = 0.002), mean arterial pressure (MD 11.5 mmHg, 95% CI [7.1; 15.9], p < 0.001), and cardiac index (MD 0.64 L/min/m2, 95% CI [0.29; 0.99], p = 0.002) were higher during HFLTV. The partial arterial pressure of oxygen (PaO2) was lower during HFLTV (MD -42.3 mmHg, 95% CI [-83.5; -1.1], p = 0.045, FDR-adjusted p = 0.072), and the partial arterial pressure of carbon dioxide (PaCO2) (MD -1.1 mmHg, 95% CI [-6.0; 3.7], p = 0.623) and the PaO2/FiO2 ratio (MD -49.3 mmHg, 95% CI [-105.2; 6.7], p = 0.079) did not differ significantly. Given the fixed-order design and simultaneous modification of multiple ventilatory parameters, these exploratory findings should be considered hypothesis-generating and cannot be attributed to individual components of the HFLTV protocol.
More Related Videos
 06:25
Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
 05:43
Determination of Continuity Index Values in Atrial Fibrillation Ablation with Proactive Esophageal Cooling
Published on: April 19, 2024