Related Experiment Video
Updated: Oct 29, 2026
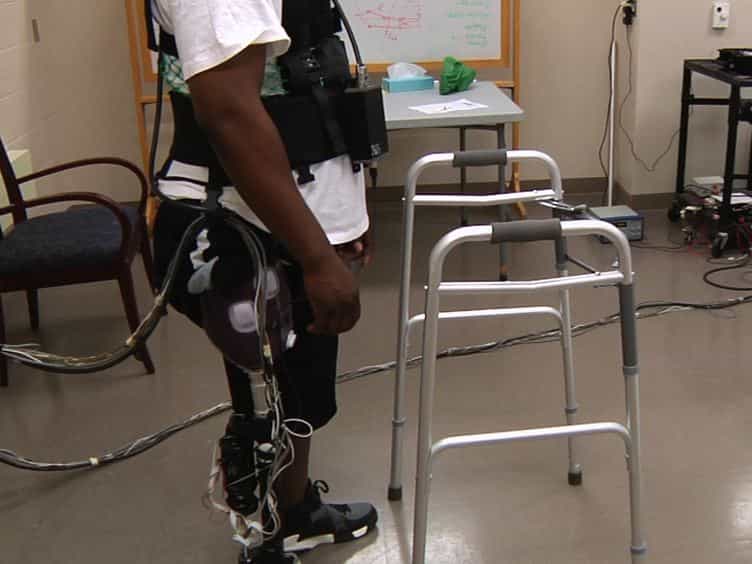
Engineering Platform and Experimental Protocol for Design and Evaluation of a Neurally-controlled Powered Transfemoral Prosthesis
Published on: July 22, 2014
Experiences of MI‑E provision and use from the perspective of people with NMD and physiotherapists: A qualitative
Meredith A Perry1, Bernadette Jones2, Andrew Campbell2
1Centre for Health, Activity, and Rehabilitation Research, School of Physiotherapy, University of Otago, PO Box 56, Dunedin 9054, New Zealand.

Background:
Mechanical insufflation-exsufflation (MI‑E) is recommended to support secretion clearance for people with neuromuscular disorders (NMD) with ineffective cough. Limited research has examined, within one study, how people with NMD and physiotherapists understand MI‑E provision and use, and how this may influence access and outcomes. The study aimed to explore areas of alignment and difference in experiences, priorities, and decision-making to identify service gaps and inform person-centred care.
Design:
A qualitative multi‑sample study, analysed using reflexive thematic analysis.
Methods:
Semi-structured interviews were conducted with people with NMD and physiotherapists, and free-text survey responses were obtained from physiotherapy leaders. Participants included 15 people with NMD (plus 9 supporters), 9 physiotherapists, and 19 physiotherapy leaders. Data were coded inductively, and themes were developed iteratively.
Results:
Three overarching themes were identified. (1) Negotiating safety and responsibility: physiotherapists prioritised responsibility, while people with NMD emphasised survival and timely access; labels such as 'reliance' and 'palliative care' influenced when MI‑E was offered and accepted. (2) MI‑E in everyday life: participants highlighted benefits beyond acute illness, including more predictable breathing, home-based routines, and social participation. (3) Building capability: variable service capability and resourcing affected physiotherapist support for MI‑E, while users developed practical expertise through routine MI-E use.
Conclusions:
Differences in how risk, responsibility, and expertise are understood influence MI‑E timing, titration, and perceived purpose. Person‑centred decision‑making, that links physiological indicators with quality‑of‑life and participation goals, supported by clinician training, may improve equitable MI‑E access and outcomes. CONTRIBUTION OF THE PAPER.