Related Experiment Video
Updated: Oct 29, 2026
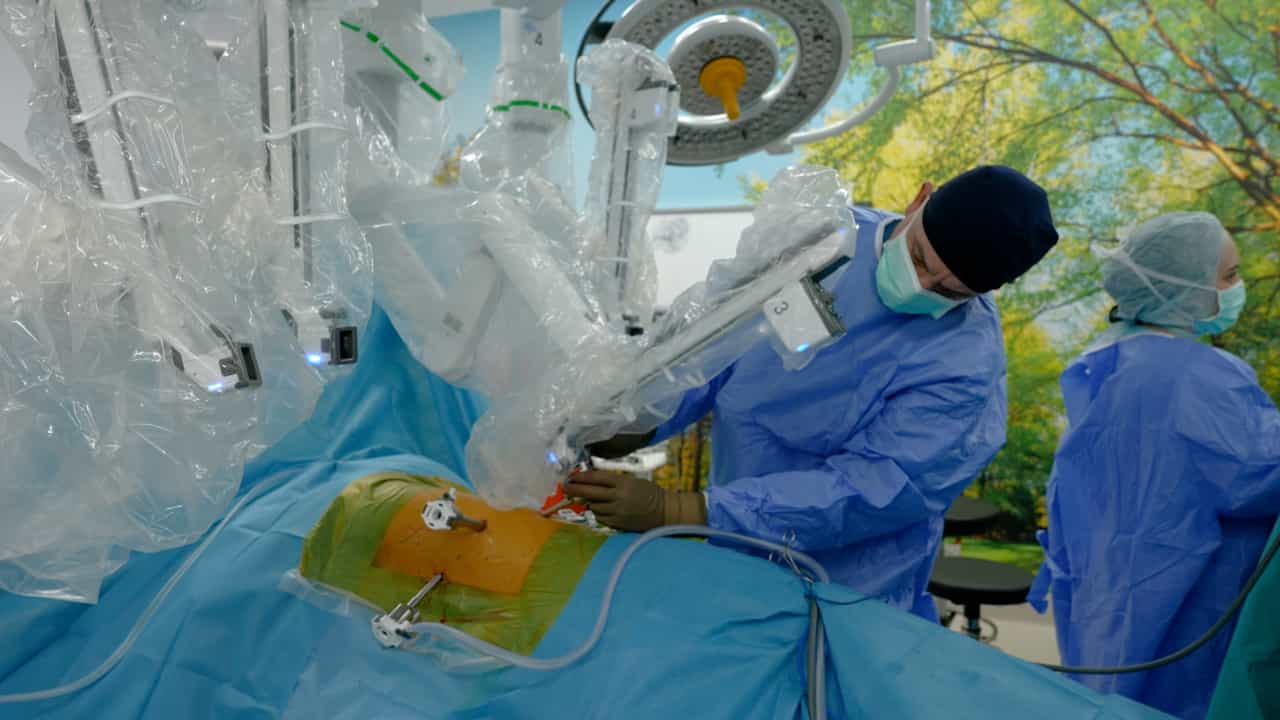
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Contemporary chest drain practice after pulmonary resection: A multicenter registry study of drain strategy,
Akshay J Patel1,2, Rebecca Weedle3, Abdullah Al-Shammari1
1Department of Thoracic Surgery, Guy's Hospital, Guy's and St Thomas' NHS Foundation Trust, London, England, United Kingdom.

Objectives:
Chest drain management after pulmonary resection varies widely, particularly with respect to drain size, use of digital systems, and suction strategy. Although smaller drains and digital drainage systems are increasingly adopted, robust real-world data evaluating their impact on clinically relevant outcomes are limited. Using a large contemporary multicenter registry, we evaluated associations between chest drain characteristics and postoperative outcomes, and quantified center-level variation in drain practice.
Methods:
A prospective multicenter observational registry including 3348 patients undergoing pulmonary resection across 21 international centers was analyzed. Patient, disease, operative, and drain-related variables were recorded. Primary outcome was prolonged air leak (>5 days). Secondary outcomes included pulmonary complications, surgical emphysema, pleural readmission, length of stay, drain duration, and in-hospital mortality. Multivariable regression models adjusted for patient, operative, and center-level factors were constructed. Center-level variation in drain practice and outcomes was examined descriptively and using funnel plots.
Results:
The cohort comprised 3348 patients, of whom 88% underwent minimally invasive resection. Prolonged air leak occurred in 9.0%, pulmonary complications in 7%, and in-hospital mortality in 0.9%. Larger drain size was independently associated with lower odds of prolonged air leak (adjusted odds ratio per 1Fr increase ≈1.12), whereas digital drainage systems were associated with higher detected prolonged air leak but shorter length of stay. Substantial center-level variation was observed in digital drain adoption, median drain size, and prolonged air leak rates, exceeding expected random variation in several centers. Reanalysis incorporating 3 additional international centers demonstrated no material change in adjusted effect estimates.
Conclusions:
In this large contemporary registry, chest drain strategy was independently associated with postoperative outcomes after pulmonary resection. Marked intercenter variation in drain practice persists, underscoring the need for evidence-based standardization. These real-world data provide a platform to rationalize chest drain management and inform future pragmatic trials.
Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:27
Pneumothorax-II
Clinical Manifestations: