Related Experiment Video
Updated: Oct 29, 2026
Innovative Strategies for Organ Preservation in Heart Transplantation: Uniform Cooling Preservation and Ex-situ Normothermic Perfusion
Published on: November 28, 2025
Beating heart transplantation after normothermic machine perfusion: A single institution experience
Samuel J Kesseli1, Abigail R Benkert1, Divyam Goel2
1Division of Cardiovascular and Thoracic Surgery, Duke University Hospital, Durham, NC.

Objective:
The beating heart implantation technique represents a recent innovation in heart transplantation hypothesized to mitigate ischemia-reperfusion injury. Prior case series have suggested an association with reduced incidence of primary graft dysfunction. The objective of this case series is to describe our transplant center's initial experience and outcomes using this technique.
Methods:
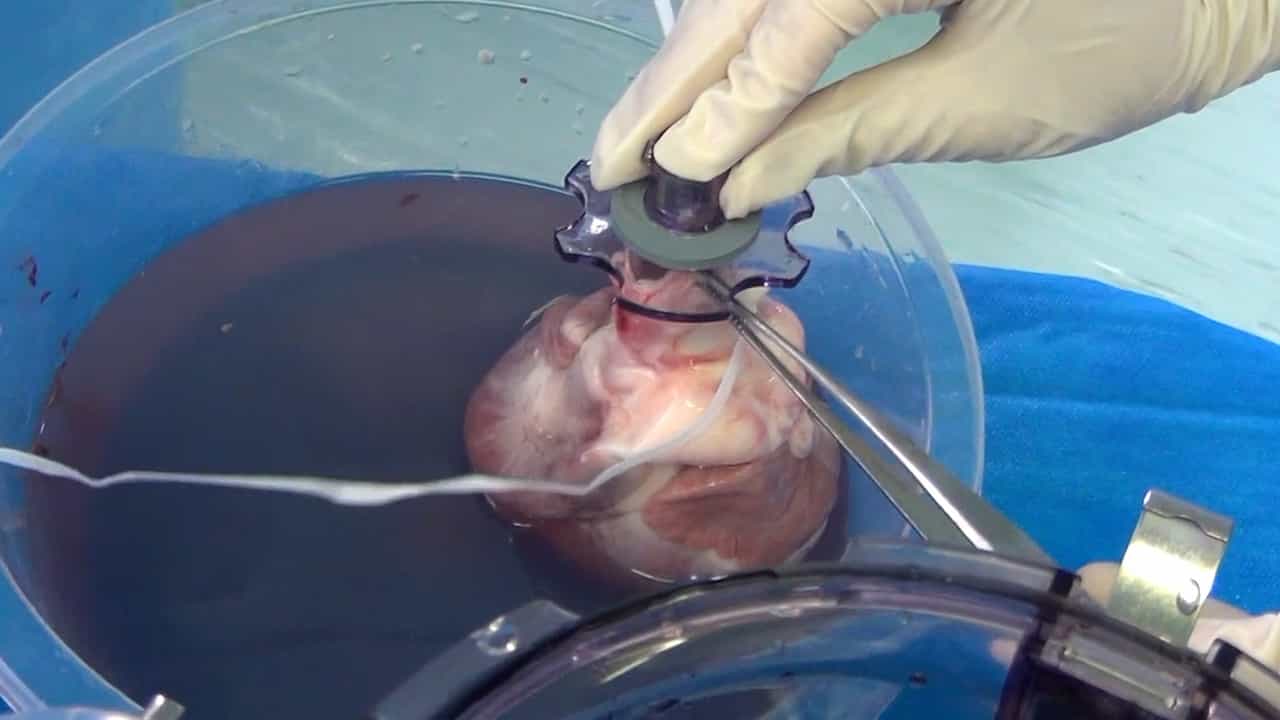
During a 1-year study period spanning from October 2024 to October 2025, our center performed 48 heart transplants using a modified beating heart implantation technique. Our protocol differs from previously reported techniques, in that the allograft is cooled to 18 °C at completion of normothermic machine perfusion and then immediately perfused with warm (34 °C-36 °C) blood at a rate of 100 to 150 mL/min upon removal from normothermic machine perfusion.
Results:
Of 48 beating heart recipients, 5 were excluded from the analysis (4 multiorgan recipients and 1 patient death unrelated to the allograft function [iatrogenic aortic dissection]). Of the remaining 43 recipients, 34 received donation after circulatory death grafts and 9 received donation after brain death grafts. The median recipient and donor ages were 54 [interquartile range, 48-60] years and 36 [interquartile range, 29-43.5] years, respectively. The total preservation time was 357 [interquartile range, 320-469] minutes, and the beating heart implantation was a median of 55 [interquartile range, 46.5-61] minutes. Seven patients (16.3%) had severe primary graft dysfunction requiring extracorporeal membrane oxygenation or right ventricular assist device; of these, 5 were donation after circulatory death recipients. Comparing perfusion parameters between patients with versus without primary graft dysfunction, the median temperature, root flow, and perfused volume were similar. The median root line pressure was higher among those who experienced severe primary graft dysfunction compared with those who did not: 104 [interquartile range, 81-126] mm Hg versus 76 [interquartile range, 65-91] mm Hg (P = .005). Median partial pressure of oxygen was also higher in those with severe primary graft dysfunction: 315 [interquartile range, 264-321] mm Hg versus 248 [interquartile range, 234-271] mm Hg (P = .021). Of the 43 included recipients, all were alive 30 days post-transplant.
Conclusions:
The beating heart implantation method during transplantation avoids a second cardioplegic arrest period and thereby theoretically reduces organ ischemia time. In this single-center series, we observed a primary graft dysfunction rate greater than in our prior institutional experience before introducing the technique; as such, we have cautiously halted routine use of beating heart implantation. Future studies should assess both donor and recipient risk factors, as well as perfusion parameters and the role of cooling that may impact graft function despite beating heart implantation.