Measured, not labelled: un-analyzable input versus misclassification in single-lead wearable ECG
Related Experiment Video
Updated: Oct 30, 2026
Patient Directed Recording of a Bipolar Three-Lead Electrocardiogram using a Smartwatch with ECG Function
Published on: December 11, 2019
Yunfei Cheng1, Peng Deng1, Yun Lian1
1Health Technology and Engineering Research Center, SKG Health Technologies Co., Ltd., 23A Floor, Building 3, Zhongke R&D Park, No.009, Gaoxin South 1st Road, High-tech Zone Community, Yuehai street, Nanshan District, Shenzhen, Guangdong, 518063, China.

Objective:
Wearable single-lead ECG has expanded arrhythmia screening, but many recordings are inconclusive, and each corpus defines that word differently. We ask how much deployment error is un-analyzable input rather than misclassification when analyzability is measured with one instrument. Approach. We evaluate three diagnostic databases in-domain and leave-dataset-out under a strict loss counting windows carrying each corpus's inconclusive label as errors unless deferred. We score analyzability with an unsupervised morphological criterion calibrated against three experts on free-living ECG. Reference unreadability is sparse and imbalanced: only seven of 15 subjects contain an unreadable window and one supplies 88% of all unreadable windows. Thresholded sensitivity and every prevalence or true-share correction are therefore exploratory. Main results. The criterion flags almost all expert-unreadable windows but only subsets of the windows labelled inconclusive by their corpora: an inconclusive rate measures convention as much as signal. At tau_a = 0.50, criterion-positive windows are 8.1%, 56.7% and 69.6% of the strict proxy loss on Holter, handheld and patch. The true-share point intervals lie below 50% on handheld and above it on patch, but joint calibration-and-sampling envelopes span 50% on both and still do at the Youden threshold 0.60. On handheld, the calibration-only envelope is more than twice as wide as the corpus-sampling-only envelope. Gate-versus-confidence ordering changes with the accounting and corpus; no general selective-risk advantage of the gate is established. Significance. Corpus labels, criterion flags and latent expert unreadability must not be conflated. A gate can win by predicting a labelling convention, and this retrospective study validates neither transfer to smartwatch dry electrodes nor improvement in patient outcomes. Measure the inconclusive rate with a stated criterion on the raw signal; do not inherit it from a corpus label.

Related Concept Videos
 01:29
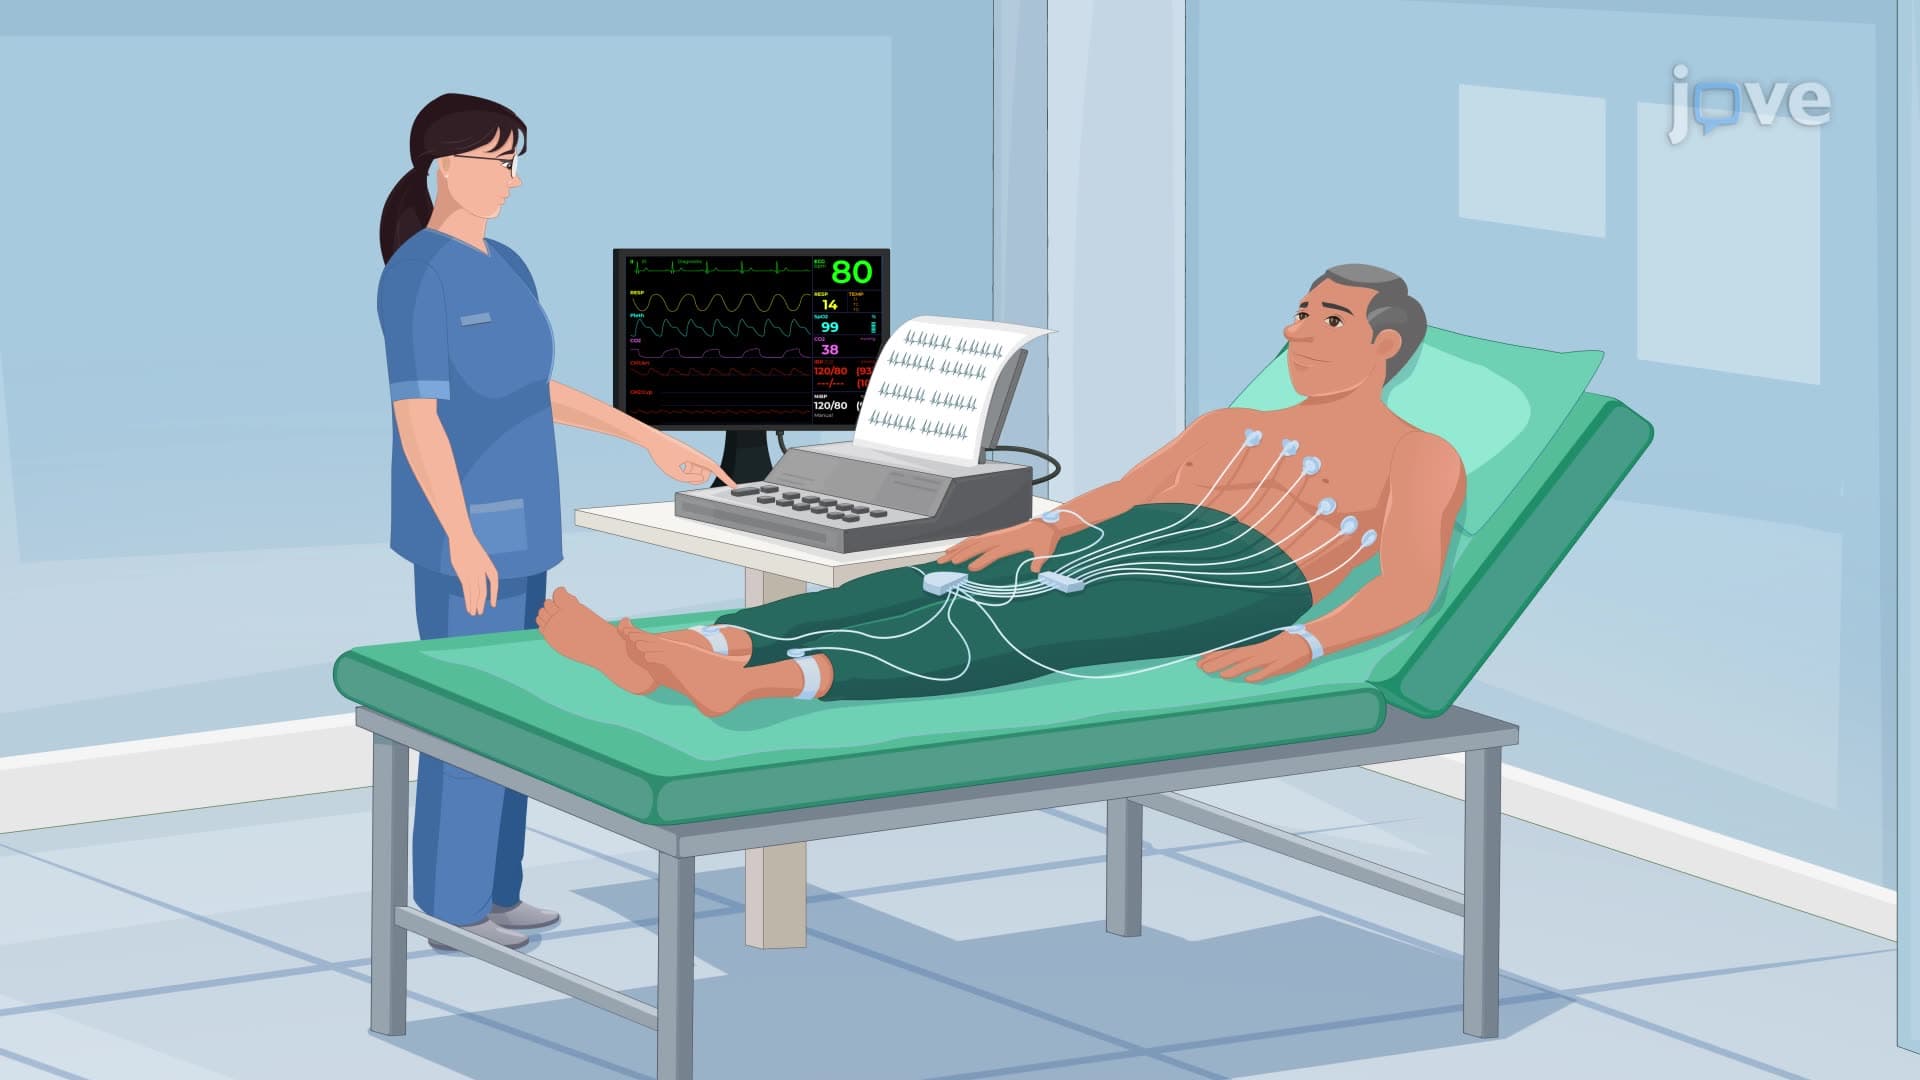
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:28
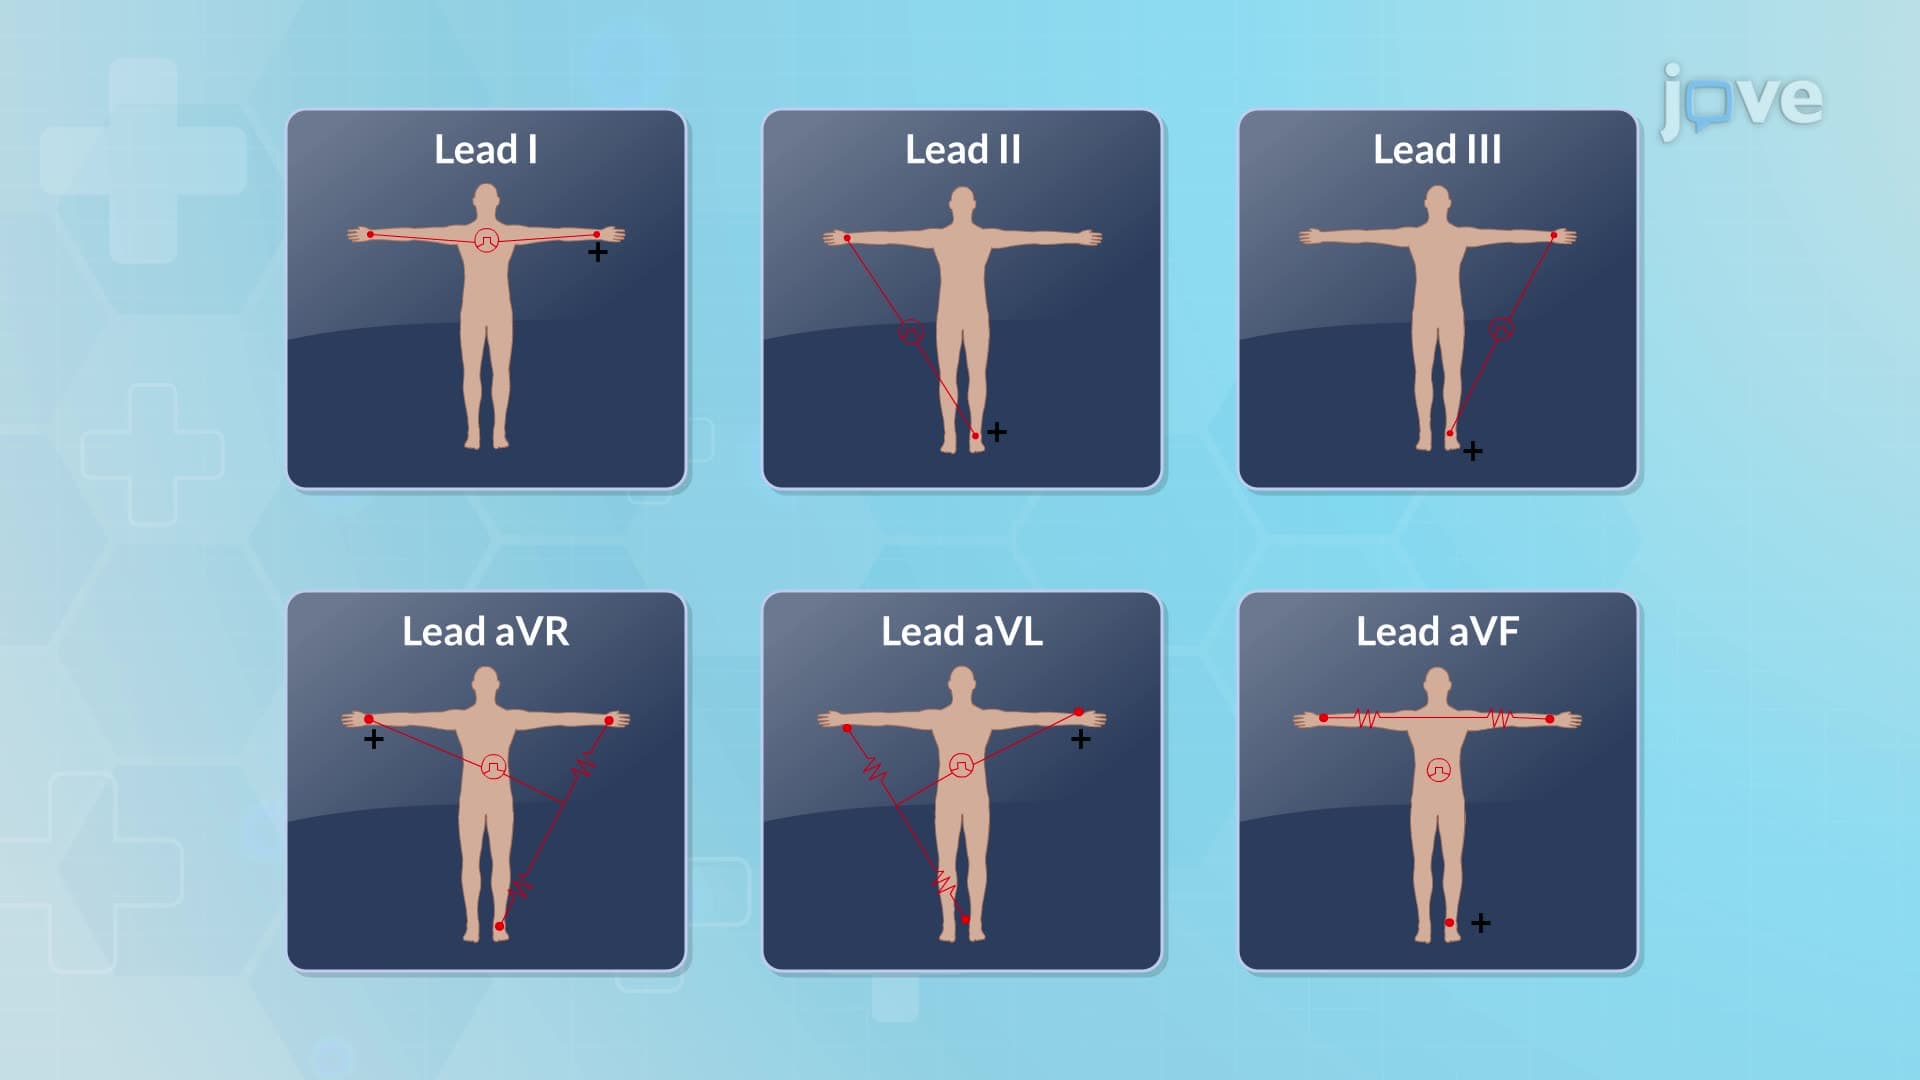
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:23
Holter Monitor: 24-Hour Monitoring
 01:25
Instrumentation Amplifier
To overcome this challenge, an ECG machine utilizes an instrumentation amplifier. This specialized amplifier is...
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage. When...
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...