Hiatal Hernia and Conclusive Gastroesophageal Reflux Disease: Size Matters
Related Experiment Video
Updated: Oct 31, 2026

Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Juan S Hernández1,2, Albis C Hani1,3, Oscar M Muñoz1,2
1Department of Internal Medicine, Pontificia Universidad Javeriana, Bogotá Dc, Colombia.

Background/Aims:
: The Lyon Consensus considers hiatal hernia (HH) as a supportive metric for the diagnosis of gastroesophageal reflux disease (GERD) when evidence is inconclusive; however, HH size is not taken into consideration. We aimed to correlate HH size with conclusive evidence of GERD from multichannel intraluminal impedance and pH monitoring (MII-pH) and upper endoscopy.
Methods:
: We analyzed a retrospective consecutive cohort of patients with suspected GERD with and without HH on high-resolution manometry who also underwent upper endoscopy and MII-pH monitoring off therapy within a ≤6 month interval. HH was categorized as none, small (<3 cm), medium (3-5 cm), or large (>5 cm). Pathological acid exposure time (AET, >6%), endoscopic GERD findings, and adjunctive MII-pH metrics were compared and correlated between subsets based on the presence and size of HH.
Results:
: Of the 456 included patients, 337 (73.9%) had HH as follows: small HH, 114; medium HH, 117; and large HH, 106. Pathological AET showed a stepwise increase from 19.3% in the no HH group to 41.2% in the small HH group, 51.3% in the medium HH group, and 83.0% in the large HH group (P < 0.001). The prevalence of erosive esophagitis increased similarly (7.6%, 14.9%, 17.9%, and 43.4%, respectively; P < 0.001). DeMeester score, total reflux episodes (TREs), and mean nocturnal baseline impedance (MNBI) showed similar findings (all P < 0.001), but the prevalence of peptic stricture (P = 0.263) and Barrett's esophagus did not differ significantly (P = 0.108). HH size correlated positively with AET (rho = 0.49) and TRE (rho = 0.53) and negatively with MNBI (rho = -0.46; all P < 0.001).
Conclusions:
: Evidence for conclusive GERD increases with HH size, supporting its role as a key anatomical marker for GERD assessment using the Lyon Consensus 2.0 criteria.

Related Concept Videos
 01:25
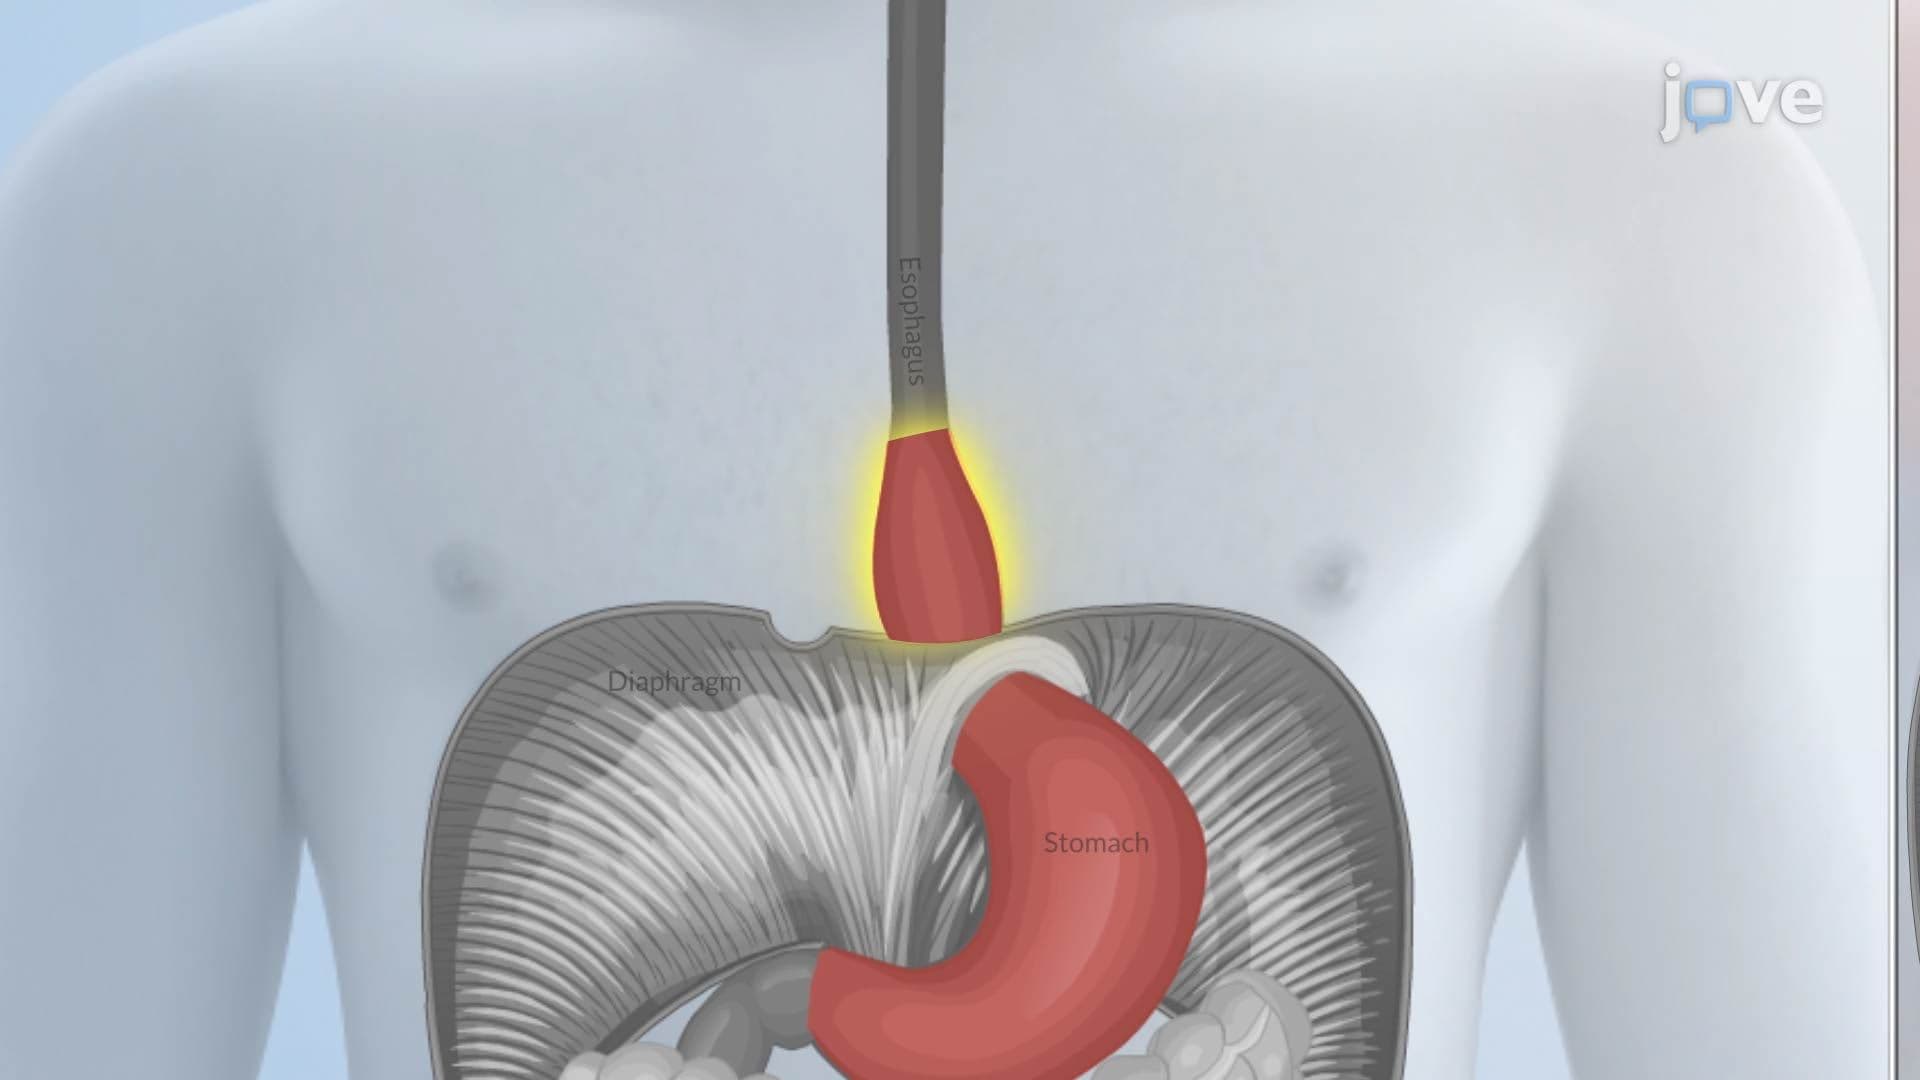
Hiatal Hernia
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:25
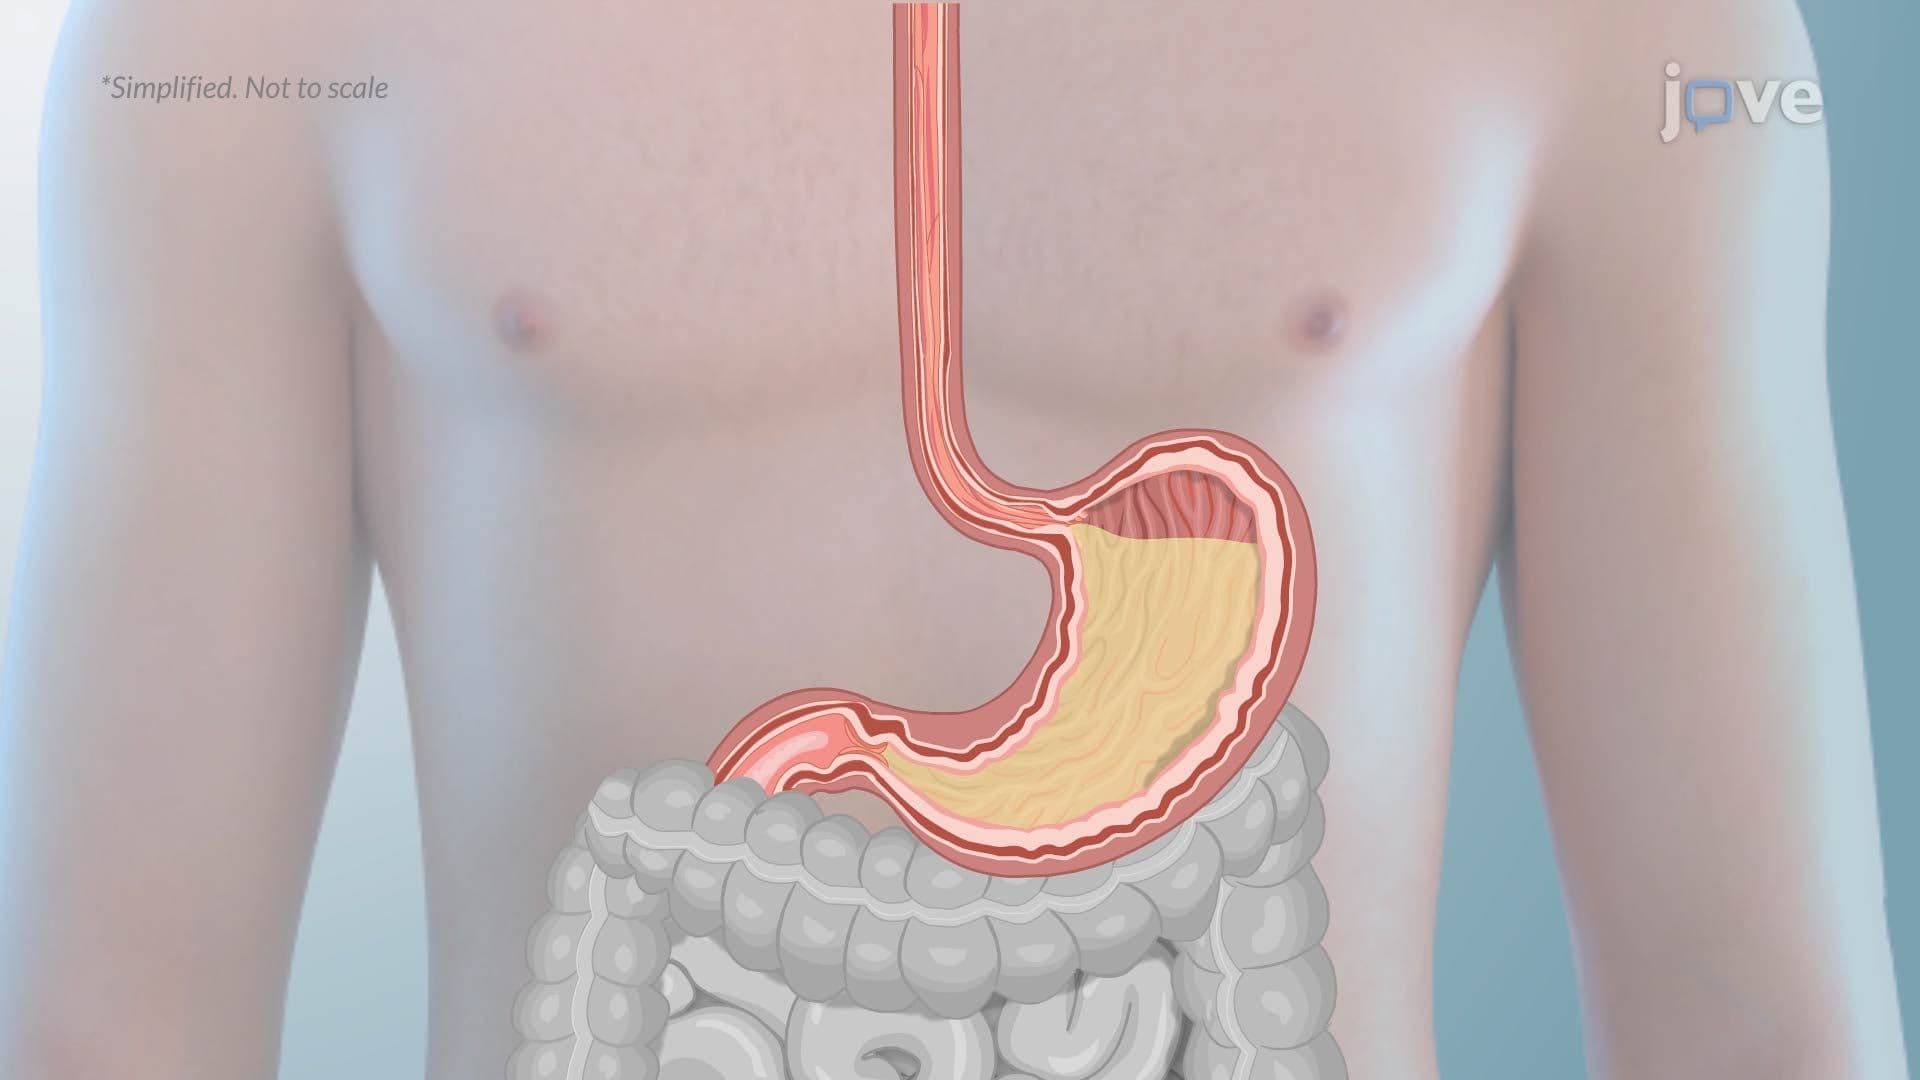
Gastroesophageal Reflux Disease
 01:29
Gastroesophageal Reflux Disease I: Meaning and Pathophysiology
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...