Screening opportunity gap in COPD evaluation after low-dose CT findings: implications for risk-based spirometry in primary care
Related Experiment Video
Updated: Oct 31, 2026
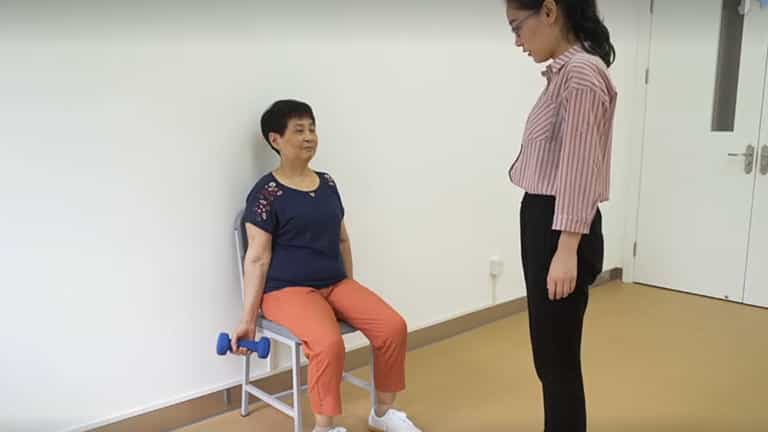
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Takamasa Hotta1, Mika Nakao1, Shintaro Shimizu1
1Department of Internal Medicine, Division of Medical Oncology & Respiratory Medicine, Shimane University Faculty of Medicine, 89-1 Enya-cho, Izumo, Shimane, 693-8501, Japan.

Background:
Low-dose chest computed tomography (CT) frequently detects findings suggestive of chronic obstructive pulmonary disease (COPD). However, the pathway from CT detection to physiological confirmation remains poorly characterized in real-world clinical practice. This study evaluated follow-up pathways after CT findings suggestive of COPD and assessed whether simple clinical factors could identify individuals at high risk of airflow limitation.
Methods:
This retrospective observational study analyzed data from a voluntary, self-paid, community-based low-dose chest CT screening program in Japan that was open regardless of age or smoking history. Among 34,425 examinations conducted from fiscal year 2015 through February 2025, 1,336 examinations referred for suspected COPD were analyzed. Follow-up pathways were categorized as no documented follow-up, follow-up without spirometry, and follow-up with spirometry. Two multivariable logistic regression models evaluated documented follow-up and spirometry use. Airflow limitation was defined as a post-bronchodilator FEV₁/FVC ratio < 0.70.
Results:
Among 1,336 examinations, 305 (22.8%) had no documented follow-up, 556 (41.6%) had documented follow-up without spirometry, and 475 (35.6%) had documented follow-up with spirometry. Among those who underwent spirometry, airflow limitation was identified in 298 (62.7%). Current smoking was associated with lower documented follow-up, whereas older age and greater cumulative smoking exposure were associated with spirometry use. Concurrent suspicion of lung cancer was associated with a lower likelihood of spirometry use. Airflow limitation rates increased according to simple clinical risk factors. Examinations with all three risk factors-age ≥ 70 years, pack-years ≥ 40, and respiratory symptoms-had an airflow limitation prevalence of 79.8%. Notably, 90 examinations without spirometry met these high-risk criteria.
Conclusion:
In this community-based CT screening program, substantial gaps were observed in documented follow-up after referral for suspected COPD and subsequent spirometry use despite the high prevalence of airflow limitation among those tested. Simple clinical factors may help identify high-risk individuals and improve targeted spirometry use in routine clinical practice.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction