Two-Dimensional Electromagnetic Navigation-Assisted Percutaneous Transforaminal Endoscopic Discectomy for Lumbar Disc Herniation: A Retrospective Comparative Study
Related Experiment Video
Updated: Oct 31, 2026
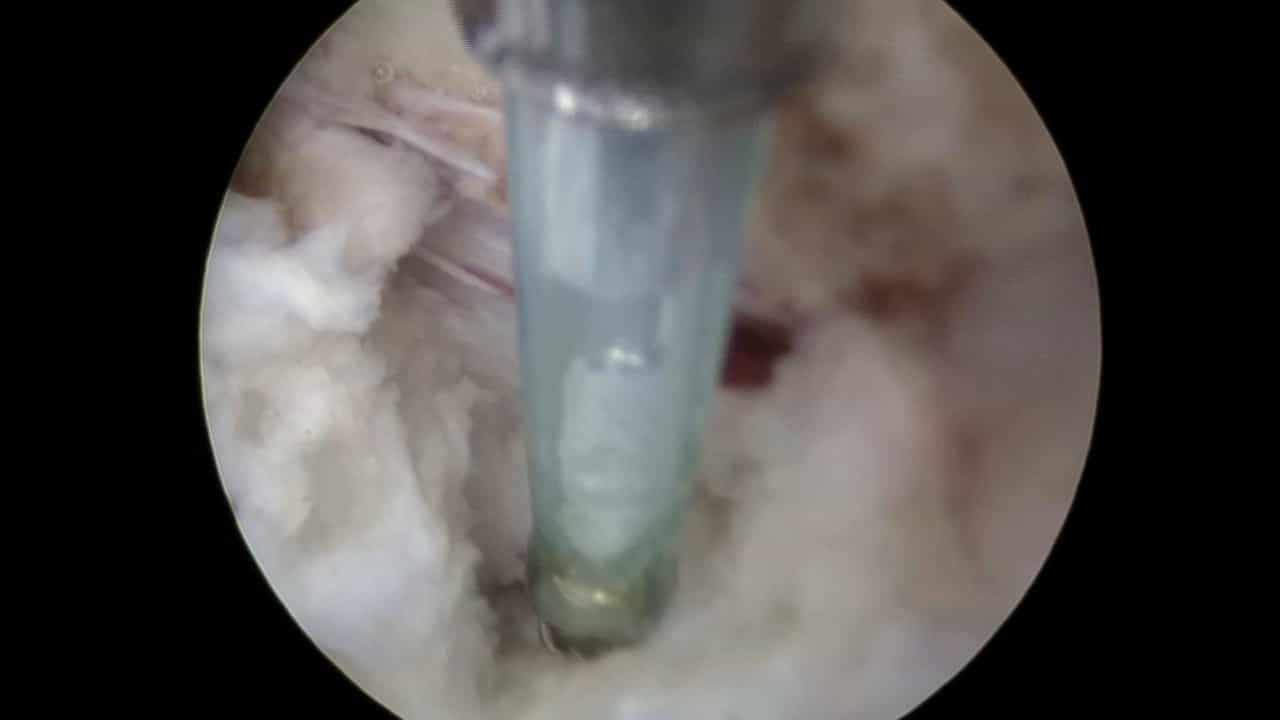
A Mobile Outside-in Technique of Transforaminal Lumbar Endoscopy for Lumbar Disc Herniations
Published on: August 7, 2018
Zhong Wei1,2, Haoyu Cheng1,2, Ren Gao2,3
1Hubei University of Medicine, Shiyan, Hubei, China.

Objective:
To compare the clinical performance, safety, radiation exposure, and learning curve of two-dimensional (2D) electromagnetic navigation-assisted percutaneous transforaminal endoscopic discectomy (PTED) with those of three-dimensional (3D) electromagnetic navigation-assisted PTED in patients with lumbar disc herniation (LDH).
Methods:
This retrospective cohort study included 82 patients with LDH who underwent PTED between January 2022 and June 2024. Patients were classified into the 2D electromagnetic navigation group or the 3D electromagnetic navigation group according to the navigation workflow used during surgery. Perioperative variables, including total operative time, navigation registration time, radiation exposure, and complications, were recorded. Clinical outcomes were assessed using the visual analogue scale (VAS), Oswestry Disability Index (ODI), and modified MacNab criteria. Learning curves for both the surgeon and the radiologic technologist were evaluated using cumulative sum (CUSUM) analysis.
Results:
Compared with the 3D group, the 2D group demonstrated a significantly shorter total operative time (66.64 ± 9.67 vs. 88.92 ± 15.98 min, p < 0.001), shorter navigation registration time (6.37 ± 0.93 vs. 12.25 ± 2.11 min, p < 0.001), and lower radiation exposure (1.77 ± 0.17 vs. 7.24 ± 0.56 mGy, p < 0.001). Longitudinal analysis using linear mixed-effects models demonstrated significant time effects for VAS of back, VAS of leg, and ODI (all p < 0.001), indicating significant postoperative improvement in both groups. No significant main effect of group was observed for VAS of back, VAS of leg, or ODI. The group-by-time interaction was not significant for VAS of leg (p = 0.774), but was significant for VAS of back (p = 0.007) and ODI (p < 0.001), suggesting differences in the temporal recovery patterns between groups for these two outcomes. According to the modified MacNab criteria, favorable final outcomes were achieved in both groups, with no significant between-group difference. The learning curve was shorter in the 2D group, with proficiency reached by the 16th case for the surgeon and the 14th case for the radiologic technologist, compared with the 3D group. No significant between-group difference was observed in complication rates.
Conclusion:
2D electromagnetic navigation-assisted PTED is a safe and clinically effective alternative to 3D electromagnetic navigation-assisted PTED for the treatment of LDH. Relative to the 3D workflow, the 2D approach offers greater procedural efficiency, reduced radiation exposure, and a shorter learning curve. Although longitudinal analysis revealed different recovery patterns over time for low back pain and ODI between the two groups, both techniques achieved substantial postoperative improvement, favorable final clinical outcomes, and comparable safety. These findings suggest that simplified 2D electromagnetic navigation may represent a more practical and scalable option for routine clinical application.