Hyperdominant Left Circumflex Artery Challenging Conventional Paradigms and Current Guideline Recommendations: A Comprehensive Literature Review and Case Series
Amirmahdi Mohammadi1,2, Mohammad Sadegh-Vashveshady3
1Department of Cardiovascular Surgery, School of Medicine Semnan University of Medical Sciences Semnan Iran.

Abstract:
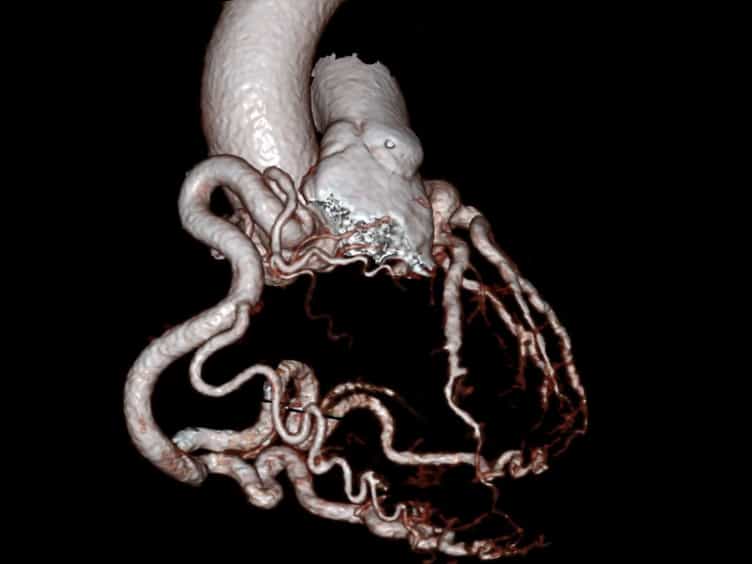
Despite its rarity in the general population, left dominant coronary circulation with a hyperdominant left circumflex artery (LCx) has been associated with a more severe risk for ischemic and coronary artery disease. The concealment of an isolated posterior myocardial infarction (IPMI) on a standard 12-lead ECG among these patients with distinctive coronary anatomy can be concerning, especially when clinicians become trapped within conventional guideline-based diagnostic criteria, a circumstance that may ultimately be linked to a poorer prognosis. We present two cases that posed unique diagnostic challenges in this specific anatomical context. Case 1: A 63-year-old man presented to the emergency department (ED) with typical anginal chest pain and severe fatigue. Although the patient was initially diagnosed with non-ST-elevation myocardial infarction (NSTEMI), eventually a catastrophic occlusion of the left posterior descending artery (PDA) in the setting of a hyperdominant LCx was seen during coronary angiography (CAG). Case 2: A 69-year-old man arrived at the ED with typical angina, described as pressure-like. Although the serial 12-lead ECGs were completely normal, given the clinical context, the patient underwent an immediate invasive strategy in < 2 h. CAG revealed complete occlusion of the ostio-proximal segment of the left PDA. In both cases, hyperdominant LCx anatomy created a diagnostic blind spot within the conventional STEMI/NSTEMI paradigm, because the infarct territory was insufficiently captured by standard ECG criteria and failed to trigger guideline-based use of posterior leads or adjunctive imaging, thereby obscuring the diagnosis of IPMI. These cases warn clinicians about the diagnostic complexity of IPMI in a hyperdominant LCx setting. In such cases, ECG findings can be ambiguous or even completely absent, and the clinical presentation may not meet current unclear guideline-based indications for adjunctive diagnostic assessment, leading to delayed recognition of high-risk ischemia, particularly IPMI.
More Related Videos
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:11
Overview of Systemic Arteries
Systemic circulation is the part of the cardiovascular system that carries oxygenated blood away from the heart to the body's tissues and returns deoxygenated blood back to the heart.
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests