Can randomized trials realistically detect patient benefit from robotic-assisted reverse shoulder arthroplasty?
Related Experiment Video
Updated: Nov 2, 2026
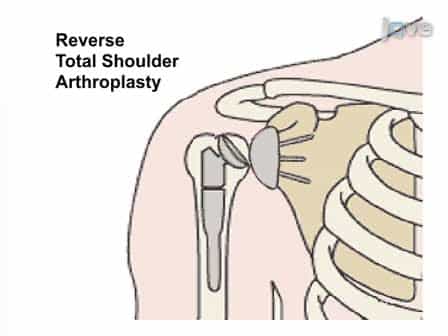
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Eoghan T Hurley1, Matthew Frederickson2, Joaquin Sanchez-Sotelo3
1Department of Orthopaedic Surgery, Duke University, Durham, NC, USA.

Background:
Robotic-assisted reverse total shoulder arthroplasty (rTSA) aims to improve implant positioning and plan fidelity, but whether these technical advantages translate into measurable patient benefit remains unknown. The purpose of this study was to determine how large randomized trials comparing robotic-assisted with conventional rTSA would need to be to detect differences in revision rates and patient-reported outcomes.
Methods:
A 2-arm parallel randomized trial was modeled with 1:1 allocation, 2-sided alpha of 0.05, and 80% power. Revision endpoint calculations used standard 2-proportion formulas under a baseline revision rate of 4%, with hypothetical absolute risk reductions (ARR) attributable to robotic assistance ranging from 0.5% to 3.0%. American Shoulder and Elbow Surgeons endpoint calculations used standard 2-mean formulas, modeling robotic-attributable between-group differences of 1 to 5 points under standard deviation (SD) assumptions of 15 and 20 points.
Results:
Under a baseline revision rate of 4%, detection of a 0.5% ARR in revision surgery required 22,663 patients per group; a 1.0% ARR required 5,301; a 2.0% ARR required 1,141; and a 3.0% ARR required 424. For American Shoulder and Elbow Surgeons with SD 15, detection of a 1-point between-group difference required 3,532 patients per group; a 2-point difference required 883; a 3-point difference required 393; a 4-point difference required 221; and a 5-point difference required 142. Under SD 20, corresponding values ranged from 6,280 to 252 patients per group.
Conclusion:
Randomized trials of robotic-assisted rTSA would require very large patient enrollment to detect the small reductions in revision surgery and modest improvements in patient-reported outcomes most plausibly attributable to the technology. These findings suggest that a feasible conventional trial may be poorly suited to detect, or confidently exclude, small advantages of robotic assistance. The next phase of study should therefore prioritize longer-term comparative analyses and focused evaluation of anatomically or clinically higher-risk subgroups, in whom the technology's effect may be larger and more detectable.
More Related Videos
 04:38
Application of Bedside Lower Extremity Rehabilitation Robots in Stroke Rehabilitation: A Randomized Controlled Trial
Published on: November 28, 2025
 03:07
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025