Shortened staged head-up tilt testing for pediatric vasovagal syncope: a retrospective derivation study
Related Experiment Video
Updated: Nov 2, 2026
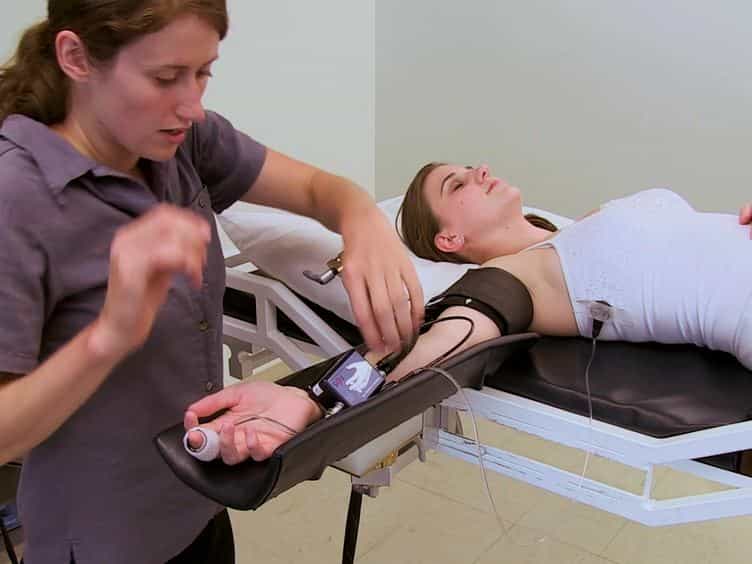
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Shuo Wang1, Yao Lin1,2, Jing Zhang1,2
1Capital Center for Children's Health, Capital Medical University, Capital Institute of Pediatrics, Beijing, 100020, China.

Background:
The head-up tilt test (HUTT) is a primary diagnostic method for vasovagal syncope (VVS) in pediatric patients, yet conventional protocols are lengthy and may impose a substantial procedural burden on children and adolescents. Accordingly, this study aimed to characterize phase-specific time-to-positivity patterns and to identify candidate shortened protocol of each HUTT phase for future prospective validation.
Methods:
Between November 2023 and March 2025, 511 pediatric patients underwent HUTT. After excluding non-VVS cases and incomplete tests, 345 patients were included. Data on the baseline head-up tilt phase (BHUT) initiation to first positive response were collected. Temporal changes in diagnostic yield were analyzed using Kaplan-Meier analysis and tracking new positive cases in 5-min intervals. Bootstrap resampling was used to assess the internal stability of phase-specific thresholds and projected retention estimates.
Results:
A total of 345 patients (aged 11.5 ± 2.5 years; 39.4% boys) were included, with 266 patients undergoing the sublingual nitroglycerin-potentiated head-up tilt (SNHUT). Among them, 87.0% tested positive, with 22.9% during BHUT and 64.1% during SNHUT. Positive results during BHUT occurred around 15.6 min (IQR 10.5-20.9), mainly within 10-20 min. In SNHUT, positive results appeared faster, around 6.3 min (IQR 4.7-7.7), mostly within the first two 5-min windows. The candidate BHUT 20-min + SNHUT 10-min protocol was projected to retain 82.3% of the observed positive responses (95% CI 77.7%-86.3%).
Conclusions:
Positive responses to HUTT in children and adolescents are most frequent within the first 20 min post-tilt and the initial 10 min during SNHUT. A shortened protocol (20-min BHUT + 10-min SNHUT) may serve as a potential candidate based on retrospective truncation analysis, yet prospective validation remains mandatory prior to clinical adoption.