How Much Do Horizontally Referenced and Interteardrop-referenced Acetabular Coverage Indices Differ During Standing in Adults With Hip Pain?
Related Experiment Video
Updated: Nov 3, 2026
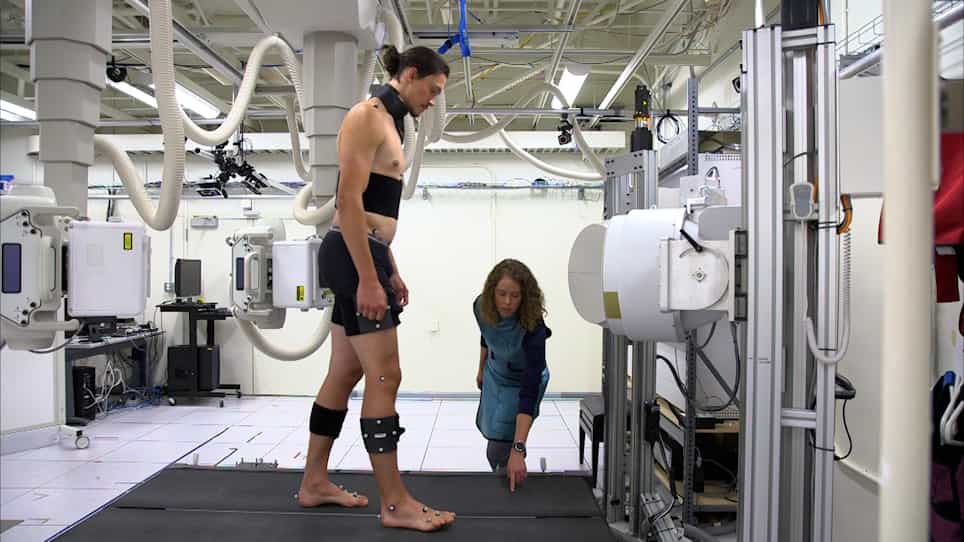
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Riley Cousins1, Moritz Wagner2,3, Megha Rao1
1Faculty of Medicine, University of Ottawa, Ottawa, Ontario, Canada.

Background:
Acetabular coverage is conventionally assessed using the lateral center-edge angle (LCEA) and acetabular index. However, on standing radiographs, these measurements may be referenced either to the pelvis or to the weightbearing horizontal. Whether selection of these reference lines leads to clinically relevant differences in acetabular coverage interpretation is uncertain.
Questions/Purposes:
(1) How do horizontally referenced and interteardrop-referenced LCEA and acetabular index measurements compare in patients with nonarthritic hip pain? (2) How are the magnitude and direction of pelvic obliquity associated with differences between horizontally referenced and interteardrop-referenced acetabular coverage measurements? (3) What are the magnitude and direction of pelvic obliquity in young adults undergoing assessment for unilateral nonarthritic hip pain? (4) How are hip-length discrepancy measures based on the lesser trochanter and hip center of rotation associated with the magnitude and direction of pelvic obliquity?
Methods:
In this retrospective comparative study, 598 patients evaluated at a tertiary-referral young-adult hip clinic between June 2021 and June 2025 were identified; 10% (60 of 598) were excluded for bilateral hip involvement or prior procedures, 5% (28 of 598) for insufficient radiographs, and 3% (17 of 598) for age 50 years or older, leaving 493 patients age 16 to 49 years with unilateral nonarthritic hip conditions and standing AP pelvic radiographs to be included. The mean ± SD age was 35 ± 8 years; 39% (191 of 493) were male. Diagnoses included dysplasia; cam-type, mixed, and pincer-type femoroacetabular impingement; isolated labral tears; and other nonarthritic hip conditions. In each hip, LCEA and acetabular index were measured using horizontal and interteardrop-referenced measurements, and classification disagreement was assessed using LCEA (< 20°, 20° to 25°, 25° to 40°, > 40°) and acetabular index (< 0°, 0° to 10°, > 10°) categories. Associations between pelvic obliquity magnitude and measurement-difference magnitude were assessed using linear regression, with directional relationships assessed graphically. Pelvic obliquity was measured as the angle between the interteardrop and horizontal reference lines, with direction defined relative to the clinically evaluated side. Hip-length discrepancy measures based on the lesser trochanter and hip center of rotation were compared across pelvic obliquity magnitude and direction groups. After interrater standardization, each patient was randomly allocated to one of two observers, who performed all measurements for that patient; a third observer reviewed a random sample. Interobserver intraclass correlation coefficients ranged from 0.69 to 0.87.
Results:
Mean ± SD absolute differences between horizontally referenced and interteardrop-referenced measurements were 2° ± 1° for both LCEA and acetabular index. Classification disagreement occurred in 14% (69 of 493) using LCEA-based categories and 10% (51 of 493) using acetabular index-based categories, most notably when interteardrop-referenced LCEA indicated borderline dysplasia and horizontally referenced LCEA indicated normal coverage (29% [28 of 95]). Each 1° increase in pelvic obliquity magnitude was associated with an approximately 1° greater measurement difference for LCEA (β = 0.89 [95% confidence interval (CI) 0.86 to 0.93]; R2 = 0.86; p < 0.001) and acetabular index (β = 0.90 [95% CI 0.87 to 0.93]; R2 = 0.88; p < 0.001). Mean absolute pelvic obliquity magnitude was 2° ± 1°; 40% (197 of 493) had pelvic obliquity of 2° to < 5° and 3% (14 of 493) had pelvic obliquity ≥ 5°. The clinically evaluated hemipelvis was abducted in 44% (218 of 493), adducted in 39% (192 of 493), and neutral in 17% (83 of 493). Lesser trochanter-based hip-length discrepancy was 2 ± 2 mm with a neutral pelvis, 3 ± 3 mm with abduction, and 4 ± 3 mm with adduction (p < 0.001), and increased from 3 ± 3 mm to 5 ± 3 mm and 7 ± 3 mm across increasing pelvic obliquity magnitude categories (p < 0.001). Hip center of rotation-based values were 2 ± 2 mm in all three direction groups (p = 0.03) and 2 ± 2 mm, 3 ± 2 mm, and 3 ± 3 mm across increasing magnitude categories (p = 0.22).
Conclusion:
These findings indicate that horizontally referenced and interteardrop-referenced measurements can yield discordant acetabular coverage estimates and radiographic classifications for the same patient. As standing radiographs become more widely incorporated into hip evaluation, comparison of horizontally referenced and interteardrop-referenced LCEA and acetabular index measurements may provide additional information by revealing pelvic-obliquity-associated differences in measured coverage while standing. In patients with appreciable pelvic obliquity, these differences may warrant consideration when interpreting acetabular morphology and discussing the relative indications for treatment or procedural options because they may lead clinicians to disagree about whether the same hip meets thresholds used in treatment planning. Future work should correlate measurements based on horizontal referencing and interteardrop referencing in patients with appreciable pelvic obliquity with clinical and surgical outcomes to (1) determine whether acetabular indices measured using the interteardrop line or floor-based horizontal reference confer superior clinical value and (2) define procedure-specific thresholds for relevant diagnostic subgroups.
Level Of Evidence:
Level III, diagnostic study.