Endoscopic Hematoma Evacuation and Controlled Inner Membranectomy Using a Modified Single Burr-Hole Technique Under Local Anesthesia for Septated Chronic Subdural Hematomas in Elderly Patients: A Multicenter Retrospective Study
Related Experiment Video
Updated: Nov 4, 2026
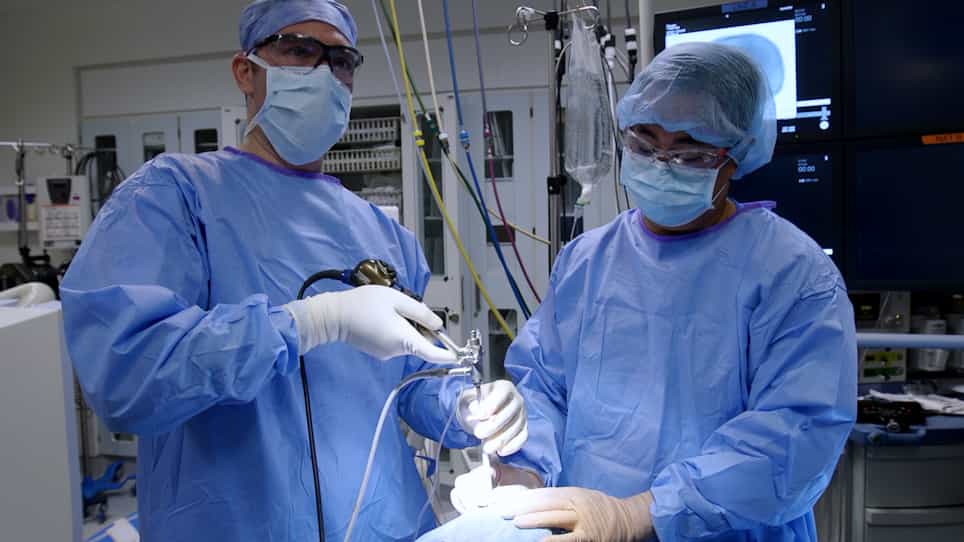
Minimally Invasive Endoscopic Intracerebral Hemorrhage Evacuation
Published on: October 15, 2021
Demet Evleksiz1, Gardashkan Karımzada2, Mehmet İlker Özer3
1Hitit University, Erol Olcok Training and Research Hospital, Department of Neurosurgery, Corum, Türkiye.

Objective:
Septated chronic subdural hematoma (sCSDH) in elderly patients may contain organized components that limit conventional burr-hole drainage. This study evaluates the technical feasibility, perioperative course, and early clinical and radiological outcomes of controlled partial inner membranecotomy using modified single-port endoscopic drainage under local anesthesia in selected elderly patients with sCSDH.
Methods:
We retrospectively analyzed patients aged 65 and older who underwent endoscopic drainage of MRI-confirmed sCSDH under local anesthesia at two neurosurgical centers between March 2022 and July 2025. Demographic characteristics, anesthesia records, complications, radiological findings, and early clinical outcomes were evaluated.
Results:
Eleven of 29 patients (38%) received antiplatelet or anticoagulant therapy. Mean hematoma thickness was 21 ± 6 mm, preoperative midline shift was 10 ± 4 mm, and operative time was 47 ± 10 minutes. At postoperative one month, 26 patients (90%) had an mRS score of 0-1, compared with 9 (31%) preoperatively. Recurrence occurred in 3 patients (10%); 1 (3%) required reoperation, while 2 (7%) were treated conservatively. Postoperative seizures occurred in 2 patients (7%). No patient required conversion to general anesthesia, and no perioperative deaths, surgical site infections, or permanent neurological deficits were observed.
Conclusion:
Endoscopic hematoma evacuation and controlled partial membranecotomy via a single burr hole under local anesthesia and sedation were technically feasible in selected patients and associated with acceptable short-term outcomes. Without a control group, superiority over other surgical approaches or an independent benefit of inner membranotomy cannot be demonstrated.