Validation of Single-Camera MediaPipe BlazePose for Knee Joint Angle Measurement Across Multiple Functional Tasks: Concurrent Validity, Interrater Reliability, and Exploratory Test-Retest Reliability Study
Related Experiment Video
Updated: Nov 5, 2026
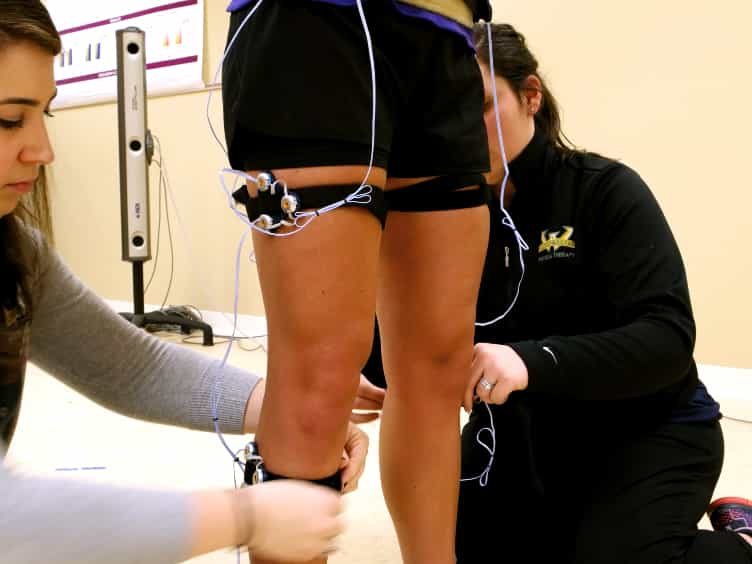
Video Movement Analysis Using Smartphones (ViMAS): A Pilot Study
Published on: March 14, 2017
Xiaotian Yue1, YiXuan Gu1, Bo Yu1,2
1Department of Rehabilitation, School of International Medical Technology, Shanghai Sanda University, 2727 Jinhai Road, Pudong New District, Shanghai, 201209, China.

Background:
Single-camera markerless pose estimation may support accessible knee movement assessment, but performance can depend on task, joint angle, and detection quality, and evidence across complementary measurement properties remains limited.
Objective:
This study aimed to evaluate agreement of MediaPipe BlazePose Heavy knee-flexion estimates with goniometer-set static target positions and with Kinovea 2D video annotation for dynamic tasks, to assess interrater agreement of the Kinovea annotations, and to explore repeated-session performance in a small retest subsample.
Methods:
Squat, sit-to-stand, and bilateral single-leg stance tasks were performed by 15 healthy adults during standardized lateral-view smartphone recording. Static knee flexion was assessed at 4 goniometer-set targets (30°, 60°, 90°, and 120°). Native hip-knee-ankle included angles were converted to clinical knee flexion (0° at full extension). Agreement was assessed using the intraclass correlation coefficient (ICC), specifically ICC2,1, signed bias and 95% limits of agreement, mean absolute error (MAE), and root mean square error (RMSE). Primary intervals used participant-cluster bootstrapping, and limits of agreement accounted for repeated measurements. Dynamic primary estimates were conditional on BlazePose target-frame confidence ≥0.3; low-confidence observations were also reported as detection failures and included in an all-output stress test. Four participants returned after 21 days to 29 days (median 25 d) for exploratory repeated-session analyses.
Results:
Dynamic measurement was available in 177 of 210 observations (84.3%); 33 of 210 observations (15.7%) failed the confidence criterion. Conditional task-specific ICCs were 0.773 (95% CI 0.564 to 0.875; n=71, 15 participants) for squat, 0.632 (95% CI 0.455 to 0.726; n=58, 12 participants) for sit-to-stand, and 0.136 (95% CI -0.078 to 0.482; n=48, 15 participants) for combined single-leg stance. Task-specific availability was present for 71 of 75 observations (95%), 58 of 75 observations (77%), and 48 of 60 observations (80%), respectively. Without the quality gate, squat ICC was 0.428, and RMSE was 25.43°. Static agreement with set targets resulted in an ICC of 0.874 (95% CI 0.770 to 0.953), with RMSE of 15.49° and angle-dependent signed error. Kinovea interrater ICC was 0.999 (95% CI 0.998 to 0.999) overall, which did not establish 3D accuracy. Repeated-session estimates with the 4 participants remained exploratory.
Conclusions:
With dynamic measurement available in 177 of 210 observations (84.3%), agreement among retained outputs depended on task, flexion angle, and detection quality. The findings support further feasibility and screening-level evaluation under controlled acquisition with per-recording quality checks; they do not support replacement of clinical goniometry, precise longitudinal decision-making, absolute 3D kinematic accuracy, or generalization to clinical populations or other smartphones.
