Minimally Invasive Cardiac Surgery: A Health Economic Perspective
Related Experiment Video
Updated: Nov 6, 2026
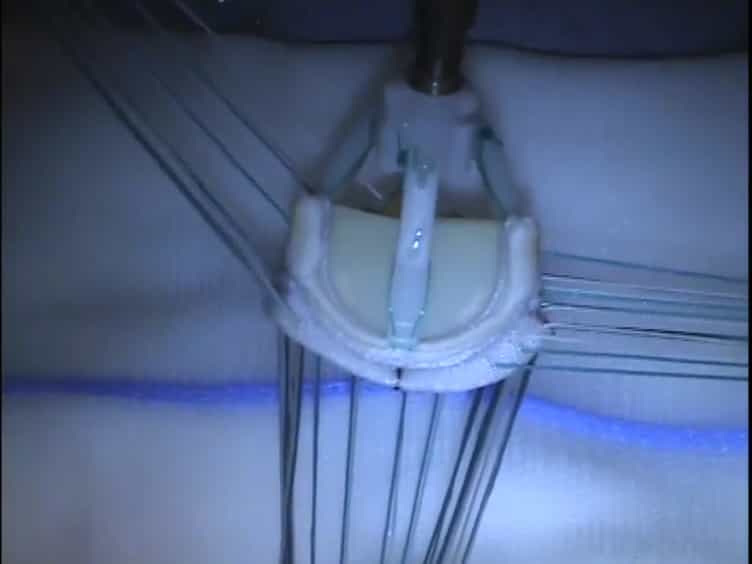
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
Megan B Meechem1,2, Kevin Liu3, Toshiro Ws Sembo3
1Libin Cardiovascular Institute, University of Calgary, Calgary, AB T2N 1N4, Canada.

Abstract:
This study aimed to review the contemporary literature on the health economics of minimally invasive cardiac surgery (MICS). MICS is being increasingly adopted worldwide. While the clinical and patient-reported outcomes of MICS have been established, uncertainty remains regarding the health economic aspect of MICS. This review aims to address that knowledge gap. This is a comprehensive narrative review of articles evaluating the health economics of MICS across various jurisdictions and healthcare systems. Electronic databases, including PubMed, Embase, and Scopus, were searched from inception through November 2025. Search terms included combinations of MICS, health economics, minimally invasive direct coronary artery bypass, mini-aortic valve replacement, mini-thoracotomy, hemi-sternotomy, aortic valve replacement, right anterior mini thoracotomy, robotic cardiac surgery, robot-assisted cardiac surgery, video-assisted cardiac surgery, and port-access cardiac surgery. Across procedure types, studies consistently demonstrated that high-volume, well-standardized MICS programs can achieve cost neutrality or cost savings, relative to conventional surgery, with reported hospital cost reductions ranging from approximately 9% for mini-aortic valve replacement to CAD 16,700 for minimally invasive mitral valve surgery. These savings are largely attributable to improved postoperative efficiency and reduced resource utilization. In contrast, centers with low surgical volumes or fragmented workflows often incur significantly higher costs per case and risk underutilizing expensive technologies, such as robotic systems. When implemented in well-resourced, experienced centers, MICS appears to be a promising, value-driven strategy for contemporary cardiac care. Health systems should consider centralizing MICS services to optimize capital investment and realize sustainable economic value, rather than distributing these resources broadly across lower-volume centers.
Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Mitral Stenosis III: Medical Management
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:25
Mitral Regurgitation III: Medical Management