[Right S1+2+3a Extended Segmentectomy Assisted by Three-dimentional Computed Tomography Volumetric Analysis in a Patient With Poor Pulmonary Function]
Related Experiment Video
Updated: Nov 7, 2026
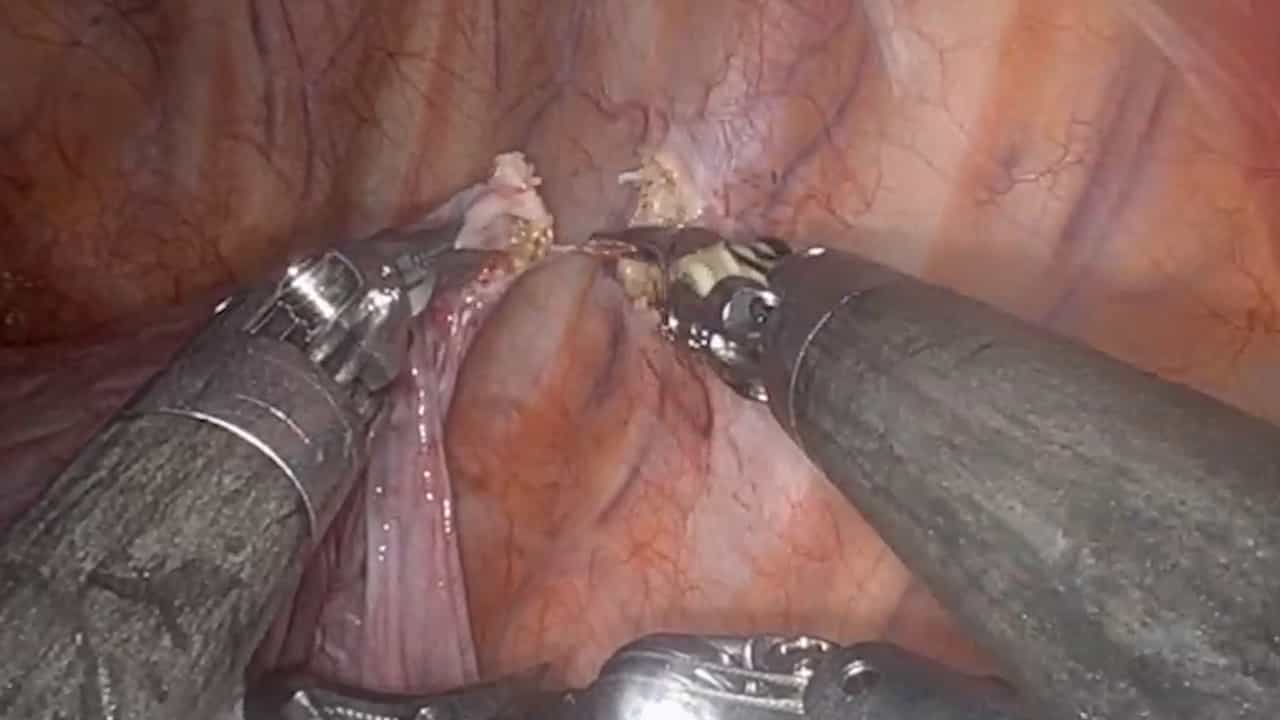
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Yoshimasa Tokunaga1, Nariyasu Nakashima
1Department of General Thoracic Surgery, Sakaide City Hospital, Sakaide, Japan.

Abstract:
An 81-year-old woman was referred to our department for a 15-mm ground-glass opacity in segment S2 of the right upper lobe. Preoperative spirometry showed severely reduced pulmonary function [forced expinatory volume in one second (FEV1) 960 ml], with minimal improvement after two weeks of long-acting β-agonist (LABA)/long-acting muscarinic antagonist (LAMA) therapy. Three-dimensional computed tomography (3D-CT) volumetric analysis and preoperative CT revealed that subsegment S 3b(310 ml) had a larger volume than the middle lobe and suggested incomplete fissure formation between S3 and the middle lobe, providing a rationale for preserving S 3b. The tumor was adjacent to both S1 and S 3a, and securing an adequate surgical margin required hilar-based resection;thus, thoracoscopic right S1+2+3a extended segmentectomy was performed. Pathology demonstrated minimally invasive adenocarcinoma. The postoperative course was uneventful, and the patient was discharged on postoperative day five. Two months after surgery, FEV1 improved to 1,350 ml, reflecting both preserved S 3b function and the delayed therapeutic effect of LABA/LAMA. This case highlights the value of 3D-CT volumetric analysis for preoperative assessment and individualized surgical planning. Even in patients with poor pulmonary function, extended segmentectomy with selective subsegmental preservation can be safely performed when sufficient residual volume is confirmed.