When does robotics add value in splenic surgery? From total splenectomy to precision and function-oriented spleen preservation
Related Experiment Video
Updated: Nov 9, 2026
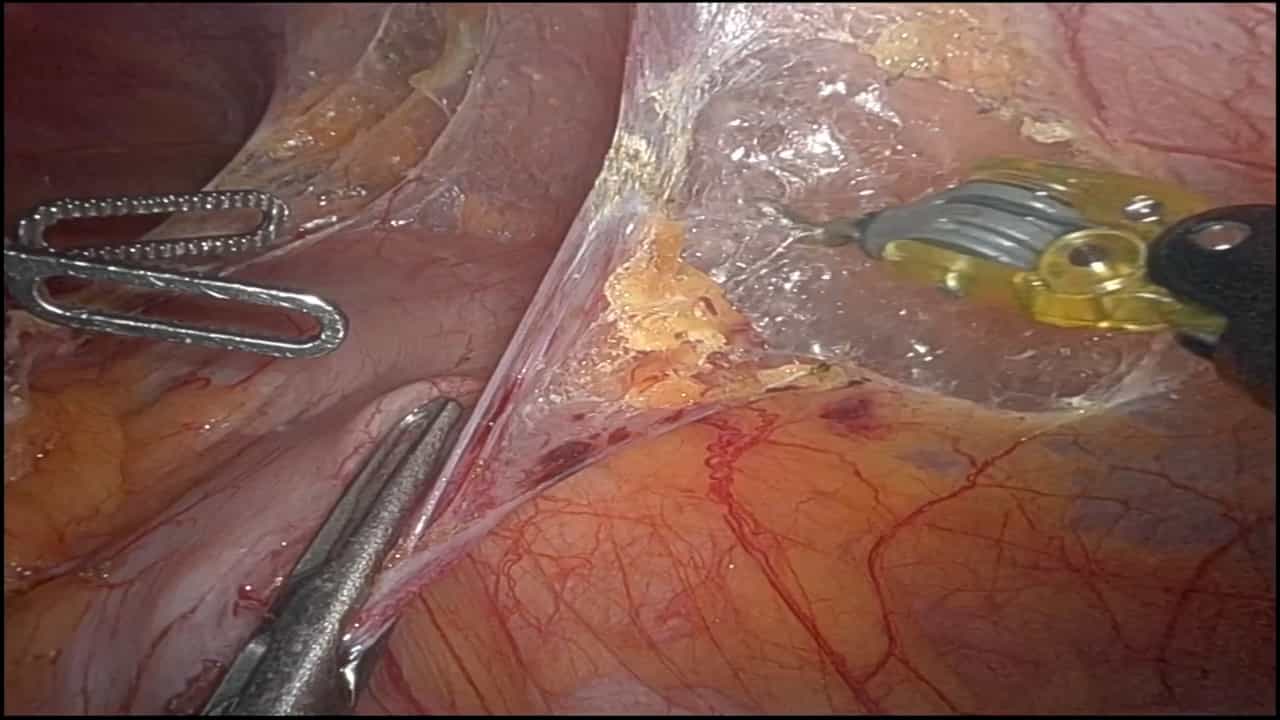
Robot-assisted Partial Splenectomy
Published on: January 2, 2026
Tianfei Gao1, Shunzhao Zhang1, Yixing Yin1
1Department of Hepatobiliary, Pancreatic and Splenic Surgery, The Affiliated Calmette Hospital of Kunming Medical University (The First People's Hospital of Kunming), Kunming, Yunnan, China.

Abstract:
Robotic platforms are increasingly used for technically demanding splenic dissection and spleen-preserving procedures, yet their incremental clinical value over conventional laparoscopy remains uncertain. The clinical rationale for preserving splenic tissue is distinct from the question of whether robotic assistance improves outcomes; evidence supporting spleen preservation should not itself be interpreted as evidence of robotic superiority. This structured narrative review, informed by a PRISMA 2020-reported search of PubMed, Embase, and Web of Science Core Collection, examines the settings in which robotics may offer additional value across routine and complex total splenectomy, precise hilar dissection, and partial splenectomy. Potential technical advantages are considered against implementation burden, including operative time, platform cost, team training, and emergency-conversion requirements. Three-dimensional vascular reconstruction, intraoperative ultrasonography, and indocyanine green fluorescence imaging are discussed as enabling technologies within an Anatomy-Perfusion-Function framework that distinguishes anatomical preservation, perfusion preservation, and functional preservation. Direct evidence remains dominated by retrospective cohorts, small series, and technical reports; data from pancreatic and gastric surgery provide only indirect support for precise splenic hilar manipulation. Given the heterogeneity and predominantly non-randomized nature of the available evidence, current findings support selective, scenario-specific use rather than claims of general robotic superiority. Future studies should compare platforms within the same clinical indication and complexity stratum while assessing perioperative outcomes, functional endpoints, and resource use together.