Related Experiment Video
Updated: Aug 18, 2026
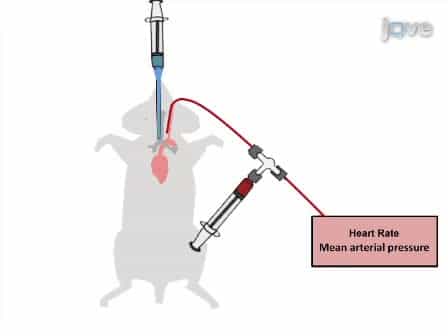

Pressure Controlled Ventilation to Induce Acute Lung Injury in Mice
Published on: May 5, 2011
Effect of alpha and beta adrenergic blockade on epinephrine induced pulmonary insufficiency

Abstract:
Recent studies demonstrated that epinephrine causes significant pulmonary A-V shunting. This study reports the effect of alpha and beta adrenergic blockade on this shunting. Sixty-three anesthetized mongrel dogs were ventilated with a mechanical respirator. Measurements of (1) the pulmonary shunt, (2) cardiac output, (3) mean pulmonary artery, pulmonary capillary wedge and systemic pressures, and (4) pulmonary and systemic vascular resistances were obtained at 5, 15 and 30 minute intervals during the first hour and hourly for 5 hours. Fifteen dogs received no treatment. All others received epinephrine hydrochloride, 2 mug/kg/min for 5 hours. Ten received epinephrine only. Ten were pretreated with propranolol hydrochloride, 250 mug/kg, 12 with phenoxybenzamine, 1 mg/kg, and 16 with phenoxybenzamine and propranolol. Propranolol significantly decreased the epinephrine induced pulmonary shunt at all times and was the most effective drug. Phenoxybenzamine decreased the early shunting, but less than propranolol, and did not decrease the late shunting. Blockade with propranolol and phenoxybenzamine was less effective than propranolol alone. Based on the observed hemodynamic changes it was suggested that beta blockade is effective in reducing epinephrine induced pulmonary insufficiency by favorably altering the flow and distribution of pulmonary blood flow which in turn decreases epinephrine induced ventilation-perfusion inequalities and capillary hypertension both of which result in shunting. Conversely phenoxybenzamine has an unfavorable effect on the pulmonary flow. These studies support previous work in animals and man which showed that beta adrenergic stimulation is important in the pathogenesis of pulmonary insufficiency. Because the amounts of epinephrine used produce blood levels observed in critical illness, these studies add support to a relationship between the increased catecholamine stimulation of critical illness and the associated and often unexplained pulmonary insufficiency.
Related Concept Videos
 01:26
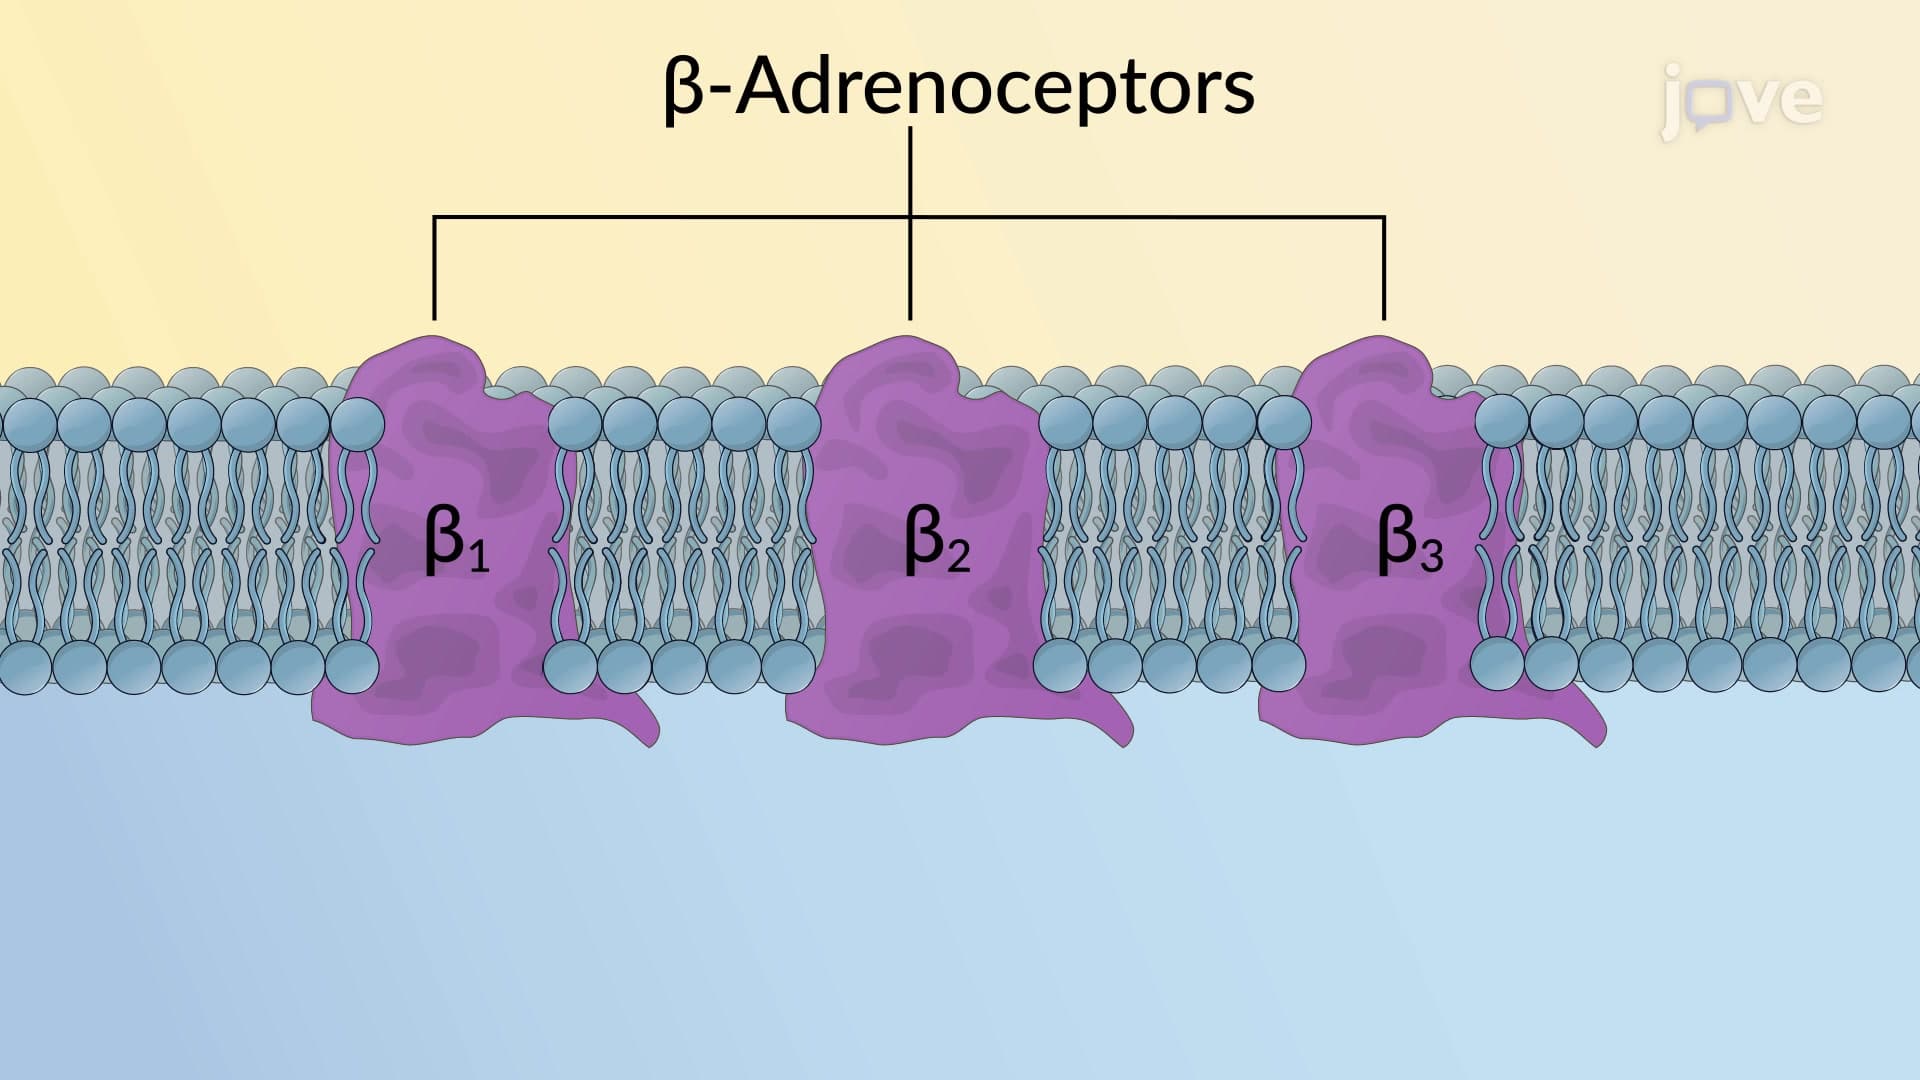
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:22
Heart Failure Drugs: β-Blockers