Related Experiment Video
Updated: Aug 11, 2026
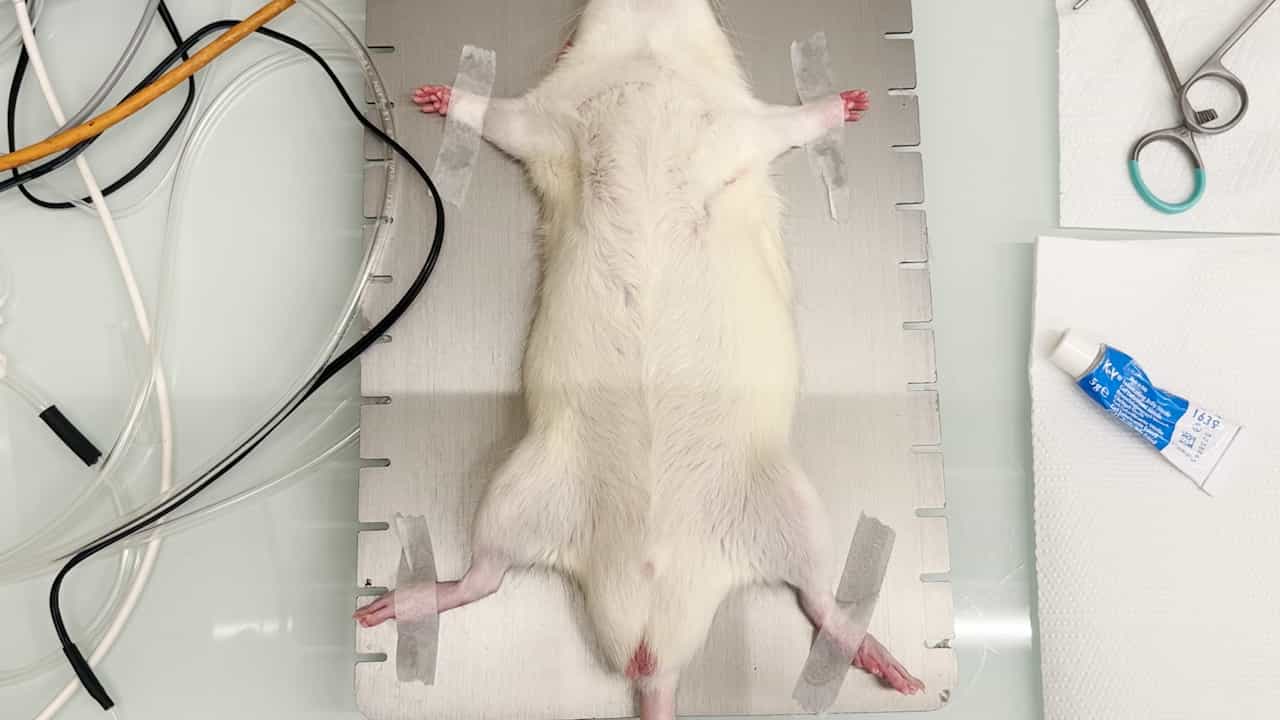
A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
Published on: August 15, 2025
Massive spontaneous hemoperitoneum due to rupture of visceral branches of the abdominal aorta

Review of 153 cases of massive spontaneous hemoperitoneum following visceral arterial rupture showed that 94% of all young women and 100% of all pregnant women had ruptured congenital splenic artery aneurysms at the time of hemorrhage, whereas young males bled from a variety of sources. Individuals who were 45 years old or older bled either from lesions of the celiac axis or its branches (66%) or from arterial mesenteric system lesions (34%). Only 22% of the older individuals of either sex bled from splenic artery sources. Arterial hypertension was present in 40% and previous or simultaneous intracranial hemorrhage occurred in 9% of the older patients. There were no survivors among those in whom the bleeding source was not operatively controlled. With operation, 79% of the younger patients and 57% of the older ones survived. Results emphasize the high mortality of visceral artery rupture with intraperitoneal bleeding. Prophylactic excision is advised for all complicated aneurysms regardless of age and all uncomplicated aneurysms in healthy individuals, especially in fertile or pregnent women.
Review of 153 cases of massive spontaneous hemoperitoneum following visceral arterial rupture showed that 94% of all young women and 100% of all pregnant women had ruptured congenital splenic artery aneurysms at the time of hemorrhage, whereas young males bled from a variety of sources. Individuals who were 45 years old or older bled either from lesions of the celiac axis or its branches (66%) or from arterial mesenteric system lesions (34%). Only 22% of the older individuals of either sex bled from splenic artery sources. Arterial hypertension was present in 40% and previous or simultaneous intracranial hemorrhage occurred in 9% of the older patients. There were no survivors among those in whom the bleeding source was not operatively controlled. With operation, 79% of the younger patients and 57% of the older ones survived. Results emphasize the high mortality of visceral artery rupture with intraperitoneal bleeding. Prophylactic excision is advised for all complicated aneurysms regardless of age and all uncomplicated aneurysms in healthy individuals, especially in fertile or pregnent women.


Related Concept Videos
 01:15
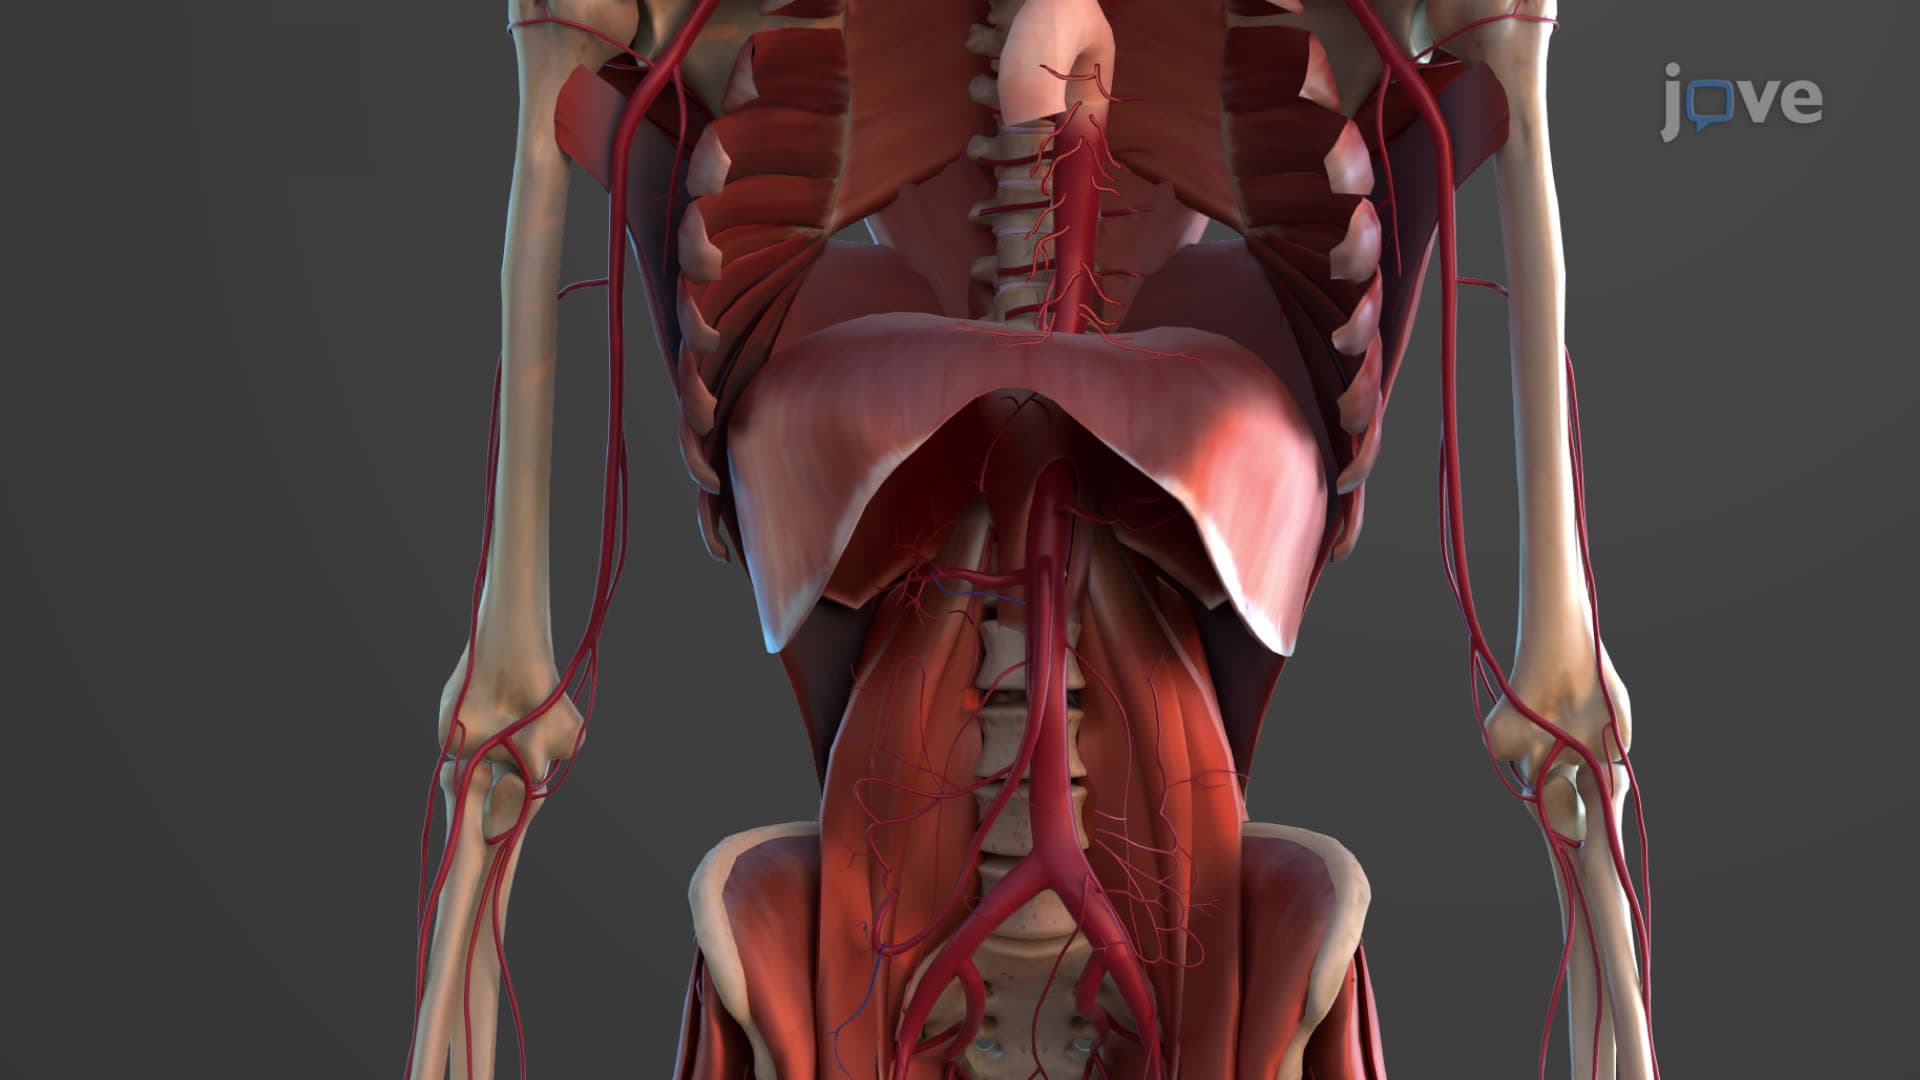
Thoracic Aorta
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:24
Esophageal Varices-I: Introduction
 01:30
Aneurysm I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Aneurysm III: Interprofessional Care