Related Experiment Video
Updated: May 3, 2026


Leveraging Turbidity and Thromboelastography for Complementary Clot Characterization
Published on: June 4, 2020

Platelet production, distribution, and destruction have been quantitated in normal man and in selected patients with platelet disorders. In most instances, total production as calculated from the megakaryocyte mass agreed with production estimated from platelet turnover. In patients with megaloblastosis, a discrepancy between these two measurements indicated the presence of ineffective thrombopoiesis. Thrombopoiesis was regulated by (a) alterations in megakaryocyte number, and (b) changes in megakaryocyte volume (produced by changes in endomitosis). The volume-endomitosis changes were closely related to the peripheral platelet count and were a useful indicator of thrombopoietic stimulus. Thrombocytopenic disorders have been classified on the basis of the disturbed physiology into disorders of (a) production (hypoproliferative or ineffective), (b) distribution (splenic pooling), or (c) destruction (immune or consumptive). Less than a twofold increase in platelet production in the presence of significant thrombocytopenia was taken to represent impaired proliferation. Thrombocytosis was classified as reactive or autonomous. Reactive thrombocytosis was consistently associated with a mean megakaryocyte volume and endomitosis less than normal but appropriate for the elevated circulating platelet count. In contrast, the average megakaryocyte volume and nuclear number were always greater than normal in thrombocythemia findings indicating autonomy.
Platelet production, distribution, and destruction have been quantitated in normal man and in selected patients with platelet disorders. In most instances, total production as calculated from the megakaryocyte mass agreed with production estimated from platelet turnover. In patients with megaloblastosis, a discrepancy between these two measurements indicated the presence of ineffective thrombopoiesis. Thrombopoiesis was regulated by (a) alterations in megakaryocyte number, and (b) changes in megakaryocyte volume (produced by changes in endomitosis). The volume-endomitosis changes were closely related to the peripheral platelet count and were a useful indicator of thrombopoietic stimulus. Thrombocytopenic disorders have been classified on the basis of the disturbed physiology into disorders of (a) production (hypoproliferative or ineffective), (b) distribution (splenic pooling), or (c) destruction (immune or consumptive). Less than a twofold increase in platelet production in the presence of significant thrombocytopenia was taken to represent impaired proliferation. Thrombocytosis was classified as reactive or autonomous. Reactive thrombocytosis was consistently associated with a mean megakaryocyte volume and endomitosis less than normal but appropriate for the elevated circulating platelet count. In contrast, the average megakaryocyte volume and nuclear number were always greater than normal in thrombocythemia findings indicating autonomy.
More Related Videos


Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:18
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 00:59
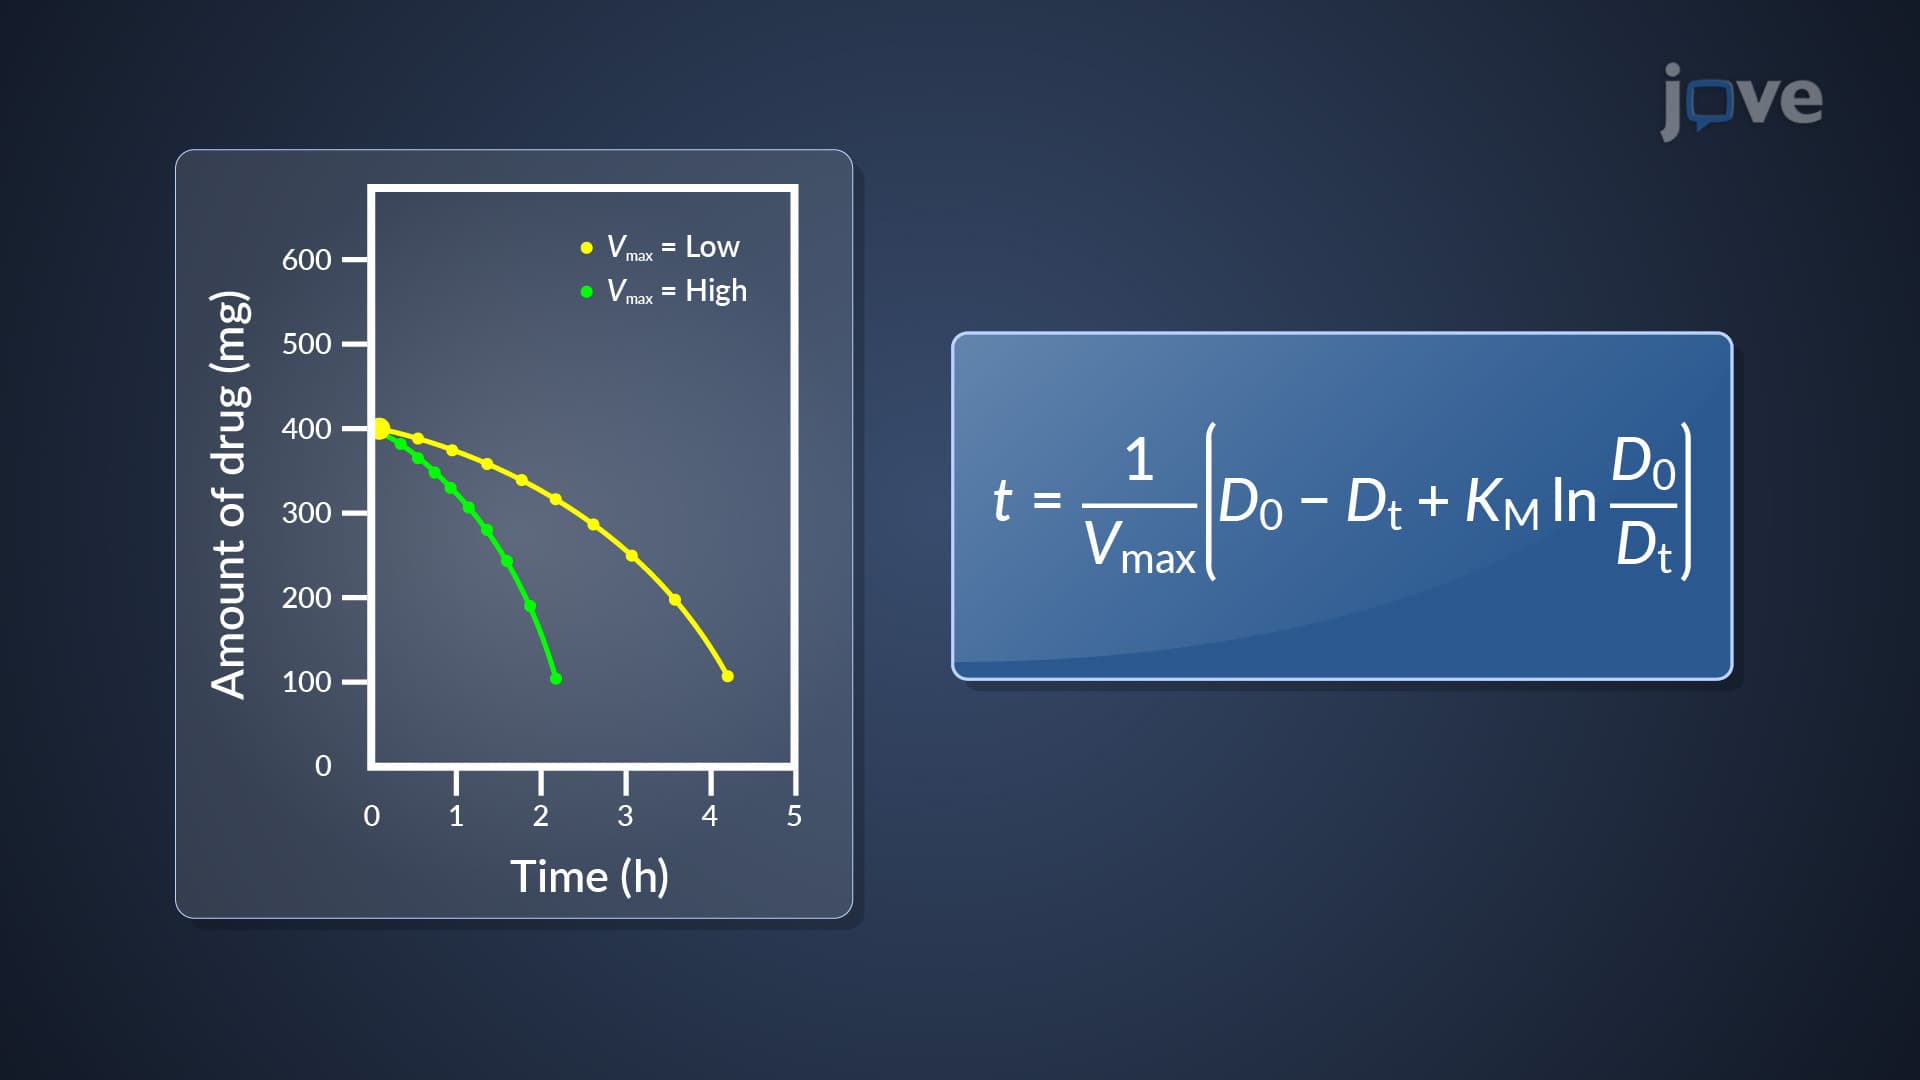
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...
 01:30
Measurement of Bioavailability: Pharmacokinetic Methods
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:29
Venous Thrombosis III: Interprofessional Care