Related Experiment Video
Updated: Aug 3, 2026


In Vitro Assays to Evaluate the Migration, Invasion, and Proliferation of Immortalized Human First-trimester Trophoblast Cell Lines
Published on: March 5, 2019
Inhibition of beta-adrenergic responsiveness in muscle cell cultures by dexamethasone

Abstract:
Cultures of two myogenic cell lines, L6E9 and L8, were grown in the absence or presence of dexamethasone. Dexamethasone (1 microM) completely inhibited the formation of myotubes. Partial inhibition (20-40%) was obtained at a concentration as low as 1 nM. Dexamethasone also inhibited beta-adrenergic responsiveness, as noted by decreases in isoproterenol-stimulated adenylate cyclase activity and cAMP accumulation. These effects were both dose and time dependent. In the presence of dexamethasone, the number of beta-adrenergic receptors, as assessed by [125I]iodohydroxybenzylpindolol binding, decreased coordinately with the decrease in cAMP. A high affinity, limited capacity cytosolic binding site for [3H]triamcinolone acetonide observed under control conditions (Kd = 0.7 nM; maximum binding, 2.7 pmol/mg protein) increased in number as a function of developmental state. These data indicate that glucocorticoids inhibit myogenesis and beta-adrenergic responsiveness in vitro.
Insights
Dexamethasone, a glucocorticoid, inhibits muscle cell development (myogenesis) and reduces beta-adrenergic responsiveness in cell cultures. These effects are dose-dependent, impacting cell function and receptor levels.
Area of Science:
- Biochemistry
- Cell Biology
- Pharmacology
Background:
- Myogenesis is the process of skeletal muscle formation.
- Beta-adrenergic signaling plays a role in muscle cell function.
- Glucocorticoids are steroid hormones with diverse physiological effects.
Purpose of the Study:
- To investigate the effects of dexamethasone on myogenic cell lines.
- To determine if dexamethasone impacts beta-adrenergic responsiveness.
- To explore the relationship between glucocorticoids, myogenesis, and adrenergic signaling.
Main Methods:
- Culturing L6E9 and L8 myogenic cell lines.
- Treating cells with varying concentrations of dexamethasone.
- Measuring adenylate cyclase activity and cAMP accumulation.
- Assessing beta-adrenergic receptor density using radioligand binding.
Main Results:
- Dexamethasone completely inhibited myotube formation at 1 microM and partially inhibited it at 1 nM.
- Beta-adrenergic responsiveness, including isoproterenol-stimulated adenylate cyclase activity and cAMP levels, was decreased by dexamethasone.
- The number of beta-adrenergic receptors decreased in parallel with cAMP levels in the presence of dexamethasone.
- A high-affinity cytosolic binding site for triamcinolone acetonide increased with developmental state.
Conclusions:
- Glucocorticoids, such as dexamethasone, inhibit myogenesis in vitro.
- Dexamethasone impairs beta-adrenergic responsiveness in myogenic cells.
- These findings suggest a significant role for glucocorticoids in regulating muscle development and function.

Related Concept Videos
 01:26
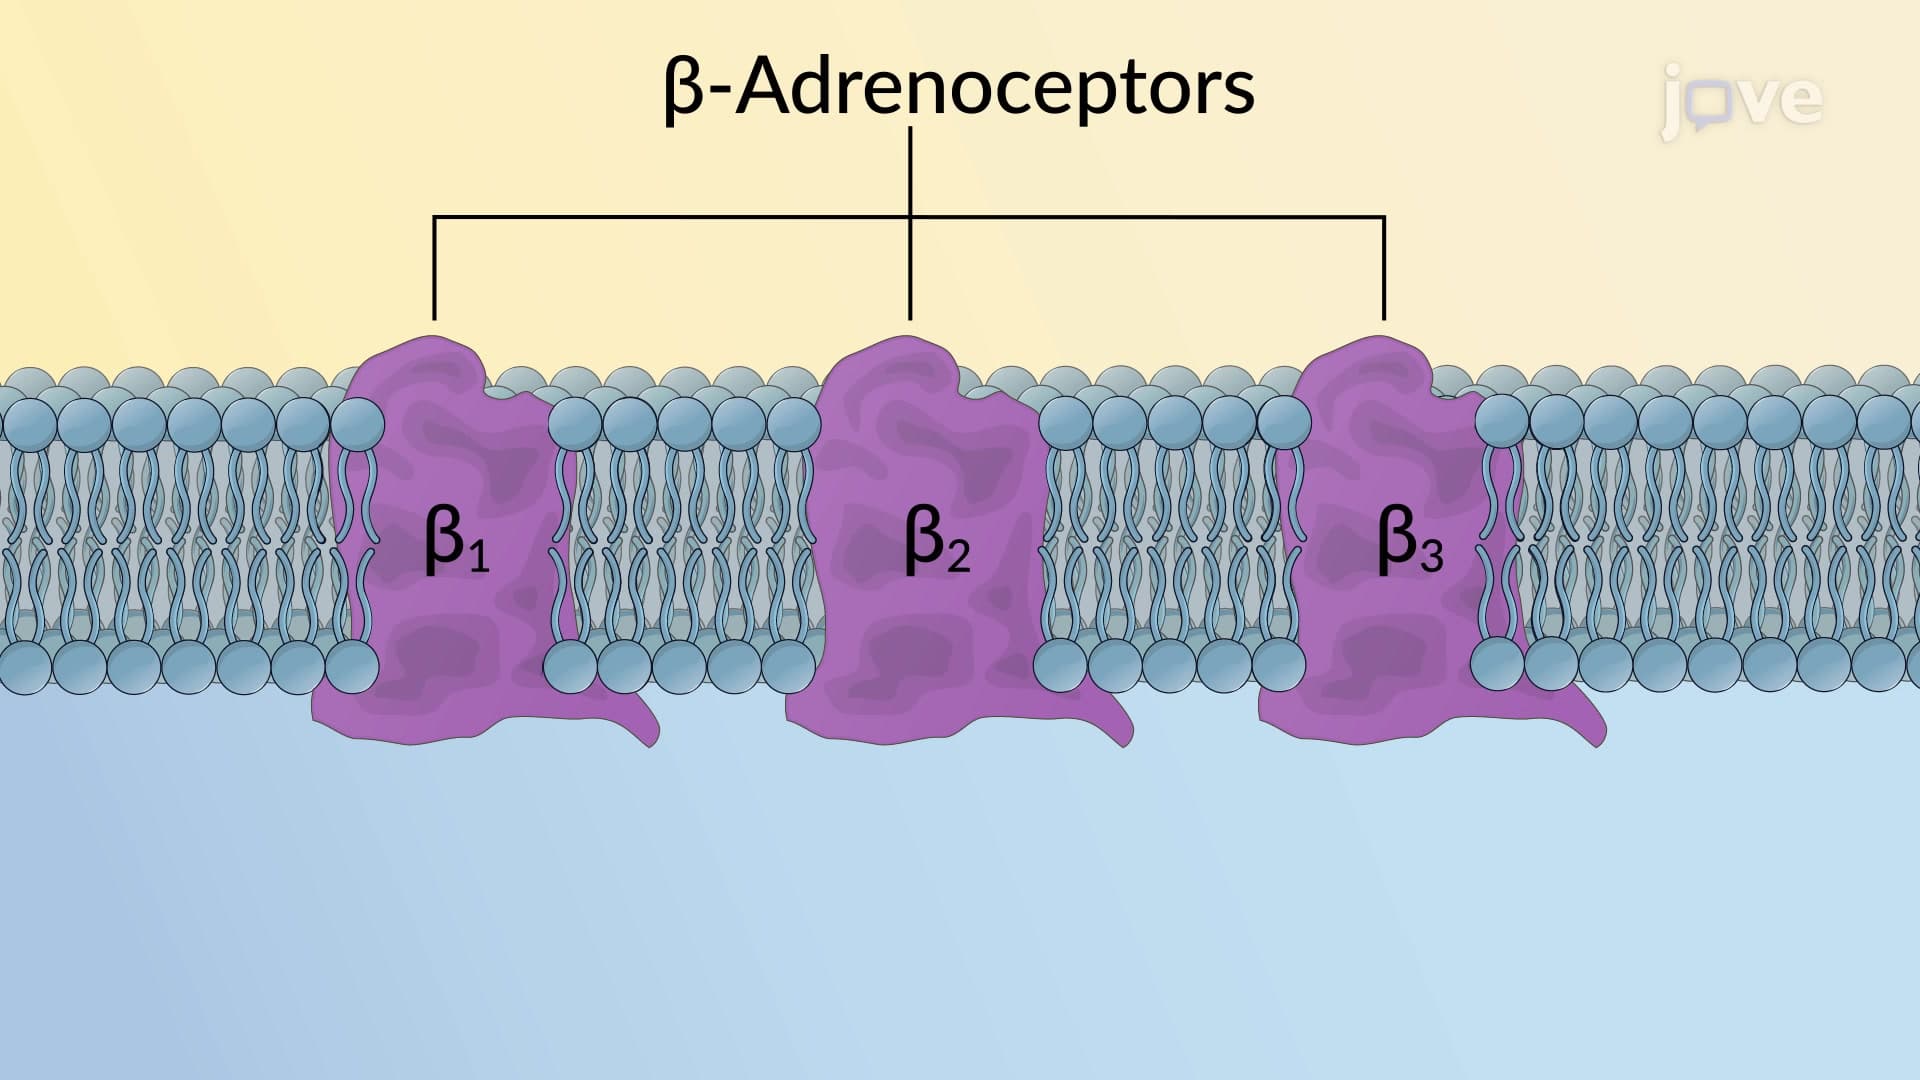
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers